

Sunday Snippets: Nov 24, 2025

Another in a weekly series of brief snippets of health care stories that bemused, intrigued and otherwise beguiled me over the past week along with my random thoughts on the matter.

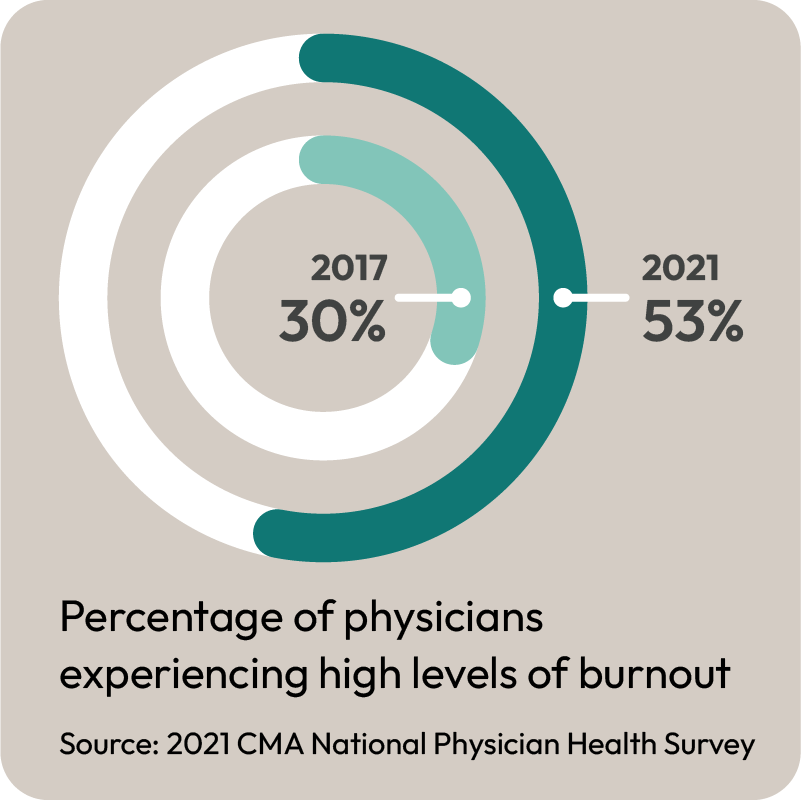
Item: Dr. Sarah Giles writes in the CBC about how she was forced to cut her hours because of the burnout.

My thoughts: Kudos to Dr. Giles for talking so openly about this. Alarmingly few of my colleagues are willing to talk about burnout and how the system is affecting them. Instead they suffer in private, and that’s not healthy for them OR the patients they serve. It’s an important story that needs to be told over and over again.
Item: “Involuntary medical treatment” for people with addiction issues seems to be all the rage. A great article in the “Conversation” shows that this won’t solve anything, and in fact will make things worse.

My thoughts: I really can’t believe we are even discussing this. It has been well known for…..well forever, that people will not get better unless they want to seek help. We have to focus on making seeking help easier, not forcing them.

Item: The always excellent Dr. Katelyn Jetelina, who most of my colleagues know as a superb voice of reason and information during the height of the Covid pandemic, writes about her feelings now that RFK junior has been nominated to lead Health and Human Services in the United States.

My thoughts: My heart goes out to her and all the hard work staff who have tried keep us all safe during the pandemic. They deserve better.

Robert F. Kennedy Jr., a leading American Anti-Vax conspiracy theorist, now tapped to head Health and Human Services in the United States

Item: TV Ontario had a segment suggesting that foreign trained physicians could help tackle Ontario’s physician shortage.

My thoughts: I’ll shout it out again, we already have enough family doctors in Ontario who are already licensed to practice medicine in this province and are familiar with the Ontario Health Care system. The number is approximately 6,000 or so (see the graphs in the linked blog for details). Can we just not make it easier to practice family medicine instead??? If we can get even 1/3 of those doctors already in Ontario to start a practice, we would end this crisis.

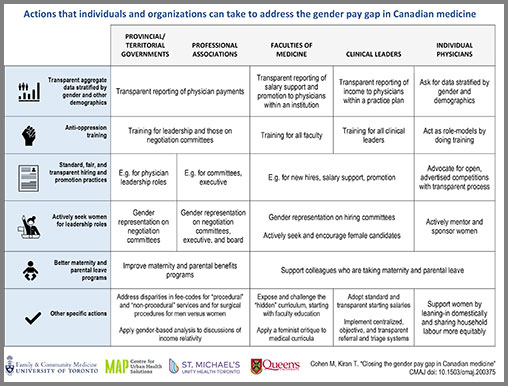
Item: Great article on the physician gender wage gap in Health Debate. Clearly shows that the gap is real and needs to be corrected.

My thoughts: One of the best accomplishments of the OMA Board when I was on it was to publish the gender pay gap report. It was arguably too late, but I believe we were the first PTMA to discuss this and to use that as a basis for future negotiations work. While I’ve had some issues with how negotiations have been handled since, I am quite comfortable in saying that positions of the OMA in negotiations would take this into account and that there is likely to be funds demanded to narrow this gap. The blame for the fact that there has been no progress on this lies mostly at the feet of the Ministry of Health. We don’t have an agreement yet on how to divide the arbitration award – and that means the Ministry is not responding to OMA proposals that would close this gap. Shame on them.
Item(s): Alberta announced that it hiring a large number of nurse practitioners to become “primary care providers” to patients who don’t have a family doctor.

My thoughts: The National Health System (NHS) in Britain is under fire for the fact that it too tried to replace the work done by fully trained physicians, with staff who were likely well intentioned, but had less qualifications. It turns out there is significant risk to this, and likely a markedly increase cost in providing health care. The article “My wife died because the NHS used cheap labour” should be, in my opinion, required reading for any politician/health care bureaucrat who thinks they can provide better care by using less trained people.

That’s all for this week. Back next week (probably) with more.

Bureaucratic Vertigo in Ontario’s Home Care System

Bureaucratic vertigo in Ontario’s home care system, exacerbated by ineffective reforms and rebranding, has led to chaos and service stagnation, necessitating genuine engagement with frontline providers for meaningful transformation.

Dr. Merritt Cade (not their real name) is a concerned and experienced Ontario physician familiar with the current crisis in home care. Dr. Cade is worried about potential blowback from this blog that will affect their patients and so this blog is posted under a pseudonym.

Vertigo is a sensation where one perceives movement that isn’t happening. In the realm of healthcare administration, a similar phenomenon occurs—bureaucratic vertigo—an organizational dizziness that mimics change but leaves structures and systems untouched. Nowhere is this more glaring than in Ontario’s home care sector, a pivotal yet neglected component of our healthcare system.

In 2023, amid promises of reform, the Ontario government introduced Bill 135, the “Convenient Care at Home Act,” envisioning a streamlined home care service managed by Ontario Health atHome (OHAH). OHAH itself was to now be brought under the umbrella of Ontario Health, the implementation arm of the Ministry of Health. Hopes were pinned on this transformation bringing ease and efficiency. However, the reality has been a déjà vu of previous cycles of centralization and decentralization of health care structures, with patients and families shouldering the consequences.

Nowhere is the bureaucratic vertigo more evident than in the successive re-branding of home care over the last 8 years from “Community Care Access Centres (CCAC)” to “Local Health Integration Networks (LHINs)” in 2017 to “Home and Community Care Support Services (HCCSS)” in 2021, to the latest iteration, “Ontario Health atHome (OHAH)” in 2024. Meanwhile, regardless of the name used, the services provided by the home care system remained untouched.

Ontario Health and OHAH’s first substantive move—renegotiating contracts for medical supplies—illustrates how bureaucratic vertigo can lead to harmful consequences. Instead of solving issues, the new contract process disconnected decision-makers from frontline realities. The result? A severe shortage of medical supplies, medication delays, and a burden placed on already overwhelmed caregivers and families. Despite clear warnings from supply companies, these decisions disregarded frontline input, leaving healthcare providers to navigate chaos without support.

OHAH’s own front-line staff, the beleaguered Care Coordinators, were also caught completely off guard as rules regarding medications and catalogues of supplies changed overnight. Care Coordinators are the quarterbacks of the home care system, matching services to patients’ needs. What OHAH and Ontario Health did was akin to completely changing the playbook on their quarterbacks and teams, with sadly predictable results.

Despite all this, however, home care holds immense potential to address systemic challenges, from reducing ER congestion and the alternate level of care logjam to facilitating dignified end-of-life care at home instead of in hospitals. What is required is not another bureaucratic shuffle, but genuine engagement with those who understand home care’s nuances best: frontline providers. It is they who hold the practical knowledge necessary for meaningful reform.

The path forward demands that decision-making authority be shared with these healthcare professionals. Their experiences can inform policies that work in reality, not just on paper. This means abandoning the “bureaucrat knows best” mentality and embracing trust and collaboration. It means abandoning committees struck merely to check a box that says that frontline professionals were consulted when, in fact, their concerns do not meaningfully contribute to decisions made.

Furthermore, the status quo must not define future transformations. Further substantial changes to home care delivery, this time relating to the supply of equipment such as hospital beds, wheelchairs, walkers and other essential aids, was planned for rollout in October but has been delayed until January. Without a change in approach, we should expect similar upheaval when this takes place. Past failures demonstrate that superficial organizational changes do not equate to operational improvements. Genuine progress relies on a foundational renewal of leadership and strategy, prioritizing empathy, accountability, and proactive stakeholder engagement.

If we are to lift Ontario’s home care from its current crisis, change must be substantive, rooted in the insights of those who deliver care day-in, day-out. We must move beyond the spectre of bureaucratic vertigo and commit to sensible, informed solutions that truly benefit patients and families across the province. By trusting, listening to and involving the frontline, we can stop the spin and start the real work of reform.

We Know How to Save Family Medicine. Why Aren’t We Doing It?

I’m honoured to have Dr. Mark Linder guest blogging for me today. I first met Dr. Linder during our time advocating against Dr. Eric Hoskins unilateral cuts to health care. He’s exceptionally well spoken and articulate . He’s a former ER doctor and now full time family physician and clinic owner. His other claim to fame is that got fired from the Kaplan MCAT teaching course after one session – which apparently was a first.

I just wrote this in a flurry this morning. I see stupider and stupider proposals from the government and from newspaper editorials. I see our new grads learn from their teachers that they need to stay away from this job. I then see the  domino effect this has on recruitment, job satisfaction and reinforced by absurd government initiatives to save the system. I watch the OMA get pulled in every direction to try and please everyone. So apologies in advance -this is just my take really-and mostly to get it off my chest-not that it will lead anywhere. So thanks for reading.

The Family Health Organization (FHO) is what saves family medicine. It has done it before and it can do it again.

In 2006 something unprecedented happened. It hasn’t happened before or since. And perhaps we didn’t quite appreciate how unique it was. The provincial Liberal government, under Dalton McGuinty and Health Minister George Smitherman, introduced an upgraded payment model for Family Medicine. It built on the existing capitation based Family Health Network (FHN) model to enhance it.

What was so unique about this? It stands out as one of the only times a government has thought beyond their 4 year term to the ultimate health of their population as well as their economy down the road when they may no longer be in power.  Sure, it was going to make them look good if everyone got a family doctor out of it-but it was a big expensive risk, a risk based on an assumption that family medicine was critical to the system, AND that practitioners need to be paid fairly for their work if they wish to retain these doctors in the future. A different time to be sure!

It worked. Look at the stats from 2008 to 2018. Look at how many Family Doctors gladly embraced the new system. Look how the number of orphaned patients dropped. 

The system had flaws. I mean this was the second iteration of what was described as an experiment. The “outside use” enforcement rule made little sense in most cases. The calculation of capitation payments wasn’t always a fair representation of how much work it took to look after the patient in front of you. Certain “in the basket” fees were bizarre and should never have been part of the package.  Doctors were actually more incentivized to send people to the ER over a walk in clinic!!! But all in all, it was a great innovation, a great idea, and saved family medicine. It also, no doubt saved the province millions in treatment dollars and ER visits as family doctors made themselves available to look after patients.

And then, In 2015 Kathleen Wynne and Eric Hoskins, the health minister at the time, effectively shut down enrollment in FHOs And that was the beginning of the end. I presume they just wanted to control the immediate budget – paying for family medicine up front meant huge savings down the road. But it resulted in a pretty big chunk of budget going out the door NOW. And the Wynne liberals didn’t have a health care crisis, didn’t heed the warnings that we as physicians laid out pretty starkly at the time, and decided, nah, we’ll just “pause” the experiment.

Which they did. And the fall out was obvious. As a clinic owner and a family doctor, I had a front row seat.  The residents and new grads had all been trained in the new system, and now were unable to access it. If they wanted to work, they’d be taking a tremendous risk setting up a clinic in a Fee For Service environment using a Schedule of Benefits that had failed to keep up with inflation for 20 years. They were screwed.  The aging Family Doctor population continued to retire at a predictable rate, and the aging population continued to get more desperate to find doctors with increasing difficulty.

By the time the FHO’s opened up again in 2021, it barely mattered–The reputation of family medicine among new grads had been thrashed for 6 years. 
With the new rules, new grads would have to gather 6 like-minded individuals (instead of just 3 like in the old days), or find a bigger FHO that was already established and could fit them in. Not so easy. Opening up your own shop had become increasingly more expensive with post pandemic inflation, so the debt would be crippling just to get started if you wanted your own clinic. And these are graduates who already had a huge amount of debt coming out of school.

Couple this with the insane increase in administrative burden as we become more and more efficient at having hospitals and labs forward us copies of paperwork. In theory, amazing, in practice hugely burdensome, time consuming and unpaid. Arguably, if the FHO rates had increased at the level of inflation, there’d be no complaints about this additional work. But the FHO rates had more or less remained static relative to the cost of doing business. Still better than FFS, still paid a lot less than the actual market value of doing the job as proven by the lack of uptake that continues today.

The thing is: The FHO is still the answer. It absolutely needs some significant tweaks. The rates need to go up. The outside use concept needs to go. Minimum size and shared EMR requirement needs to be softened so that smaller groups can join together in nearby geographic areas. Some sort of separate funding will be essential to help clinic owners to keep up with inflation.  But it still achieves by far the best mix of physician autonomy, clinic management, and long term government savings. And it’s evidence-based! We have a recent history we can look back on to demonstrate efficacy!

Other solutions, such as having lesser-trained individuals diagnosing and managing patients give the appearance of short term gains at a huge future cost as more referrals to specialists are made and more referrals to the ER are made. Another concept of having government run all clinics is clearly so expensive as to be dead at the gates-Doctors currently pay for rent, administration and their own retirements out of their incomes. It’s not great for us, but it’s a heck of a lot cheaper for the taxpayer to do it that way, and simply pay the doctors more.

I recognize that my FFS colleagues are not helped at all by an enhancement and advocacy for the FHO approach. And I’m sorry. I obviously think there’s a lot of work that could be done to improve FFS rules and individual payments. No doubt.


But we actually have the evidence that the FHO saved family medicine when it was introduced. It was stunningly effective, and if nursed back to health, will absolutely work again.

Sunday Snippets – November 3, 2024

Another in a weekly series of brief snippets of health care stories that bemused, intrigued and otherwise beguiled me over the past week along with my random thoughts on the matter.

Item: AI is now inventing things no one ever said. It turns out that AI can “hallucinate” (no really, that’s what they are calling it). Apparently the AI invents commentary that includes things like racial comments/violent rhetoric (!) and even medical mis- diagnoses.

My thoughts: My group is actually looking at AI to help with our Admin burden. While the technology shows promise – this is a useful reminder that we should all read what software generates before logging off. You will probably still save some time, just not as much as hoped.

Item: A new lung cancer vaccine that uses mRNA technology is entering trials. Somewhat ironically, this is what mRNA technology was being studied before the COVID pandemic, and its use for the COVID vaccines. The technology shows great promise to greatly reduce the side effects of cancer treatment, and provide more targeted therapy.

My thoughts: The “vaccine” term is probably going to need refining, because it’s not really preventing lung cancer (which is what most people associate with the term vaccine). Additionally, social media is still awash in mis-information about mRNA technology. So probably better to avoid that term. But at the end of the day I would agree what we are really in a remarkable time for cancer therapy with so many new treatments available. (Still better not to get cancer of course – so if you do smoke – quit!).

Item: Dr. Elaine Ma, a physician who went over and above the call of duty to organize mass vaccination clinics in the Kingston area at the height of the Covid Pandemic is asked to pay back the billings generated during those clinics. (Note I did not say income – Dr. Ma would have used a good portion of those billings to pay staff, supplies and other overheads).

My thoughts: I’ve been (frequently) told I’m too hard on bureaucrats in health care. That I come across as somewhat insulting and “un-presidential” when I complain about them. And every time I think to myself “I really need to take a deep breath and be hard on the problem, not the people” – along comes yet another example of rigid bureaucratic thinking and frankly bureaucratic stupidity that I wind up reverting to my old habits. I will say this, the residents of the Kingston area are a whole lot better off because of Dr. Ma , and the sooner the OHIP bureaucrats get this, the better. As for the OMA’s silence on the matter, it’s pretty disappointing.

Addendum: after writing this blog the OMA has confirmed that they have been helping behind the scenes. I’m glad to hear that they have been helping Dr. Ma, but I would state for the sake of their members that they need to be SEEN to be helping….

Item: The Registered Nurses Association of Ontario blasted the government for not embracing nurses as a central to solving the primary care crisis.

My thoughts: I admire the RNAO for advocating for their members (no really, that’s kind of what a member organization is supposed to do). They’re wrong of course. Using Nurse Practitioners to replace physicians (as opposed to complementing them) will only massively drive up the cost of health care and worsen outcomes. But unlike certain organizations- see above – the RNAO stands up for its members.

Item: Walking pneumonia rates in the United States – and probably Canada – are spiking, particularly in young children.

My thoughts: It’s always awful to see children sick, and as clinicians we should be on the look out for this. BUT – thankfully the vast majority of cases appear to be mild, and if treated appropriately people are recovering. They may have a persistent cough for several weeks – but they are getting better.

Item: Collingwood’s newest physician says that the profession is endangered until the province ante’s up better pay. Disclosure – Dr. Ladda has joined my Family Health Organization and I feel we are lucky to have him.

My thoughts: Read my full blog tomorrow – written by a guest blogger so at least it will be coherent.

Item: A columnist in the Ottawa Citizen basically says that Premier Ford is outsourcing the family medicine problem.

My thoughts: A good friend of mine says it much, much better than I could. “We need the political leadership to step beyond name calling and giving token titles to people to win an election. If you want this province to thrive, rebuild and lead Canada again, it requires more than what we have seen for 20 years from ALL political parties .”

That’s it for this week’s Sunday Snippets. As mentioned above, watch out for a really superb guest blog tomorrow on how to fix family medicine.

Sunday Snippets – Oct. 27, 2024

I was away last week but I’m back with another in a weekly series of brief snippets of health care stories that bemused, intrigued and otherwise beguiled me over the past week along with my random thoughts on the matter.

Item: There was significant growth in the number of physicians in Alberta in the third quarter.

My Thoughts: Alberta is kind of a funny province. There are some very strange goings on with their health care policy. But it can’t be denied that despite all of that, if you provide incentives to attract younger physicians it will help. Having said that, it can all be easily undone if they don’t get on with it and implement the compensation for family physicians they promised, and for some reason appears to be delayed.

Item: The province of Nova Scotia has launched a physicians retirement fund initiative, helping physicians to retire well.

My Thoughts: What’s that you say? You mean ensuring that physicians have peace of mind about their retirement might actually help recruit (gasp!) and even retain (double gasp!!) physicians? Who would have thunk it?? In all seriousness, given the way the Federal Liberal government of our effete Prime Minister really screwed physicians with the recent tax law changes – this is a necessary move and I hope will get copied by all provinces. It really will help improve morale and reduce some of the burnout.

Item: John Richards and Tingting Zhang, from the CD Howe Institute wrote an op-ed in the Financial Post encouraging more use of nurse practitioners since they can “do almost everything an MD can”.

My Thoughts: El Toro Poo Poo. (This is a PG rated blog so that’s all I could get away with). I work with Nurse Practitioners and I have seen them help patients and I firmly believe they have a role in health care. But that role is not to replace physicians. The studies that show they can “do almost everything” are done based on what scope of practice suggests they can do. The blunt reality is nurse practitioners drive up costs and worsen care if used in settings as these characters suggest. The studies that show that NPs are cheaper ONLY look at the actual income an NP gets and compare it to a physicians income, as opposed to looking at the work that is actually done/number of patients seen/and number of tests ordered. The FP article isn’t even fit to be used for toilet paper.

Item: The crisis in Home Care supplies, first reported by Avis Favaro on X (formerly Twitter) continues. Home care nurses are reporting heartbreaking stories of patients buying their own supplies on Amazon since home care couldn’t provide them. Dr. Drew Moore and Dr. Hal Berman should be lauded for going public with their concerns. (I’ve met both of them and they are both mensches).

My Thoughts: I’m old. I’ve seen a lot of government screw ups in my time, especially in health care. But I have yet to see bureaucrats who screw up be truly held accountable and fired. Ever. They just get shuffled off to some other department. It it too much to ask that if someone makes a mistake at their job (and this is a BIG one) they get held accountable?

Item: Quebec is attacking family doctors for some reason. First they suggested they would link people to non-family physicians for care and even remove patients who were “healthy” from their own family physicians. Then they presented erroneous data suggesting that family doctors basically don’t work hard enough.

My Thoughts: There are 9 other provinces and 3 territories that would love to have these doctors.

Item: Penn State Medical Residents unionized, went on strike and got significant benefits (despite being driven off the hospital grounds by hospital security!)

My thoughts: Unionization of physicians is going to happen eventually. Whether through the long gestating Charter Challenge (yes my Ontario peeps – it is still working its way through the courts) or some other mechanism. The younger physicians clearly seem to want this model of representation and at some point in the not too distance future, physicians will be unionized.

Item: The Ontario government announced plans to effectively bar foreign students from attending medical school in Ontario.

My thoughts: My thanks to Am640 News for interviewing me on the topic, and my thoughts on this can be heard below. (This short version – this is populist rhetoric that will do nothing to help with the health care crisis):

My Interview on AM640 About the Current Crisis in Home Care

Was pleased to be interviewed by Ben Mulroney today discussing the current crisis in Home Care in Ontario. Unfortunately, the Ontario Health bureaucrats have really mucked up the process of ordering supplies for vulnerable patients at home, leading to immense suffering for patients at home and their loved ones.

Click below to hear more:

https://podcasts.apple.com/au/podcast/shortage-of-medical-supplies-needs-an-urgent-fix/id1677003384?i=1000673744931

Arbitration Part III: When and How Much Will Docs Get Paid?

Disclaimer: The information is based on my personal analysis and should not be your sole source of information. The payment schedule below is based on what we were told was “PLANNED”. Being a firm believer in “Murphy’s Law“, I would suggest that changes to the below may come at any time. Contact info@oma.org with any questions.

After writing why the Arbitration Award will be bad for patients and doctors, it seems my three loyal readers were unhappy that I couldn’t say when docs would be paid. Being a demure, sensitive, and eager to please sort, I feel compelled to try my best to explain when money is coming.

Once again, my two examples are Drs. Alpine and Valley. Both had 13 years of post secondary education (4 years for a BSc, 4 years for medical school and 5 years for residency). Dr. Alpine does a lot of procedures and can see more patients than he could 20 years ago due to improved technology. Dr. Valley spends a lot of time with intensively sick patients, so she sees the same number of patients as 20 years ago.

What assumptions am I making for the Calculations?

Drs. Alpine and Valley will each provide same number of OHIP services yearly from 2023 – 2026. We have to assume that the entire 2.8 % increase from last year, and the 9.95% award this year will be given across the board (ATB) until April 1, 2025. (The OMA and MOH could reach an agreement on distributing the funds more fairly- but I highly doubt it). We’ll also assume that the schedule for payments the OMA provided at their webinar will be met – I remain very skeptical.

Let’s assume Dr. Alpine billed OHIP an average of $100,000 a month for fiscal 2022/23 and Dr. Valley billed OHIP $30,000 a month. This time period is the base rate for OMA calculations, and hence mine. (Physicians who read this blog can put their average 2022/23 monthly billings into the calculations below to find out their own numbers).

What happened for April 1, 2023 to March 31, 2024?

The OMA and MOH agreed to a 2.8% increase in fees that was to be divided into across the board (ATB) increases and relativity increases. Because the agreement came late, and the OHIP Computers couldn’t be updated (sigh), Drs. Alpine and Valley continued to bill OHIP at the same rate as 2022/23.

What happened on April 1, 2024?

The OHIP computers finally updated to reflect the previous year’s increase. Since the two sides didn’t agree on a relatively formula, the 2.8% was given ATB. Dr. Alpine’s gross income went to $102,800 a month. Dr. Valley’s went to $30,840. Both increases showed up on the May Remittance. Doubtful Dr. Valley even noticed her increase.

What will happen on the Nov. 2024 Remittance ?

Well, finally all the reviewing and rejecting and re-submitting of claims for the year April 1, 2023 to March 31, 2024 will have happened. The computers will then pay the retroactive 2.8% amount of this year to the doctors. Dr. Alpine will get an additional $33,600 (1.028 x $100,000 x 12) on his remittance for retroactive pay. Dr. Valley will get $10,080 (1.028 x $30,000 x 12).

Isn’t there a drop beginning in December 2024?

The increase drops to 2.55% and the funds saved are dedicated to enhancing the Hospital On Call Coverage program (HOCC). Dr. Alpine will now see $102,550 (1.0255 x $100,000 and Dr. Valley will start to get $30, 765 (1.0255 x $30,000).

What happens for the January – March 2025 Remittance Advice?

Allegedly, the OHIP computers will be able to apply the 9.95% increase for this year now (I’ll believe it when I see it). The word “prospective payment” was used in the webinar, but I don’t know what that means. This increase is compounded to the now 2.55% from the previous year. As a result, starting with the January remittance, Dr. Alpine will now get $112,753.73 ( 1.0255 x 1.0995 x $100,000) a month from OHIP. Dr. Valley will be at $33,826.12 a month.

What is supposed to happen on the March 2025 Remittance?

What’s that you say? Wasn’t the 9.95% increase supposed to start on April 1, 2024? So what happened to all that money? Well, according to the OMA you will get a lump sum payment for April to December in the March remittance. Dr. Alpine can expect to see a one time retroactive payment of $89,583. 57 ($112,753.73 that he should have gotten subtracting the $102,800 that he did get, multiplied by 9 months) and Dr. Valley will get $26,875.08. This is in addition to their usual remittance.

OK, What Happens After April 1, 2025?

Well at this point the new ‘permanent’ fees are supposed to kick in. Up until now, everyone has been given ATB increases. Whatever is negotiated or arbitrated, is supposed to start now. However, the base rate will be the 2022/23 rates. In a previous blog, I assumed that we would carry on the process of giving 1/4 of the increase as ATB and 3/4 via relativity. IF this is done (not sure if it will be) then every speciality will get 2.46% (0.7% for last year + 1.75% this year, compounded) plus X percent – with the X varying from speciality to specialty based on relativity.

Let’s assume Dr. Alpine’s speciality got an X=0% and that Dr. Valley’s got X = 17.54%. In that case Dr. Alpine will now get $102,460 a month:

  • $100,000 base rate from 2022/23 x (1.0246 ATB increase + 0 for relativity).

Dr. Valley on the other hand will get $36,000 a month:

  • $30,000 base rate from 2022/23 x (1.0246 ATB +.1754 for relativity).

I imagine Dr. Alpine will be annoyed.

What are the chances of the new fees being ready on April 1, 2025?

Slim to none. Militancy on the part of the MOH and incompetence on the part of bureaucrats in charge of OHIP are two constants as sure as death and taxes.

Um…well what happens to our monthly incomes after April 1, 2025?

I honestly can’t figure that part out (and not for lack of trying). The procedural agreement states:

“Any unexpended portion of the targeted price increases will continue to be paid to physicians as a separate payment on the monthly Remittance Advice until such time as each targeted increase is implemented or unless the parties agree otherwise.” 

This is the part that I think most people have missed (including, frankly, the OMA Board that approved this agreement – and yes I know it was an attempt to get real money in the hands of physicians). It’s one thing to accept 2.8% ATB. But to accept 12.75% ATB (2.55% from last year compounded with 9.95% from this year) is a bit much. You really have to wonder if there wasn’t a fairer way to spend this money, especially with so many Dr. Valley’s struggling. Time will tell what happens here.

Geez old country doctor, all you’ve done is fuzzify the muddification!

I aim to please dear reader. I aim to please.

SPECIAL MESSAGE FOR FAMILY PHYSICIANS ONLY

Those of you who have read my blogs know that I (and many others) are really really upset with College of Family Physicians of Canada for inviting Dr. David Price to be a keynote speaker at the Family Medicine Forum. I view it as a slap in the face to family physicians, given his role on the Ontario Government’s Negotiations Team.

The Ontario Union of Family Physicians would seem to agree with me. They are asking all family physicians to sign the petition below to have Dr. Price removed as a Keynote speaker. PLEASE click on this link to read and I encourage you to sign.

Arbitration Part II: Award Implementation Will Hurt Physicians/Patients

Disclaimer: The information below is based on what a non-lawyer (i.e. me) was able to sort out after reading the OMA and Ministry’s 2024-2028 Procedural Agreement, the OMA Legal Counsel’s summary of the award, and attending the OMA Zoom session on the award. This may not be accurate (and I will correct the blog if more relevant information becomes available). I encourage all OMA members to contact the OMA directly with specific questions (info@oma.org) and not rely on this blog as your sole source of information.

The Numbers

First, let’s again review the numbers (approximated for simplicity).

Physician Services Budget, fiscal year ending March 2024: $16 Billion +

Arbitration Award: 9.95% – approximately $1.6 billion

OMA/MOH agreement on split of funds: 70% ($1.12 Billion) to fee increases and 30 %( $480 million) to targeted programs.

Previous contract (no guarantee this will repeat): 25% of the fee increases ($280 million) would go to across the board (ATB) fee increases for entire profession. The remainder ($840 million) would be distributed on the basis of relativity (giving more of a raise to low earning specialties and less to higher earning specialties). IF this pattern repeats, this equals a 1.75% increase for everyone. Then each specialty would get assigned an additional percentage (let’s say X) based on relativity. Ergo everyone should get 1.75% + X, where X varies from zero (for high billers) to higher (for lower billers).

The Implementation

According to the OMA webinar, the OMA and Ministry have yet to agree how to distribute the award. Mediation starts early October and all of this might wind up in Arbitration in March of 2025. My sense from watching the webinar is they are not close on an agreement.

So what happens to the money for this year? We are all supposed to get a raise now right? Well, that’s when the procedural agreement takes effect. It states (sorry for the legalese):

The Year 1 price increase will be implemented as follows:
a. The entire price increase under the Year 1 2024-28 PSA will be implemented
prospectively as an across-the-board increase to the fee-for-service payments
identified in paragraph 1a above, with a target date of the RA in the month 90
days following the issuance of the arbitration decision, and will flow through to
non-fee-for-service payments as soon as practicable.
b. A lump sum payment equal to the entire increase awarded for Year 1 for the
earlier period from April 1, 2024 through to the implementation date under
paragraph 12(a), will be paid as soon as practicable following the arbitration
award with a target date of October 2024.
c. To the extent practicable, the permanent year 1 non-targeted price increases
will be implemented at the same time as the April 1, 2023, price increases
under Year 3 of the of the 2021-24 PSA i.e. April 1, 2025, and in any event no
later than October 1, 2025. These increases will be calculated on a base of
2023-2024 expenditures …… The distribution as between across the board increases and relativity increases will be determined in such manner as the parties agree or, failing agreement, as the board of arbitration awards….

OMA staff confirmed at the webinar that this is in fact what will happen. They even had a complex schedule of prospective payments/lump sum payments/retroactive payments and so on that left me, frankly in need of high doses of Zofran.

To try and simplify things, let’s look at how this will affect two doctors.

Meet Drs. Alpine and Valley

Dr. Alpine and Dr. Valley both completed four years of an undergraduate degree. They then completed four years of medical school, and each did a five year residency in the field of their choosing. Dr. Alpine was always someone who liked to “do stuff”. He wound up in a speciality that does a lot of procedures and as technology has improved, has been able to treat more patients in a day than his specialty could 20 years ago.

Dr. Valley, who is no less smart, really enjoys patient interaction. She chose a specialty that requires more intensive time with patients, and as such, is not able to see more people in a day than someone in her field could 20 years ago.

With our aging population and increasingly complex health care needs – both Dr. Alpine and Dr. Valley are swamped and have long waiting lists.

Dr. Alpine, was able to bill OHIP $1 million for fiscal year ending March 2024. This represents his gross income, and to be fair, his office has a lot of leased medical equipment, along with staff that he has to pay for out of that $1 million. Dr. Valley billed OHIP $350 thousand for fiscal year ending March 2024. She too has staff and other overhead expenses, but not as much equipment.

What happens to Dr. Alpine and Dr. Valley under the procedural agreement? While the schedule for payments for the award is a convoluted mess, the reality is that for the fiscal year ending March 2025 – Dr. Alpine will gross $1.1 million, and Dr. Valley will gross $385,000.

Now the OMA states that the goal is to have new permanent fees in place based on relativity and targeted funding for April 1, 2025. The ONLY way this could happen is if the government negotiations team completely capitulates its positions in the next couple of weeks. Seriously people, the schedule shows that if there is no agreement this thing goes to Arbitration in early March 2025. IF that happens, it’s part and parcel of Arbitration for the 2-4 years of the contract. So the Arbitrator probably won’t even make a ruling until September 2025. Then another six months to re program the ancient OHIP computers and while the fees may be retroactive to April 1, 2025, you likely won’t see the money until Spring 2026.

Let’s assume that the arbitrator follows the precedent set where 1/4 of the increase ( $280 million) should indeed be ATB, and then distributes the rest based on relativity. And let’s assume that Dr. Alpine’s speciality was assigned an X of 0% and Dr. Valley got an X of 18.25%. Therefore Dr. Alpine for the fiscal year ending March 2026 will gross $1.0175 million – a reduction of $82,500 dollars from the year before. While Dr. Valley will get bumped to $420,000.

No matter how often the OMA reminds people that the increase for the first year is one time only, and NOT a permanent increase, the reality is that many members will have budgeted around their increase, and Dr. Alpine will, be very miffed at a $82,500 reduction in income for doing the same work.

But it’s not all that great for Dr. Valley either. She will have missed one year of a substantial increase that should have gone to her earlier. Not only that, but her offices cost pressures and admin workload have been skyrocketing. She needs the stability a relativity based formula provides right now, not in March of 2026.

Because of the delay in stabilizing her practice, she actually chose to leave her practice and do a different kind of medicine. Her patients now have to go back on a waiting list, and who knows when they can find someone to take over their care.

I understand why this procedural agreement was put in place. It was to ensure that doctors got a much need cash injection sooner rather than later. But unfortunately there are unintended consequences of this and those are coming to fruition. Specialists like Dr. Valley who need the relativity increases right now will not be able to hold out and may leave their practices. Dr. Alpine will be understandably miffed at the yoyoing of his income.

And all of this uncertainty will do nothing to help the health care system.

The Arbitration Award: The Good, The Bad, The Ugly

On Sep 12, Ontario Medical Association (OMA) Board Chair Dr. Cathy Faulds announced that the Kaplan Board of Arbitration awarded Ontario’s doctors 9.95% for the first year of their Physicians Services Agreement (PSA).  Sounds straightforward right? Nope – it’s actually ridiculously complicated.

I’ve looked at the award.  I may have some of this wrong (copious documents found on the OMA website induced catatonia, hypersomnolence and cluster headaches).  But this is my take.

A simplified (I have a small brain) set of numbers first:

Total award:  10%, approx value $1.6 billion dollars

Amount for general feel increases: 7% or $1.12 billion dollars

Amount for “targeted funding”: 3% or $480 million dollars.

In the past the OMA and Ministry agreed 1/4 of the raises would be across the board, the rest done with “relativity in mind”.  IF we do that again then $280 million (1/4 of $1.12 billion) will be in across the board increases.  Every specialty would get a 1.75% raise. The rest of the money ( $840 million) would be for raises based on relativity. So all specialties would get 1.75% + X as a raise.  The “X” would vary. It would be more for low income specialties, and the X would be lower or even zero, for the high income specialties.

The Good.
There’s a raise.  The MOH Team stated that Bill 124 should not impact the deal. The arbitrator disagreed and felt that we were unfairly treated because of Bill 124 stating:

“Bill 124 directly impacted the bargaining even though physician compensation was not subject to its terms.”

Hence, the MOH Team completely lost their argument that there should be no redress, and there was a 6.95% redress given.

There was a recognition that family practice is in crisis.  In his ruling the Arbitrator said:

“We accept on the evidence that there is a physician shortage. Somewhere between 1.35 million and 2.3 million people in the province are not attached to a family doctor. These are real numbers. The Ministry’s own documents – which we ordered disclosed–demonstrate that there is a problem to address.”

The arbitrator had to order the Ministry to disclose this?? Jeez. Additionally, the Arbitrator noted:

“Clearly, more family doctors are needed as are more doctors practising comprehensive longitudinal medicine…..it is obvious that the citizenry is ageing – the Government acknowledges this brings with it increased complexity…”

Contrast this with the Ministry’s absolutely laughable position that there is “no concern” about a shortage of doctors.  This is frankly a warning shot, and a welcome one, to the MOH’s negotiations team to not say such stupid things again, and to change their position in future rounds of negotiations.

In another shot to the now obviously inept MOH Negotiations Team, the Arbitrator agreed that admin burden also needed to be addressed with, you know, money. He stated:

“We have reached the conclusion that targeted increases – not necessarily baked in – should be allocated to the reduction and redeployment of administrative work that can best be performed by others or through digital or other measures.”

Finally, It was quick.  OMA Board Chair Cathy Faulds had told us not to expect an award until the end of September.  Who knows why Kaplan put the award out so quickly.

The Bad.

This will not be enough.  The OMA asked for a 22.9% increase. They got less than half of that. This is not really the big win the OMA is portraying it as.

A 10% increase in gross billings for family medicine will not be enough to stop the haemorrhaging of doctors from comprehensive family practice. The “X” for family medicine (see above) needs to be high, and much of the targeted funding needs to go to family medicine too.

And, while it’s true that the Arbitrator recognized there was a crisis in family medicine, the award given did not really do anything in and of itself to stabilize family medicine.  It’s true that was not part of the scope of the arbitrator for this round (this round was for a fee increase). The fact that some practical guidance in how to resuscitate family medicine is missing is still bad for all Ontarians.

The Ugly

The implementation of this award is going to be a nightmare.  As I write this, there is no indication that the MOH and OMA have agreed on how to divide up the $1.12 billion in general fee increases based on relativity.  In fact, indications are that the MOH will continue to fight the methodology, meaning it could be a very long time before fee increases for specialties are set.

Worse, the OMA and MOH have not been able to agree on how to distribute the $480 million in targeted funds.  Which means….more mediation and arbitration.  I continue to concede that the OMA states arbitration and mediation will be done by mid- March 2025. I continue to not hold my breath.

Even uglier is that one solution being proposed would be to give “everyone” a 9.95% increase right now, until the relativity and targeted funding is sorted out.  But that would mean that some of the higher paid specialties would see a 9.95% for a bit, only to have a relative cut once the final fees are sorted out (also to be arbitrated by March 3-7, 2025).  No matter how you message this to warn people – this will cause problems when people see a decrease in income after a rise.

All of which means that the retroactive pay for this year may not come for over a year. If you are a physician who has some decisions to make (eg do you renew the lease on your office at the higher rates the landlord is demanding) – you are going to be awash in uncertainty.

The ugliest part of all of course, is that a bunch of lawyers are going to get really rich as their billable hours go through the roof during this process.

There is a better way.

The government’s main concern should be about expenditures. That decision has now been made for them.  The PSB will go up by $1.6 billion.  That money will have to be paid one way or another.  

The government can now, especially after being told off by the Arbitrator back off from their polarizing and obstructionist path, accept the OMA proposals for implementing the award. They cover what the government states it wanted (pay lower paid specialist more of an increase than higher paid ones).  They also covers issues around admin burden which the Arbitrator acknowledged exist, and the shortage of family physicians (which the arbitrator also acknowledged). 

The total amount spent by the government is going to be $1.6 billion regardless. Getting rapid agreement on the distribution of those funds will decrease the uncertainty about how much goes where and will shorten the time it takes doctors to get paid, which will stabilize the health care system.

Then, for the love of Allah/God/Yahweh/Great Universal Consciousness – the government now needs to realize that you can’t fix health care without working co-operatively with your doctors.  Go look at other provinces. Copy them and get a fair deal for years 2-4 of this agreement.

Or the government can continue to obstruct, obfuscate, delay and impede any real progress towards working together with more protracted, internecine mediation and arbitration. The ball is in their court.

What should doctors do?

The above represent my personal interpretations of the documents I read. I encourage all Ontario physicians to register for the OMA live session on Tuesday Sep 17 from 7:30 – 8:30 pm to hear more details about this agreement.

Never Ending Arbitration a Sign Government Does NOT Want to Work with Doctors

News Item #1: Prince Edward Island agrees to a contract with its doctors. Amongst other things, the deal recognizes that family medicine is a specialty (finally!) and increases compensation to reflect that. It also introduces strong measures to reduce red tape and administrative burdens, and adds what appear to be retention bonuses. PEI joins British Columbia, Manitoba, Saskatchewan and even Alberta (!) in working co-operatively with their doctors.

Dr. Krista Cassell of Medical Society of PEI with Health and Wellness Minister Mark McLane and Health PEI CEO Melanie Fraser

News Item #2: Ontario Medical Association (OMA) Board chair Cathy Faulds announced last week that the Kaplan Board of Arbitration will not deliver a ruling on the fractious contract dispute between Ontario’s doctors and the Ministry of Health (MOH)at the end of August as expected. It is delayed until at least the end of September, if not longer.

Now you, dear reader, are probably wondering why I refer to a one month delay as “never-ending”. Firstly, because I’m not convinced it’s only one month. I don’t recall the Arbitrator ever giving us a timeline for when he was going to give a decision when I was on the OMA Board. Timelines for meetings and hearings, sure – but for the decision, no.

But more importantly, even if there is a ruling in September, it’s nothing but a mere step in a protracted, convoluted process that, at the end of the day, does nothing more than show that the government would rather not engage the OMA in providing solutions for our health care crisis. To understand why, one needs to first appreciate the prolonged nature of the current arbitration process, and just how tortuous it is. (I will do my best).

First, the current arbitration process is ONLY for one PART of the first year of what is supposed to be a four year contract. It will cover April 1, 2024 to March 31, 2025. BUT, it will only cover a percentage increase for that one year. It will not set specific fees for different specialties. Instead, there was general agreement (last I heard) that 70% of the increase would go towards fee increases and the other 30% would go towards targeted areas of high need.

Sounds simple enough to sort out right? If the deal is worth, say $2 billion (this number is totally made up and Mr. Kaplan, if you are reading, this number is much less than the increase should be), then $1.4 billion would go towards fee increases, and $600 million would be targeted towards areas of need.

The problem is that the fee increases are to be distributed along what’s know as a “relativity model”. Essentially lower paid specialists are to be given a bigger raise than higher paid ones. Unfortunately, the OMA and MOH can’t agree on how those raises are to be distributed amongst the various specialties. Worse, they can’t agree on how to distribute the 30% that was earmarked for “targeted funds”.

Which means…..you guessed it, ANOTHER round of arbitration with yet another set of decisions to be ruled upon by the arbitrator. This additional protracted process won’t begin until the arbitrators first ruling and further negotiations and mediations. The information on the OMA website suggests arbitration for those issues won’t happen until March 3, 2025.

But wait, didn’t I say that this was only for the first year of the four year contract? Why yes, yes I did. Which means that after this, we now start arbitration AGAIN for years 2-4 for the doctors contract. And yet again, not only do decisions needed to be made on the percentage increase, but on how that increase is divided up. Which means…….potentially many more rounds of arbitration.

I would concede the OMA websites suggests all of the year 2-4 arbitration, and left over issues from year one can be done at the same time (March 3-7, 2025). However, I will refrain from betting the mortgage on that actually coming to fruition. We are one early election from this timeline being thrown into chaos. The cynic in me thinks that by the time arbitration is all done for this supposed four year cycle, it will be time to start negotiating (and yes more arbitration!) for the next four year cycle.

The government will most likely abide by the initial arbitration award (it’s doubtful they would reject an award prior to an election call). Ontario Health Minister Galen Weston Sylvia Jones will frame this as part of the process for coming to an agreement. She will (probably) claim that by abiding by the award the government is “working with” physicians to benefit the health care needs of the province.

She will be wrong.

I’ve mentioned this before, arbitration is preferable to the days when governments could unilaterally cut physicians income at the whim of the health minister. However, that doesn’t change the fact that arbitration should be viewed as a necessary evil, with emphasis on the evil. Not only can it demoralize people who are going through it, the spill over effects have wide reaching consequences.

What does this mean for the general public? The OMA has come up with some solutions for the various crises our health care system is facing (2.5 million without a family doctors, worsening health care catastrophe in Northern Ontario, overwhelming bureaucratic burden etc). The reality is that many of the solutions require changes that need to be made in a contract with Ontario’s doctors. But we don’t have one, so none of these will be implemented.

Instead of working co-operatively with the OMA to come up with solutions in a fair contract, the current government seemingly prefers to leave it all to the arbitrator. And as a result, patients will continue to suffer.

The government of Ontario has a choice. Follow the lead of BC, Manitoba, PEI and so on and work with the doctors to help patients. Or set up a perpetual conflict with them.

Over to you Minister.

Ontario Health Minister Sylvia Jones, who can start to fix things tomorrow, if she wants.












