How To Vote By Proxy at the CFPC Annual General Meeting

On Wednesday, October 28 2026, the College of Family Physicians of Canada (CFPC) will hold its annual general meeting (AGM). There will be a number of important motions for discussion. I will say, however, that the CFPC, like a lot of representative medical organizations, often suffers from a lack of engagement from the broader membership. It seems that engagement only goes up when organizations do something to upset members, like trying to implement a third year of the residency program without a member vote.

This is unfortunate. Physician members’ organizations would benefit greatly if only it was easier for physicians, given their overwhelmingly busy lives, to get engaged in a meaningful way with those organizations. Emphasis on easier.

Hoping to make the CFPC stronger , Drs. Conte, Dubord and I have proposed six bylaw changes. We genuinely feel this will make the CFPC more democratic, transparent, and accountable. It would be foolish to suggest that simply passing these motions will fix the CFPC. There is no fixing of membership-driven medical organizations, there is only ongoing supervision and treatment. But passing these six will allow members to keep an eye on the CFPC.

The response from the current leadership of the CFPC seems well intentioned. However, a deep dive into the minute package shows a fair bit of institutional groupthink.

For example, according to their AGM Meeting Materials:

“Upon receiving the proposals, management invited the members to work collaboratively to address certain noted concerns with the proposals. The members declined, opting for the proposals to be presented to the membership as originally submitted.”

We suspect what the leadership meant was that we chose not to co-operate in the way that the leadership wanted us to. Dr. Dubord had clearly sent a response back asking for specifics about the legal concerns. The CFPC replied on Aug 12 it would not lay out legal concerns and hasn’t specified these concerns in the meeting package. Not sure how to co-operate given this.

The leadership of the CFPC says that our six motions are based on good ideas and a positive desire to transform and improve the CFPC. I thank them for recognizing that. They state they want something similar, and have proposed alternative motions, which they feel are better. I thank them for putting the time and effort into developing alternative suggestions.

Unfortunately, when unpacking their proposals with a moderate degree of scrutiny, many loop holes become apparent. The potential for none of the changes we want to be implemented in a meaningful way exists. The CFPC leadership has made it clear if both our motions and their 5 alternatives pass, then their alternatives will take precedence. In our view, their alternatives lack the bite of our six motions.

For example, the first motion is for the membership as a whole to elect their president. The board instead is offering board-recommended picks. This essentially means that the board can still choose who runs for president. My guess is that the CFPC is scared that someone ill suited for the role will be chosen.

But if we look at the Ontario Medical Association (OMA) – as part of their governance transformation, they realized that members had to decide who the most visible person on their Board was. The OMA has been holding member wide elections for president since 2018 (initially non-binding) and it was really only in 2018 that some uncouth, obnoxious, ill mannered lout was chosen to be President-Elect. The rest have all been pretty reasonable people.

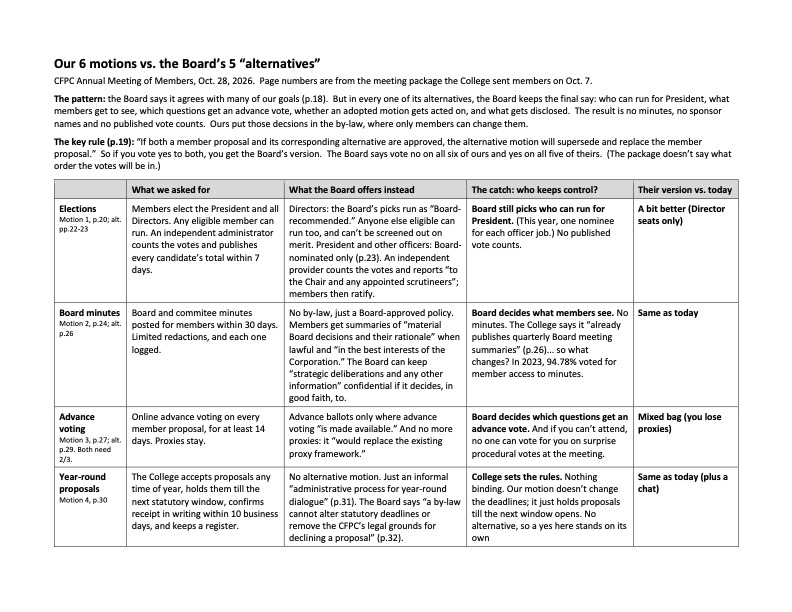
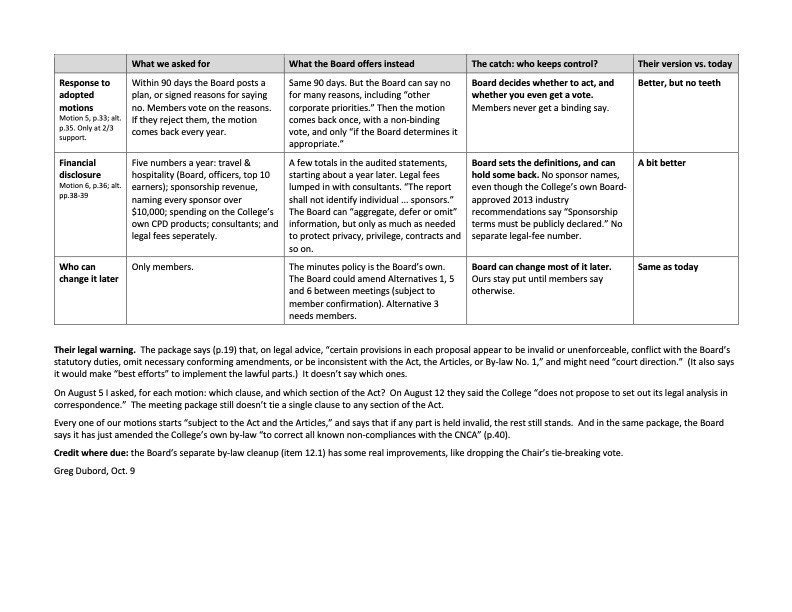
Similarly, our second motion called for board and committee minutes to be posted, but instead the board is just offering summaries (no change). Our third motion codifies online voting (which will increase engagement!) whereas the Board wants to pick and chose. Our fifth motion demands a 90 day response, time while the Board’s doesn’t have the same teeth to enforce. And the motion on financial disclosure we propose is much stronger than the Boards alternative.

Here’s a chart with a nice summary of the differences in our motions and the Boards alternatives (a larger version can be downloaded here):
Here are the steps you need to follow if you support our motions:

First search your email inbox with the phrase “CFPC”. This should identify all the emails from the CFPC you have. Go to the email dated on October 7, 2026. That one will have a link to register, personal information and your control number. Then do the following:

1. Log in at: election-client.ca.electa.lumiconnect.com/cfpc/proxycard/ with their email and the control number from the College’s Oct. 7 email. NEVER send your control number to anyone else.

2. Item 1: Appointing a proxy. The default options are Board officers. Pick the middle option and type: Paul Conte. He has graciously agreed to hold proxy votes. He has set up an email just for proxies: paul.cfpcproxy@gmail.com

3. Items 2 to 9: This is all CFPC business. Vote as you see fit. As an FYI Item 5 approves keeping the fees where they are.

4. Item 10: This is the CFPCs own package of needed bylaw fix, and I support these and encourage you to support them too.

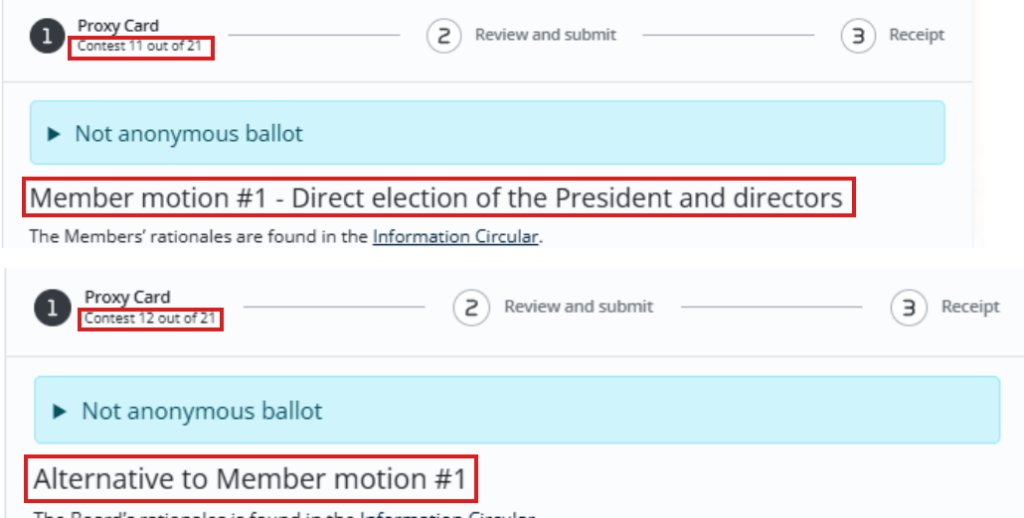
5. Items 11 to 21: I ask that you approve every Member Motion (Items 11, 13, 15, 17, 18 and 20). It is ESSENTIAL to REJECT EVERY Alternative Motion (Items 12, 14, 16, 19, 21). NB. The Proxy Card refers to these as CONTESTS, NOT ITEMS. However, the numbering system still stands. Vote YES on 11, 13, 15, 17, 18 and 20. Vote NO to 12, 14, 16, 19 ,21. Remember, if the alternate motion gets accepted, it will supersede the six member motions, and no meaningful change will occur. You should see something like this:
5. Submit by Oct. 25 at 11:59 p.m. ET. Before you do, turn on vote verification on the review page.

Some of you may disagree with the six motions we propose and support the CFPC Board. That’s fine. Healthy tension and disagreement is vital for any organization. But what’s not fine is for members to ignore this issue and NOT vote, particularly since you can appoint a proxy. (A proxy HAS to submit your votes the way you want, even if the proxy disagrees with you).

I truly hope that first and foremost, every member of the CFPC takes the time to vote. A healthy vote count means members want the CFPC to be better and sends a strong message as to steps that can be taken to achieve that goal.


A Tale of Two Charter Challenges

Authour’s note: To paraphrase the original old country doctor, Leonard “Bones” McCoy of Star Trek fame, I’m a doctor, not a barrister. The following represents my understanding of the legalities in the Charter Challenge, and should not be taken as gospel. For more detailed questions, email the OMA: info@oma.org

The original Old Country Doctor, Leonard “Bones” McCoy

Last week, the Ontario Medical Association (OMA) held an online webinar updating members on the status of its excruciatingly long gestating Charter Challenge against the government of Ontario. The Challenge was initiated in 2015 after the repugnant unilateral actions of the then governing Liberals. Ironically enough, last week the Ontario Nurses Association (ONA) also informed the public that they were moving forward with their own Charter Challenge.

On the surface, it would seem that the Challenges are about the same thing. Both argue that the government has too much power. Both rely on the Charter’s protection of freedom of association. Both say that meaningful collective bargaining requires more than simply sitting across a table and talking.

But there is a crucial difference.

The OMA’s Challenge

In 2015, the disastrous duo of Health Minister “Unilateral” Eric Hoskins, and Premier Kathleen “No-Wynne” claimed the absolute right to impose changes to physicians compensation. The OMA, through the Challenge, made a pretty straightforward argument. If a government could impose compensation, and physicians were unable to strike to protest, the two sides do not have equal bargaining power. A meaningful way of resolving an impasse was needed. The OMA’s Challenge argued that the Charter’s protection of freedom of association requires an effective dispute resolution mechanism. It further argued that a Binding Arbitration Framework (BAF) is that mechanism.

The Supreme Court had just handed down a decision in the Saskatchewan Federation of Labour case that recognized that the right to strike for non-essential services is constitutionally protected because it can be an essential component of meaningful collective bargaining. This seemed to be very supportive of the OMAs position that an alternate mechanism is therefore required for essential workers like physicians who can’t strike. However, the Court did not say that every group deprived of the right to strike must automatically receive binding interest arbitration. That distinction matters (more on that later).

Eventually of course, Premier “No-Wynne” realized how inept her health minister was as the system was collapsing under his watch. She forced him to give doctors a fair BAF even though he was on record as opposing it. The OMA’s Challenge shifted from asking the Supreme Court to impose a BAF, to asking the court to recognize that physicians have a Constitutional entitlement to a BAF, so that no incompetent Premier/Health Minister could take it away in the future. (I guarantee you that at some point in the future, some bumbling government will try to do this).

Former Health Minister Eric Hoskins and Former Premier Kathleen Wynne

The Nurses Charter Challenge

In contrast, Ontario’s nurses have had access to arbitration for over half a century. The Hospital Labour Disputes Arbitration Act (HLDAA) of 1965 states clearly that when collective bargaining reaches an impasse with essential employees, disputes are sent to binding arbitration. This was meant to prevent strikes and lockouts. (Physicians are considered independent contractors, so HLDAA does not apply to us).

The nurses are arguing that this is NOT enough. Their argument appears to be that taking away a worker’s most important bargaining weapon (the right to strike), and enforcing compulsory arbitration doesn’t make the system fair. Essentially, if employers know employees can’t strike, there is less incentive to compromise. They will just send everything to arbitration. This removes too much bargaining power according to the nurses.

ONA says that this is particularly problematic when the issues being negotiated are not simply wages, but staffing levels, working conditions, patient safety and the ability of nurses to provide appropriate care.

ONA is not saying arbitration is bad, just that being forced into it without both sides agreeing is bad.

What has the Supreme Court Been Up To?

Since 2015, the Supreme Court has continued to develop law around freedom of association and collective bargaining. It has made clear that meaningful collective bargaining is constitutionally protected. It has also recognized that the right to strike can be an essential part of that process.

But there is an important limitation.

The Court has suggested that the Charter does not necessarily guarantee a particular bargaining system. It protects the ability to engage in meaningful collective bargaining, rather than guaranteeing that negotiations must occur according to the precise system preferred by a union or professional association.

Which really is where the difficulty lies for the OMA. The Court would likely say that there must be a fair negotiations process, but may not impose the preferred option. They may also say – “well, doctors have a BAF now, come back to us when some future government unilaterally rips it up, and we can discuss it then”.

Supreme Court of Canada

The Other Issue

ONA represents employees in a conventional unionized labour relationship. The OMA represents physicians who, for the most part, are independent contractors rather than employees of the Ontario government. That distinction could become important in court. Not sure how, like I said, I’m doctor, not a legal expert.

The Irony

That is what makes these two Charter challenges particularly interesting.

The OMA is saying: “We need constitutionally protected binding arbitration because we don’t have enough bargaining power.”

The ONA is saying: “We don’t have enough bargaining power because we are forced into binding arbitration.”

However

The cases are connected by the same fundamental question. Exactly how much constitutionally protected bargaining power are representative organizations and people entitled too? That is why these two Charter challenges deserve to be watched together (assuming the OMA carries through). They may ultimately tell us something much bigger than whether nurses can strike or whether doctors are entitled to arbitration. They may define how much bargaining power the Constitution requires when the government is on the other side of the negotiating table.

And in Ontario’s publicly funded health-care system, that is a question with consequences far beyond the courtroom.

Addendum:

For physicians in Ontario, it does appear that the OMA is laying the groundwork to stop pursuing the Challenge. There may be many good reasons for that (wait till a government takes away BAF and fight the issue then for a better chance of success). I encourage you to check out the recorded version of the OMA webinar on the Charter Challenge, and to fill out the survey on the member survey on the issue.

Re-Post: Dear Premier Wynne, It’s Not Too Late To Fix Health Care

Old Country Doctors Note: This blog originally appeared in the Huffington Post on May 9, 2016. I’m re-posting on my own website so that I can keep it for easier future reference.

The Right Honourable Kathleen Wynne

Premier of the Province of Ontario

Dear Premier Wynne,

So I hear you are thinking of proroguing the Provincial Parliament, likely as a prelude to a cabinet shuffle in the hopes of raising your incredibly poor poll numbers. 

While there has been no shortage of scandals for your government, the reality is the biggest issue facing you is health care. If you can fix that, then maybe, just maybe, you can pull out a victory in 2018. What’s that you say? If that’s the case, stop writing articles about how bad health care is and start offering suggestions instead? Glad you asked! Here’s how you can fix health care in seven easy steps.

Since I’m limited to 1,000 words or less on my blog post, I will give you four steps this week, and next week, we will go with steps five through seven.

1) Order an administrative review of the senior management at the MOHLTC

Start right from the top (Deputy Minister Bob Bell) and include the rest of the senior management team. There’s a real problem with morale in Ontario Health Care. Last year, Ted Ball from Quantum Transformation Technologies did a survey of health care leaders that showed damming results for just how little faith they had in the leadership and direction of the MOHLTC. 

Between 50 and 70 per cent of responses were in the “Poor to Fair” categories for virtually every single question. In addition, in the comments section there were repeated calls to cut down on the bureaucracy (and this from bureaucrats!). One exasperated person simply extolled “Just do something!” This is abysmal.

Since then, a new vision, Patients First, was introduced by Health Minister Eric Hoskins. Quantum did another survey after this, and the results were worse! Amongst other deplorable numbers only 20 per cent of health care leaders have confidence in the MOHLTC to manage the enhanced LHIN’s proposed in the document.

Additionally, in the comments section, the top adjectives used to describe the managerial/leadership capacity of the MOHLTC were words like “uninspired,” “obstructionist,” “incompetent,” “autocratic” and a plethora of similar negative terms.

The people of Ontario pay a lot of money through their taxes (in the case of Bob Bell, $426,535 according to the Sunshine List) to ensure health care is run properly. It’s not happening. A formal administrative review can give the leaders some good advice as to how to encourage other leaders to follow them. It’s sorely needed.

2) Read Dr. Shawn Whatley’s blog on health care bureaucracy in Canada

Make sure you read all the excellent links. Memorize all the data that’s there. Keep those figures at hand, as you will need them when you try to push through the next set of changes you need to make. 

[In 1995] people realized that in a universal health care system, cutting payments to doctors equals cutting services to patients. They will realize this in 2018 as well.

3) Get rid of multiple ‘arm’s length’ agencies

Look, every time you create an “arm’s length” agency (e.g. Cancer Care Ontario), that agency has to create an administrative bloat. Things like policy and procedure manuals, human resource departments, various administrative levels and so on. In health care, the problem is that all of these agencies have to report to the MOHLTC (who funds them). The MOHLTC, of course, has a policy and procedure manual, human resource department, administrative levels and so on. What’s worse is that the MOHLTC has departments solely dedicated to liaising with all these other external agencies.

For example, the Gordian Knot that is the MOHLTC organizational chart, clearly shows that there is an eHealth strategy and investment branch of the MOHLTC. Their job is to liaise with eHealth. So, why not just bring in eHealth into the MOHLTC and get rid of the redundant bureaucracy?

Now, I get that politically, the goal was to try and have these agencies take flak when things go wrong, so that bad news won’t stick to the health minister. But guess what, it’s not working anymore. People won’t blame Cancer Care Ontario for the stem cell disaster in the 2018 election. They will blame YOU.

So, get rid of the LHIN’s, eHealth, Health Quality Ontario, Cancer Care Ontario, CCAC and a whole bunch of others. Bring them all into the MOHLTC so you don’t need multiple HR departments and policy manuals. This is why mergers and acquisitions are in vogue in the business world. Go with it.

4) Offer binding arbitration to the doctors.

Like it or not, you can’t make a fundamental transformation to the health care system without the help of the doctors. Even though I didn’t like it much, I understood the political rationale behind trying to shame them into coming back to the table by attacking their billings. Problem is, it didn’t work. People believed their doctors, not your political stunt. 

As an aside, go back to the last time an government cut payments to physicians (Bob Rae’s NDP government of 1990-1995). Go dig up their election ads. They all started with “Bob Rae has cut payments to doctors.” The thought was to portray to the public that by cutting payments to doctors, there was more money for other services. Sound familiar?

See how he did in the 1995 election (hint: it wasn’t pretty). People realized that in a universal health care system, cutting payments to doctors equals cutting services to patients. They will realize this in 2018 as well.

Giving binding arbitration to physicians puts YOU in a no-lose situation. If the arbitrator sides with physicians, you can say to the public that you have no choice but to go along with it, as it’s part of a collective bargaining process. If the arbitrator goes sides with the government, the physicians will have gotten what they asked for, and will have to go along with whatever settlement there is.

Either way, you then have physicians re-engaged in the process of transforming health care which is an engagement you badly need.

Yours sincerely,

An Old Country Doctor

Wasaga Beach’s Much Needed Nursing Home Reveals Haphazard Government Bureaucracy

Recently, the Ontario government announced a hundred million dollars of new funding towards a new, 288 bed nursing home in Wasaga Beach. What’s really impressive is that the project is already ready to put shovels in the ground. Construction is expected to begin in late 2026, and it’s anticipated that the first residents will be welcomed in 2029. This will become the largest nursing home in the South Georgian Bay region.

To be abundantly clear, Ontario does need more nursing home beds. In 2017, I wrote about the then desperate need to build 35,000 nursing home beds. For reasons that I can’t fathom, the previous Liberal governments never really did anything to build up healthcare infrastructure, despite the fact that we had a growing and aging population. That particular government seemed to think that the healthcare needs of the population would simply fix themselves.

I’ve been critical of some of the things that the current Conservative government has done in health care, but they do deserve credit for significantly ramping up healthcare infrastructure builds. Whether it’s new hospitals being built, new equipment like MRIs being purchased, and yes, finally building new nursing homes, this particular government has recognized that you simply can’t provide healthcare to an aging and growing population without increasing the capacity of the infrastructure.

However, I continue to be frustrated by the fact that a government whose leader is famous for having made extremely critical comments of overlapping and haphazard bureaucracy, hasn’t done more to get the various facets of the healthcare system to be streamlined and work together.

The Wasaga Beach Nursing Home (as much as it’s needed and should be built) is a perfect example of this.

Nursing homes, by definition, have complex patients with significant health care needs. Some of them, will get sick and will need to be transferred to the nearest hospital Emergency for assessment. For Wasaga Beach, this means the Collingwood General and Marine Hospital (CGMH). Being complex patients with multiple health needs, some will be admitted to hospital.

However, as of 2024/25, the CGMH already showed over 39,000 ER visits (up 8% from the year before!) Their inpatient status showed overcapacity for the entire fiscal year. All hospitals have fluctuations and times where they are more full than others, but to be overfull for an entire fiscal year is extra ordinarily busy.

How much more stress will be added to the CGMH by the new nursing home?

Trying to find reasonable data is painfully difficult. I searched a number of sites, but the best that I could come up with was a 2018 analysis. Yes, there was fluctuation during Covid, but we are back to pre-Covid numbers. Crunching a lot of numbers (so that you, dear reader, don’t have to) gives the following, what I consider to be reasonable, projections:

  • The CGMH can expect about 160 ER visits per year from the new nursing home. These patients are very complex so their ER visits will take much longer. (By comparison, 288 seniors who live independently in the community would only result in 58 ER visits per year).
  • Given that just under half of all nursing home patients who go to the ER wind up getting admitted to hospital, we are looking at about 75 more admissions to hospital per yer.
  • It was even tougher trying to find out how long patients who are admitted to hospital from a nursing home will stay in hospital. That link above had some information, but hardly enough to be accurate. The best guess I could come up with was between 5-7 days per admission, so if we go with 6 days in hospital on average, we’re looking at about 450 days in hospital per year.

Now let’s keep in mind that the CGMH is already full. We no longer have hallway health care. We have chair health care (the hallways are full). So where are these patients going to go? (N.B. I do appreciate that there might be some relief as some of our hospitals Alternate Level of Care patients will now have a nursing home to go to – but I’m going to make an educated guess that the stress on the hospital will outweigh the benefit).

My three loyal readers might be aware of the fact that Collingwood is getting a new hospital. Once again, kudos to the current government for approving a badly needed new facility. However, there are still a bunch of bureaucratic approvals needed, and shovels won’t go into the ground until at least the fall of 2028. Hopefully, the project will be complete in 2033 (because government run projects always come in on time).

And this is the part that really drives physicians and healthcare workers crazy. Could there not be some common sense in the eyes of the bureaucrats at the ministry of health who approve these projects? If you are able to approve shovels in the ground by this fall for the nursing home, why can’t you do it for the hospital? You know that patients from the nursing home are going to wind up in hospital and stress an already overburdened place. You know that the new hospital’s been approved. Why doesn’t the Ministry of Health co-ordinate the builds? Do these bureaucrats from each department (hospital and nursing home) not talk to each other? (Having been involved in many meetings with many bureaucrats at different branches of the ministry when I was president of the Ontario Medical Association, I can tell you the answer to that is no.)

Overbureaucratization of our health care system has been a problem for decades now. It’s been unrelenting and farcical at times. The Wasaga Beach nursing home, as needed as it is, is just one more example of this. It’s where the real silos exist in health care and our system will not improve until we get a government that is willing to tackle the bureaucracy.

Preparing for the August Covid-19 Wave in Canada

We’ve learned much about COVID-19 since the first infection was announced in 2019. This has helped us develop better treatments and better prevention strategies. We’ve learned that COVID has settled into a fairly consistent annual pattern. There’s a smaller summer wave (end of July to mid-September) and a larger winter wave (November to January). The larger wave ends around the time flu season starts.

This year the summer wave has started in the United States. Wastewater concentrations of COVID are starting to increase in southern and western states (yes they are still low, but they are trending upwards). ER visits with proven COVID cases are also growing in the southwest. So the wave is beginning.

As I write this, the Canadian wave has not yet begun. In particular, the Ontario numbers are still low overall. Local fluctuations are occurring however, and if trends hold as they have done over the past few years, we can expect the COVID wave to start in August, and peak in early September.

The current U.S. wave is due to an Omicron strain of the virus designated as Nimbus. Thankfully, it appears that the Omicron strains cause less serious infections (though may spread more quickly). This means that existing immunity from prior infection and immunizations continue to provide some meaningful protection against severe disease.

With that in mind, what should Canadians do to prepare for this summer wave? For healthy people, I actually think we’ve reached a point where it’s unreasonable to say “avoid COVID at all costs.” With COVID being so widespread and so frequent, our goal should now be to take a risk-based approach.

What EVERYONE Should Do

We all benefit from better air quality, particularly indoor air quality. While all of us love air conditioning, opening windows when practical really helps increase airflow circulation and is very beneficial. Now let’s be clear if it’s an exceptionally hot day, or if it’s a wildfire smog filled day where it looks like the surface of Venus , then obviously the windows should stay closed. But when practical, opening windows is good for air quality.

Make sure you have HEPA air purifiers. I have one in every room in my office. Putting an air purifier in high volume rooms in your home is a good idea.

Social gatherings should also be outside. Fresh air and sunshine – just what your grandmother ordered.

I appreciate this next bit of advice will go over like a lead stone for some people, but I think it’s important that you keep a few well-fitted N95 masks around as well. You can buy these online. I’m not suggesting you need to wear them all the time, I believe we’re past that. However, in the event that a wave hits and you have to go to a crowded environment, or you’re feeling unwell, it’s better to have these ready and available, rather than scrambling to find one at the last minute.

Similarly rapid antigen tests are also useful to keep at home. You can get these from most drug stores. They are unfortunately a little less sensitive for Omicron than they were against the early variants, but they’re still fairly useful. Again, I’m not suggesting you swab every day if you’re feeling well. But if you do develop flu-like symptoms in August, then it’s helpful to already have the tests at home. Please note that a negative test does not completely rule out an infection, especially during the first 24 hours of illness. Doing a second test a day or two after your first test will improve the accuracy of the test.

If you do become ill, then of course, I would hope that you would have the good manners to stay at home. Symptoms of a covid infection are generally the same as most other respiratory illnesses (sore throat, cough, low-grade fever, fatigue). Most physicians now do virtual visits, and so you can still arrange to speak to a physician or video call them if you’ve got these types of symptoms, without infecting their whole waiting room. If you are sick, please have the common decency to avoid visiting people who have significant health issues, as those people, if they get COVID, have a significantly higher chance of deteriorating rapidly.

Get immunized! Most patients should get a yearly Covid shot, generally in the fall. Enough of the clot shot/fakecine/frankenshot/globalist serum/fauci juice nonsense. By Aug of 2024 over 13.7 BILLION Covid Vaccines were given worldwide (including over a 100 million in Canada). None of overwrought, neurotic claims about how we’re all going to die if we got the Covid shots have come true. Protect your self and your loved ones and get an annual vaccine (click here to get your shot).

And of course, there is the same advice that grandmothers have been giving forever. Eat right, exercise regularly, maintain a healthy weight, control your diabetes, quit smoking, take your vitamins (2,000 international units of vitamin D daily and 500-1000 mg of Vitamin C daily would be a good start for Canadians). Doing all of that will not prevent you from getting COVID, but they certainly are associated with a much better outcome if you do get COVID.

What Those Who are Elderly or Have Significant Health Issues Should Do

In additions to the above, significantly ill or immunocompromised patients might benefit in getting a Covid vaccine twice a year. Please discuss this with your doctor. Additionally, knowing that they are at higher risk, they should be prepared to avoid indoor activities with the general public during the coming Covid wave. For example, many grocery stores deliver now, so there’s no need to go shopping. Avoid larger indoor events where possible. If travelling by bus or plane, just go ahead and wear a mask during a Covid Wave. Call your doctor when you first get sick as you may qualify for some of the newer treatments for Covid.

The last word.

This year appears to be trending for a moderate COVID wave as opposed to a severe one in August. If we all take reasonable, cautious precautions, we can hopefully keep it under control.

Innovation Winter

Recently, the Ontario Government announced plans for a province wide family practice record system. I was debating what to write about it when I came across this post from Dr. Shahin on LinkedIn. While I don’t agree with all of it, it’s an important point of view. He’s kindly agreed to allow me to post this as a guest blog, and I encourage you to give his LinkedIn page a read.

Dr. Ilan Shahin is a Family Medicine specialist who serves as the Primary Care Lead for Patient Attachment for the Central West Ontario Health Team (CW OHT). 

He’s also a Board Member and Secretary-Treasurer of the Ontario College of Family Physicians (OCFP), has an MD and Master of Business Administration (MBA) from McGill University and is a co-founder of ConsultLoop, a former e-referral platform.  Basically a whole lot smarter than I am.

Innovation Winter is a Canadian tradition of killing off product categories with the whisper of a large procurement.

Every so often in digital health, governments see small companies sprouting around a category, and decide to procure The Thing for the entire jurisdiction. This is ambitious, well-intended, and comes with its fair share of boosters. E-consults, e-referrals, and e-prescribing all had similar stories. However, these didn’t work out as intended.

E-consults remains a clunky product with uptake well below its potential, when once there was a physician-led startup that offered a nice mobile experience that was much easier to use and even log on to.

E-referrals is still maturing when it’s been 10 years since an original RFP was won via a single LHIN with the thought that it would be rolled out across the province. There too, there was a company (which I co-founded) that built the referral platform at less than 5% the cost of that initial RFP, produced unprecedented and yet unmatched wait time data, and had pilots shut down because of whispers that e-referrals would be deployed imminently across the province.

E-prescribing has the story of Infoway’s landmark project that was shut down after hundreds of millions in spending, with market penetration that was only a few percentage points of total prescriptions despite the virtualization pressure of a pandemic. Setting standards for companies serving the pharmacy market could have harnessed their competitive drives, rather than relying on one platform with its limited agility.

In each case, government comes with good intentions, and tries to build The Thing. In doing so, they create what is effectively a monopoly, which risks insulating the product from market forces that produce better value, and lower costs.

However we don’t need a large procurement to actually have happened, for the monopoly or oligopoly to be entrenched, in order to kill innovation. Just the mere whisper that something big is coming is enough to make rational actors across the system wait and see. This also includes small businesses, which is where the imperative to listen to customers, the urgency to improve, and the competition on price and quality actually lives. Ingenuity lives there too, in the companies facing short cash runways, the incumbent complex, and the need to prove themselves as trustworthy both clinically, operationally, and ethically.

Government has to be careful about what it does to the marketplace when it acts. Sometimes in raising its hand, it ushers in an innovation winter, which has the potential to block far more value in a robust, competitive market, than it uncovers in a RFP-led closed market approach.

Let government focus on building the strongest marketplace, driving to common standards to uplift the market’s value, while ensuring fair competition to harness the cost and quality pressures that come with it.

Market-making. That’s the game. Innovation winters are signs of failure.

Please Don’t Move to the Georgian Triangle (Collingwood, Clearview, Wasaga Beach)

Wait, doc, what’s this all about? You’re asking people not to move to where you live?!?

Yes. Please don’t move to this area.

But you always tell others how wonderful an area this is!

This is indeed true. I love living here. I consider myself very blessed for having come here 34 (!) years ago. We are a few minutes’ drive away from the world’s longest freshwater beach, a few minutes’ drive away from ski hills. There’s golf, boating, too many outdoor activities to list. I enjoy the trails myself and often bicycle to my office during the warmer months. A true four seasons resort area.

Is the problem the people?

Not at all. The people here are kind, generous and extremely supportive. Plus there’s an old farmers mentality in a lot of them (that’s a good thing). I’m grateful they have allowed me into their lives. It’s an honour to help them.

Is the problem the growth in the area?

I’d be lying if I said I was completely happy with the increase in the population over the past ten years. The towns have gotten quite crowded, and the roads are busy. Bicycling on the roads is now classified as a survival sport. And yes, I have seen traffic jams, which is something I never thought I’d see. But no, that’s not it exactly.

Okay, doc, you’ve got me really confused. What exactly is the issue then?

It’s the healthcare system.

That makes no sense. You’ve often talked about how proud you are of the fact that you were the inaugural chair of the Georgian Bay Family Health Team, and how closely the doctors in the area worked together to form a really cohesive medical community.

This is true. The Georgian Bay Family Health Team, under the leadership of their Grand Poobah (inside joke), Maria LaRose, is, in my opinion, the best health team in the province. The doctors and allied health care staff all work well together. We formed the first community wide Electronic Records system in the Province. It’s still the only one in Ontario that is integrated with other health care partners. It’s the best medical community in the province.

Building with the GBFHT Main office

Okay, so is it the hospital? Goodness knows you’ve had issues with administration in the past.

Actually, we’ve been very fortunate to have better administrators at the hospital the last couple of decades. The nursing staff and other allied healthcare professionals (physiotherapists, occupational therapists, pharmacists, respiratory therapists, and so on – apologies to those I missed) really are excellent and hardworking as a team. They really want to help patients. The problem, of course, is that they are overworked.

Collingwood General andMarine Hospital

So then your issue is with the capacity of the local healthcare system?

Exactly. You see, currently, we have seven thousand people in our neck of the woods who don’t have a family doctor. If you move to the area, you will be number 7,001. Therefore, you will wind up going to our after hours clinic, or the hospital emergency department, which will increase the stress on those facilities.

This is, of course, not the fault of the individual physicians, nurses, allied health care workers. The blunt reality is the health care infrastructure is not there.

But I thought you guys were building a new hospital?

We are. BUT. We’ve known we’ve needed a new hospital since the early 2010’s, and despite many pleas, won’t start digging until 2029. We are hoping to complete in 2032. Various layers of inept government bureaucracy at the Ministry of Health have thrown many roadblocks in the construction process. As a result, our over burdened hospital puts patients in “unconventional places.“

You mean like hallway medicine?

Actually, I believe the term now is “chair care“because even the hallways are full.

Wonderful. Are the local townships not doing enough to recruit doctors?

It’s not really a township responsibility to look after the healthcare system. Now, there are some local efforts (with a bit of success) to get more family doctors in the area. However, that’s a slow process until the wider provincial problems are fixed.

You’re saying don’t come to the Georgian Triangle, but don’t these issues occur elsewhere?

Absolutely. I mentioned the Georgian Triangle just because it’s the area I know the best. Ontario has many beautiful areas for people to live in. Lots of different type of communities to suit all needs from small town, to large urban settings. But, if you currently live in an area where you already have a family doctor and you have a number of health issues, you really may want to reconsider moving until you can assure yourself of getting continuous, comprehensive, ongoing care in the community. Without a local family doctor, you will be getting itinerant care seeing different doctors at walk in clinics or Emergency departments, and that’s not good for your health.

So don’t move anywhere if you already have a family doctor?

Well look, people often have to move for many reasons. Work, family, retirement. I get it. BUT, I would encourage you, if at all possible, to scope out not just the amenities of the area you are thinking of, but also check the local health system out. That is something most people don’t do, they just expect health care to be there for them. That mentality needs to change.

And don’t move to the Georgian Triangle?

Yah, don’t move here. Our doctors (and hospital, and home care) are full.

FHO+: The Good, The Bad, and the Reality on the Ground

My thanks to Dr. Wael Guirguis, (pictured inset) who had a superb post on LinkedIN that he’s kindly allowed me to reproduce as a guest blog. Dr. Guirguis got his MD in Egypt in 2003 and has been practicing in Canada since 2011. He’s the lead physician for the Fairway FHO and provides comprehensive care for patients at the Danton Medical Centres. A thought provoking read which I hope you’ll enjoy.

Over the past couple of months, Family physicians across Ontario have started experiencing the reality of the new FHO+ model in day-to-day practice.The goals behind the reform are understandable.

Improve access. Support continuity of care. Encourage after-hours coverage. Create more accountability in primary care.

These are important goals, and family physicians should absolutely be part of improving the system. Some aspects of FHO+ deserve recognition. Organized after-hours coverage matters. Continuity of care matters. Accountability matters. But as implementation unfolds, many front-line physicians are beginning to identify operational consequences that may not have been fully appreciated during policy design.

The Efficiency Problem

One of the biggest concerns is the relationship between productivity and compensation efficiency. Under FHO+, physicians are now heavily constrained by hourly and monthly thresholds tied to direct patient care time. In practical terms, physicians can work harder, see more patients, and still experience a significant reduction in compensation efficiency. The unintended consequence is that the model may discourage efficiency during regular clinic hours.

A physician who develops efficient workflows, uses technology effectively, and safely improves patient throughput may actually feel penalized for doing so. That creates a concerning signal within primary care. Healthcare systems should reward:

  • safe patient access
  • continuity
  • quality
  • responsible innovation
  • sustainability
  • burnout prevention

Not unintentionally encourage physicians to slow down to remain within operational thresholds.

The Hidden Mental Burden

One of the least discussed consequences of FHO+ is the cognitive burden it creates for physicians throughout the day. Doctors are now not only thinking about patient care, they are also continuously tracking:

  • direct care hours
  • monthly hour accumulation
  • reimbursement thresholds
  • after-hours eligibility
  • continuity metrics
  • outside-use implications
  • whether additional work will still be compensated fairly

That constant background calculation creates mental fatigue. Family physicians already operate in an environment of nonstop decision-making: clinical care, inbox management, staffing issues, documentation, urgent requests, abnormal results, hospital follow-ups, and administrative work. Adding another layer of continuous operational tracking changes the psychology of practice itself. Instead of focusing entirely on patient care and clinic efficiency, physicians may begin constantly asking themselves:

“Am I crossing another threshold?” That is not a healthy foundation for sustainable primary care.

The Bigger Problem: Complexity Itself

This discussion is larger than FHO+ alone, It reflects a broader pattern in healthcare reform. With each reform cycle, the Schedule of Benefits seems to become increasingly complex rather than simpler.

New rules. New modifiers. New exceptions. New thresholds. New formulas. New tracking requirements. Yet very rarely do reforms focus on reducing front-line operational complexity for physicians. And complexity itself has consequences, It increases cognitive load, administrative dependency, billing anxiety, operational inefficiency, and eventually burnout. Complex healthcare systems may be unavoidable. But complex systems still require simple front-line workflows. That principle is often overlooked.

Continuity of Care Should Be Managed by the System, Not Punitive Billing Rules

Continuity of care matters. Family physicians understand that better continuity leads to better long-term outcomes, fewer fragmented records, reduced duplication, and safer patient care. But enforcing continuity through increasingly complicated physician payment penalties is not the right approach. A simpler and more effective solution already exists. If the Ministry of Health wants to strengthen continuity of care within capitation models, the responsibility should sit primarily with the system itself, not through constant billing complexity imposed on physicians.

For example: If a rostered patient repeatedly seeks care outside their enrolled medical home beyond a defined threshold, the Ministry could automatically review or remove the patient from the roster. The patient would be notified directly by the Ministry of Health not by the physician. This creates clear accountability while avoiding unnecessary tension between doctors and patients. Most importantly, it removes one of the major hidden burdens currently placed on family physicians: constantly monitoring continuity metrics, outside use calculations, and roster penalties while simultaneously trying to run busy clinics.

Continuity of care should be encouraged through smart system design and patient accountability  not by forcing physicians to navigate increasingly complicated billing formulas and penalties. Doctors should focus on delivering care. The healthcare system should focus on managing the system.

The Human Side Nobody Talks About

Most family physicians are not trying to maximize billing. They are trying to:

  • keep clinics financially sustainable
  • reduce patient wait times
  • manage inbox overload
  • supervise staff
  • complete documentation
  • respond to urgent patient needs
  • avoid burnout

When systems unintentionally penalize high-functioning clinics for being efficient, morale suffers quickly. And eventually, patients feel the impact.

A Better Path Forward

Primary care reform is necessary. But reforms work best when governments collaborate closely with front-line physicians who actually operate clinics every day. The goal should not simply be measuring physician hours. The goal should be:

  • maximizing safe patient access
  • improving continuity
  • reducing unnecessary administrative burden
  • supporting sustainable family medicine
  • encouraging innovation and operational efficiency
  • protecting physicians from burnout

Ontario has extraordinary family physicians who want the system to succeed. The question is whether the system is being designed in a way that allows them to succeed too.

Why You Should Attend the OMA’s (Continued) Annual General Meeting

Last week, the Ontario Medical Association announced that the continuation of the 2026 Annual General Meeting (AGM) will occur on Tuesday, June 23rd, at 6:30 PM. This meeting will be virtual only. Once again, proxies will not be allowed. I would suggest that it is essential for every member to make an effort to attend.

My three loyal readers will remember that there were six member proposals (4 by Dr. Conte seconded by myself). Only one got voted on at the May 7 meeting, and the remainder will be voted on, on June 23. Regardless of what you may think of the individual motions, I would suggest the fact that members take the time to make proposals, and attend to vote is a good thing. It is important, as I’ve learned over the years, to pay attention to what’s going on at the OMA because so much of our livelihood depends on them.

This year’s AGM is proof of what can happen when members show up and make their voices heard. Now, I was criticized for my blog on the last AGM for calling out the shenanigans that occurred at the meeting. This all surrounded what were in my opinion, the two most important motions.

Both motions pertained to removing non-physicians from having voting authority over physicians at the Board of the OMA. To be abundantly clear, neither of these motions would have prevented the organization from seeking external expert advice on an ongoing basis. Organizations, particularly advocacy organizations like the OMA, do that all the time, as they absolutely should. Physicians are not experts in everything, and seeking out the best possible advice in different areas from experts in their fields is always a good thing to do.

No. These motions would simply have said that after getting the advice, and carefully reviewing it, the voting authority for who makes decisions at the organization should fall only on physicians. Only physicians have innate knowledge and lived in experience of how the healthcare system affects them. Only physicians will inherently know when such advice, well intentioned though it may be, will actually help, or those times when it is unhelpful.

At the last meeting, for reasons that are unclear to me, as I’m not a lawyer, the first motion, which would have removed non-physicians from the Board immediately, required two thirds of a vote. This motion, after much debate, got fifty-three percent. Now, I fully expected some of our colleagues to throw up roadblocks to the first motion. That happened. I won’t do a line by line analysis of that as I don’t think it’s relevant, but if it had just stopped there, I probably wouldn’t have made any comments about “shenanigans” or “the usual suspects.”

What happened was that once it became apparent that the majority of physicians at the meeting did want not want non-physicians voting at the Board level, it became crystal clear that the second motion, which only required fifty percent plus one, would likely pass. A friend of mine, who also attended virtually, commented to me, “I wasn’t in the room, but I swear I could hear the jaws drop and the shock from many of the people in the room.”

Rather than accept that the debate had already been had, that all of the points had already been made, and accept the will of the membership, some of our colleagues continued to try and delay the process and play games. Eventually they succeeded. The meeting was paused and now we have to do it all again. And those are the shenanigans that had me, quite frankly, extremely annoyed.

At any rate, the membership has another chance. If we all show up, we can vote on the second motion and determine if we do, in fact, want a large part of our futures decided by non-physicians. (Non-physicians have just over twenty-five percent of the vote at the board currently).

Other motions that are important for us to decide upon include the director election ballots process. This year marked, as far as I’m concerned, a new low in how the board director elections were run. The OMA screened candidates for board director and limited who could run based on their own criteria, that was fed to a third party firm to try to avoid blame. In essence, the OMA chose who we physicians could vote for. Furthermore, they impugned the reputation of one of the president elect candidates by printing subjective opinions about his social media posts.

The second motion would stop the OMA screening candidates and allow the members to pick who they want leading them.

Other motions include eligibility for board if you had previously held the role of president in the association. Once again, it is really the decision of the members, not the OMA, to rule out who can and can’t run (and yes, there’s a conflict of interest in there for me). There’s also a motion recommending the OMA not access personal tax information. The OMA has never actually accessed personal tax information despite significant misinformation about this. However, I personally see no harm in restating that again. And finally, there’s actually a really good idea asking the OMA to support their districts by sharing email lists in compliance with privacy legislation. Our districts do need strengthening, and this would help with that.

None of these changes, however, can occur without physicians showing up. It will take time. It will take effort. It is a couple of hours out our very busy days. I feel bad asking for members to sacrifice this amount of time, but at the end of the day, if we don’t pay attention to what’s going at the OMA, we will not get the results we deserve.

I encourage all Ontario physicians to register early for the AGM by clicking the link below:

Register for June 23, AGM

The Shrinkflation of Family Medicine

Dr. Julie Wilson (pictured inset) had a superb post on LinkedIN that she has kindly allowed me to reproduce here as a guest blog. A much smarter person than I, she is a family doctor,has been named one of Canada’s 100 Most Powerful Women, Top 40 under 40, 3 x Business award winner and much much more. I encourage you to follow her for more of her excellent insights.

There is a word for when the packaging stays the same but there is less inside. In groceries, we call it shrinkflation. In family medicine, the same process has been underway for years and we still do not have a proper name for it. The phenomenon is real, the consequences are significant, and the cause is structural rather than professional.

It deserves to be examined plainly.

What Family Medicine Was Designed to Do

When I completed my family medicine residency, the expectations were unambiguous. A graduating family physician needed to be able to deliver their own patients’ babies, follow them in hospital, suture lacerations in the office, perform biopsies and joint injections, insert IUDs, provide prenatal care, administer pediatric vaccines, conduct children’s wellness visits, and manage mental health from assessment through to ongoing treatment. You were trained to treat and manage every condition as though there were no specialists present, because in Canada, there often are not.

This was not an aspirational standard. It was the functional design of the role. Family medicine in Canada was conceived as the foundation of a system in which primary care would carry the load that specialist infrastructure could not be expected to cover across a country of this geographic scale and population distribution. Broad scope was not a luxury. It was a requirement.

What Has Changed Since the Pandemic

The erosion of that scope has been incremental and largely unremarked upon in public discourse. Since the pandemic, a substantial number of family physicians, including those whose practice is confined entirely to clinic-based work, have stopped performing procedures and providing services that were previously considered core to the role. Biopsies, suturing, contraceptive management, prenatal care, pediatric immunisation, children’s wellness visits, mental health assessments, and ongoing counselling have migrated out of the family practice setting into referral queues, specialist offices, and in many cases, emergency departments.

It would be tempting to attribute this to shifting training norms or changing physician preferences, and those factors are not entirely irrelevant. But they are not the primary explanation. Family physicians did not collectively decide to de-skill because they lost interest in comprehensive practice. The more accurate explanation is that the financial and structural conditions required to sustain comprehensive practice have deteriorated to the point where, for many clinics, broad scope is no longer economically viable.

The Economics of Comprehensive Care

Comprehensive care costs more to deliver than narrow care. It requires longer appointment slots, better equipment, more qualified support staff, more expansive insurance coverage, and considerably more time spent on coordination and documentation that does not generate a separate billing code. These are real costs that the clinic model must absorb, and for a significant proportion of BC primary care clinics, the current overhead structure cannot absorb them.

The 2025 Financial Review of Primary Care Clinics in Vancouver, produced by the Vancouver Division of Family Practice, provides useful context. Average operating expenses per physician run approximately $110,000 per year. A clinic operating at 25% overhead on a physician billing $450,000 generates $112,500 in revenue, leaving almost nothing above the average expense threshold and no margin whatsoever for the additional infrastructure that comprehensive practice requires. At overhead rates of 20% or below, which are increasingly common in recruitment conversations driven by alternative-revenue clinic models, the arithmetic becomes impossible well before extended scope enters the picture.

The result is a rational economic response to an irrational structural situation. Clinics on constrained margins contract their service offering to the minimum sustainable model. Services that require additional time, equipment, or staff are referred out. The physician’s role narrows not because of a change in values or training, but because the financial model of the clinic cannot support anything broader.

The Systemic Consequences

The consequences of this contraction do not remain contained within the family practice setting. They redistribute across the health system in ways that are cumulative, expensive, and in many cases preventable.

Canada operates on the stated premise of a primary care-based health system. The logic of that model is that a robust and comprehensive primary care foundation reduces the demand on specialist services, emergency departments, and acute care capacity. When the foundation contracts, the load it was carrying does not disappear. It transfers.

Every laceration that is no longer sutured in a family physician’s office becomes an emergency department visit. Every mental health presentation that no longer has a landing place in primary care adds to the demand on crisis services and inpatient psychiatric capacity that is already stretched beyond its design parameters. Every biopsy that moves from a family physician’s office into a specialist referral queue adds weeks or months to the interval between a patient’s first concern and a clinical diagnosis. Every prenatal patient who cannot access continuity of care through their family physician adds complexity to obstetric and hospital-based maternity services.

Specialty wait times lengthen not only because of specialist supply constraints but because specialists are now managing presentations that a well-resourced primary care system would have handled earlier and closer to home. Emergency departments are not simply overwhelmed by volume. They are absorbing a category of care that primary care has progressively stopped providing, without any corresponding expansion of emergency capacity to meet that transferred demand.

The diagnostic lag that results from this redistribution carries its own clinical cost. The interval between a patient identifying a concern and receiving a diagnosis has extended from days to months for an increasing range of conditions. In oncology, in cardiology, in neurology, earlier diagnosis consistently correlates with better outcomes. The compression of primary care scope is not a neutral administrative adjustment. It has clinical consequences that are difficult to measure at the individual encounter level but become visible at the population level in outcomes data.

Patients who have only ever experienced the contracted version of family medicine do not recognise what is absent, because they have no baseline for comparison. They do not know that the referral they received could have been managed in the same appointment by a physician who is fully trained and willing to do the work. The shrinkflation is invisible to those who have never seen the full product.

The Path Back

Restoring comprehensive family medicine will not happen through exhortation. Physicians who have adapted their practice to the structural constraints of their clinic model will not re-expand their scope because the profession asks them to. The conditions that made contraction rational need to change before expansion becomes possible.

Several directions are worth pursuing seriously. Funding models need to reflect the genuine cost of delivering comprehensive primary care, including the additional infrastructure, time, and staff that broad scope requires. The LFP billing model in BC represents progress in recognising longitudinal value, but it does not yet fully account for the procedural and extended scope work that a comprehensive practice involves.

Training culture matters as well. If residents observe that the physicians they are learning from no longer perform the procedures they are being taught, the implicit message is that those skills are aspirational rather than practical. Preserving broad scope in residency training requires that the training environment model it, which requires that the clinics where training occurs are financially equipped to sustain it.

Record transfer and cross-clinic infrastructure also warrant attention. A physician who might otherwise take on complex procedural or prenatal care is significantly less likely to do so if the clinical history required to do it safely is inaccessible because of the fragmented and non-interoperable state of EMR systems across BC. The administrative friction of comprehensive practice needs to be reduced, not compounded.

Finally, the conversation about what is being lost needs to happen at a scale and with a directness that it has not yet achieved. Policymakers, health system planners, and the public are not well positioned to advocate for the restoration of something whose disappearance they have not been clearly shown. Making the shrinkflation visible, naming it, costing it, and tracing its consequences through the system is a necessary precondition for addressing it.

The physicians are still trained. The capability is present. What is required now is a serious, sustained effort to rebuild the structural conditions that make comprehensive family medicine not only possible, but financially sustainable for the clinics and physicians who want to practice it properly.

Dr. Julie Wilson, MD, CCFP, FCFP