What Exactly is the CFPC Leadership Thinking?!?

My few loyal readers will know by now that I am one of three physicians (along with Drs. Dubord and Conte) who are sponsoring six motions at the College of Family Physicians of Canada (CFPC) annual general meeting (AGM). I genuinely feel that these motions will push the CFPC into a better direction, and will help make it a more accountable organization for frontline members like myself.

I have no illusions, and neither should you, that simply passing these motions will “fix” the CFPC. I’ve come to realize that there is, in fact, no “fixing” of any physicians’ organizations, for a myriad of reasons. But what there can and must be, is ongoing, consistent vigilance and pressure applied by frontline members. These organizations must constantly be pushed to go in the right direction. I believe that passing these six motions will do that.

Having said that, I confess to being completely befuddled by the approach that the current leadership of the CFPC is taking towards these motions. Make no mistake, I fully expected the CFPC leadership to oppose the motions as written. That’s fair. Healthy disagreement and tension are vital for the success of any membership organization. But the strategy they are using honestly suggests that they hope member indifference will stop the motions. (NB – I do recognize there is a large degree of apathy towards the CFPC – but that doesn’t mean that it a GOOD thing).

For example, in the initial emails to the membership announcing that these six motions would be presented at the AGM, the CFPC specifically pointed out that the doctors supporting these motions did not respond to attempts to reach out and work cooperatively on them. Did they not think we would keep receipts? Dr. Dubord clearly reached back and asked for clarifications on what parts of the amendments were felt to be in contravention of Canada’s Not for Profit Corporation Act (NFPCA). We still don’t have a clear answer to that question.

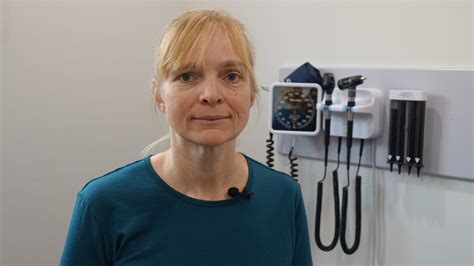
As recently as last week, CFPC president Dr. Sarah Cook (who I will say has done a good job promoting the importance of family physicians in public) stated that our motions “sit uneasily with the law,” and that “court direction may be needed.” But which parts of the motion sit “uneasily”? Which part of the NFPCA will necessitate “court direction”? The specifics have not been provided to the members at large.

Dr. Sarah Cook, President, CFPC

Additionally, while the CFPC has developed five alternate proposals that they state could be implemented much more quickly, a review of these alternate proposals suggests that there’s enough leeway for the board to NOT implement them. Remember, this is the same organization that treated a 95 percent vote in favour of access to Board Minutes and a 91 percent vote in favour of an independent review of the PGY-3 mess as suggestions, and declined to implement either. Did the CFPC leadership think we would have all forgotten that? And that we wouldn’t want something with more “teeth” the next time round?

Our six motions are by-law changes that the CFPC would be forced to abide by. Given the unfortunate lack of trust that appears to be there between the membership as a whole and the CFPC leadership, I really don’t understand how the CFPC thought alternate proposals without “teeth” would be acceptable.

Additionally, it would seem that members are expected to forget that last year, the CFPC wanted to institute perpetual annual fee hikes for members (up to the rate of inflation). The argument was basically “we’ve trimmed all the fat we can.” (In fairness they did trim their budget a lot). But suddenly, this year, they don’t need a hike anymore (there is a motion at this year’s AGM presented by the CFPC to keep the fees the same). You mean, membership pressure works? Golly.

All of which is my way of saying that I have the strong sense that members need to continuously push the CFPC to do the right thing. We CAN have a better organization, we just have to put a little bit of effort into it.

It should surprise no one that I’m going to encourage all of you to support the six motions and reject the alternates. As a reminder, members can vote by proxy but MUST register by Sunday October 25 at 11:59 pm.

The directions, once again, for voting by proxy:

First search your email inbox with the phrase “CFPC”. This should identify all the emails from the CFPC you have. Go to the email dated on October 7, 2026. That one will have a link to register, personal information and your control number. Then do the following:

1. Log in at: election-client.ca.electa.lumiconnect.com/cfpc/proxycard/ with their email and the control number from the College’s Oct. 7 email. NEVER send your control number to anyone else.

2. Item 1: Appointing a proxy. The default options are Board officers. Pick the middle option and type: Paul Conte. He has graciously agreed to hold proxy votes. He has set up an email just for proxies: paul.cfpcproxy@gmail.com

3. Items 2 to 9: This is all CFPC business. Vote as you see fit. As an FYI Item 5 approves keeping the fees where they are.

4. Item 10: This is the CFPCs own package of needed bylaw fix, and I support these and encourage you to support them too.

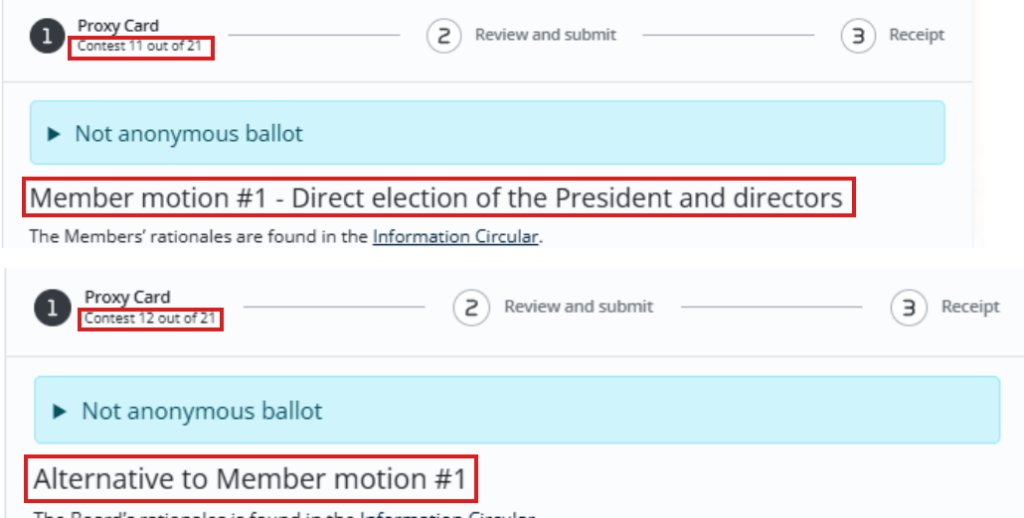
5. Items 11 to 21: I ask that you approve every Member Motion (Items 11, 13, 15, 17, 18 and 20). It is ESSENTIAL to REJECT EVERY Alternative Motion (Items 12, 14, 16, 19, 21). NB. The Proxy Card refers to these as CONTESTS, NOT ITEMS. See image below (modified from an original made by Dr. Kamphuis):

With any luck, we can have a better CFPC on October 29, but only if we are willing to make our voices heard by voting.

How To Vote By Proxy at the CFPC Annual General Meeting

On Wednesday, October 28 2026, the College of Family Physicians of Canada (CFPC) will hold its annual general meeting (AGM). There will be a number of important motions for discussion. I will say, however, that the CFPC, like a lot of representative medical organizations, often suffers from a lack of engagement from the broader membership. It seems that engagement only goes up when organizations do something to upset members, like trying to implement a third year of the residency program without a member vote.

This is unfortunate. Physician members’ organizations would benefit greatly if only it was easier for physicians, given their overwhelmingly busy lives, to get engaged in a meaningful way with those organizations. Emphasis on easier.

Hoping to make the CFPC stronger , Drs. Conte, Dubord and I have proposed six bylaw changes. We genuinely feel this will make the CFPC more democratic, transparent, and accountable. It would be foolish to suggest that simply passing these motions will fix the CFPC. There is no fixing of membership-driven medical organizations, there is only ongoing supervision and treatment. But passing these six will allow members to keep an eye on the CFPC.

The response from the current leadership of the CFPC seems well intentioned. However, a deep dive into the minute package shows a fair bit of institutional groupthink.

For example, according to their AGM Meeting Materials:

“Upon receiving the proposals, management invited the members to work collaboratively to address certain noted concerns with the proposals. The members declined, opting for the proposals to be presented to the membership as originally submitted.”

We suspect what the leadership meant was that we chose not to co-operate in the way that the leadership wanted us to. Dr. Dubord had clearly sent a response back asking for specifics about the legal concerns. The CFPC replied on Aug 12 it would not lay out legal concerns and hasn’t specified these concerns in the meeting package. Not sure how to co-operate given this.

The leadership of the CFPC says that our six motions are based on good ideas and a positive desire to transform and improve the CFPC. I thank them for recognizing that. They state they want something similar, and have proposed alternative motions, which they feel are better. I thank them for putting the time and effort into developing alternative suggestions.

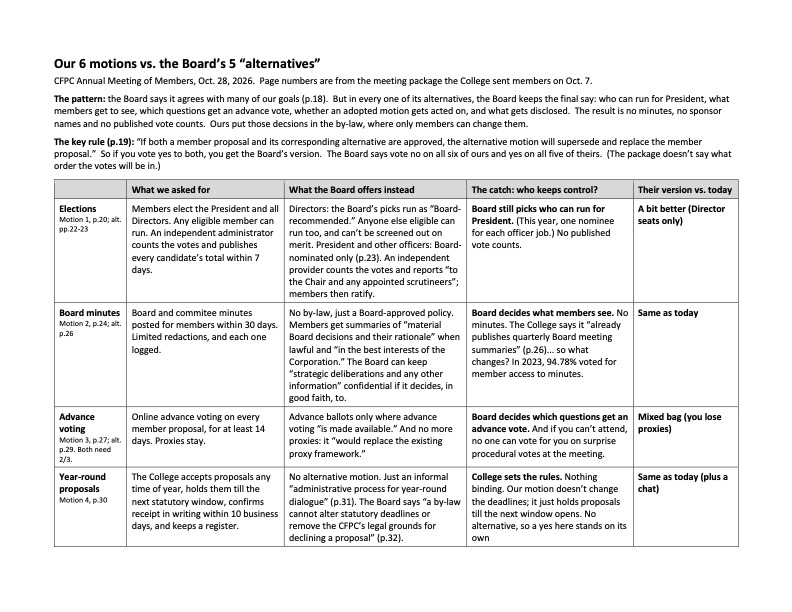
Unfortunately, when unpacking their proposals with a moderate degree of scrutiny, many loop holes become apparent. The potential for none of the changes we want to be implemented in a meaningful way exists. The CFPC leadership has made it clear if both our motions and their 5 alternatives pass, then their alternatives will take precedence. In our view, their alternatives lack the bite of our six motions.

For example, the first motion is for the membership as a whole to elect their president. The board instead is offering board-recommended picks. This essentially means that the board can still choose who runs for president. My guess is that the CFPC is scared that someone ill suited for the role will be chosen.

But if we look at the Ontario Medical Association (OMA) – as part of their governance transformation, they realized that members had to decide who the most visible person on their Board was. The OMA has been holding member wide elections for president since 2018 (initially non-binding) and it was really only in 2018 that some uncouth, obnoxious, ill mannered lout was chosen to be President-Elect. The rest have all been pretty reasonable people.

Similarly, our second motion called for board and committee minutes to be posted, but instead the board is just offering summaries (no change). Our third motion codifies online voting (which will increase engagement!) whereas the Board wants to pick and chose. Our fifth motion demands a 90 day response, time while the Board’s doesn’t have the same teeth to enforce. And the motion on financial disclosure we propose is much stronger than the Boards alternative.

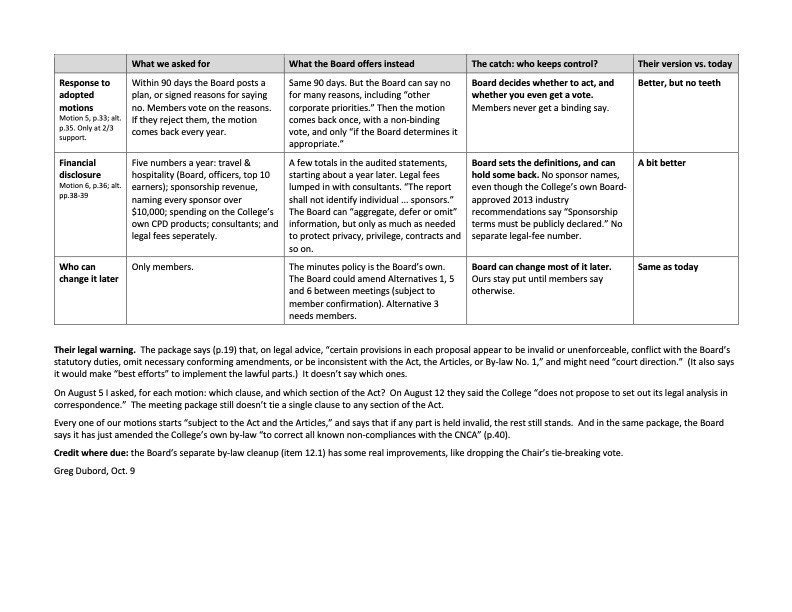
Here’s a chart with a nice summary of the differences in our motions and the Boards alternatives (a larger version can be downloaded here):

Here are the steps you need to follow if you support our motions:

First search your email inbox with the phrase “CFPC”. This should identify all the emails from the CFPC you have. Go to the email dated on October 7, 2026. That one will have a link to register, personal information and your control number. Then do the following:

1. Log in at: election-client.ca.electa.lumiconnect.com/cfpc/proxycard/ with their email and the control number from the College’s Oct. 7 email. NEVER send your control number to anyone else.

2. Item 1: Appointing a proxy. The default options are Board officers. Pick the middle option and type: Paul Conte. He has graciously agreed to hold proxy votes. He has set up an email just for proxies: paul.cfpcproxy@gmail.com

3. Items 2 to 9: This is all CFPC business. Vote as you see fit. As an FYI Item 5 approves keeping the fees where they are.

4. Item 10: This is the CFPCs own package of needed bylaw fix, and I support these and encourage you to support them too.

5. Items 11 to 21: I ask that you approve every Member Motion (Items 11, 13, 15, 17, 18 and 20). It is ESSENTIAL to REJECT EVERY Alternative Motion (Items 12, 14, 16, 19, 21). NB. The Proxy Card refers to these as CONTESTS, NOT ITEMS. However, the numbering system still stands. Vote YES on 11, 13, 15, 17, 18 and 20. Vote NO to 12, 14, 16, 19 ,21. Remember, if the alternate motion gets accepted, it will supersede the six member motions, and no meaningful change will occur. You should see something like this:

5. Submit by Oct. 25 at 11:59 p.m. ET. Before you do, turn on vote verification on the review page.

Some of you may disagree with the six motions we propose and support the CFPC Board. That’s fine. Healthy tension and disagreement is vital for any organization. But what’s not fine is for members to ignore this issue and NOT vote, particularly since you can appoint a proxy. (A proxy HAS to submit your votes the way you want, even if the proxy disagrees with you).

I truly hope that first and foremost, every member of the CFPC takes the time to vote. A healthy vote count means members want the CFPC to be better and sends a strong message as to steps that can be taken to achieve that goal.

GRAND ROUNDS: A 72-YEAR-OLD NATIONAL COLLEGE PRESENTING WITH CHRONIC MEMBER DISCONNECTION

N.B. Once again, my thanks to Drs Greg Dubord (mostly!) and Paul Conte for co-authoring this blog.

CHIEF COMPLAINT

Chronic member disconnection. By the patient’s own account, “some” physicians have felt disconnected, but investigation reveals this is very widespread. Self-Management (a column, a newsletter, a podcast and poorly attended town halls) failed.

HISTORY OF PRESENT ILLNESS

In January 2022 the CFPC (“the patient”) surveyed its members and found that only 39% felt the College listened to them, and only 25% considered their fees worth the money. No full satisfaction survey published since. That same month it proposed a mandatory third year of residency, PGY3, without a member vote.

At the November 2023 AGM, members voted 91% to stop PGY3 and review how it came about. 95% asked for access to Board minutes. The patient withdrew the proposal and promised “a comprehensive, independent review process.” In July 2024 the patient declined to release minutes and recorded “no further need for an analysis of this direction.” Asked about PGY3 this year, the President said: “We learned a lot from that… But we have moved past that.”

PAST MEDICAL HISTORY

  • 2013 to 2016: Merged its certification exam with the Medical Council of Canada’s, then unmerged it.
  • 2019 The Board decides each year which “skills, experience and perspectives” it wants, its committee screens applicants for them, and the Board sets the final list of nominees “in its sole discretion.” Members then vote, but only among the names the Board has already chosen, and for the officer positions there is exactly one name each.
  • October 2023: Data breach, with members not told the details until more than five months later.
  • November 2023: Proposed a 7% fee increase. 83.86% of members rejected it.
  • 2024 to 2025: Went to court to validate its own by-laws retroactively after, by its own affidavit, more than a decade of non-compliance with the federal Act. (Ontario Superior Court of Justice, court file CV-24-00096601)
  • March 2025-February 2026: Adopted a Member Code of Conduct binding on all 46,000 members, then added suspension or revocation of membership as penalties, with appeals decided by a panel the Board Chair designates and declared “final.” Never put to the members.
  • November 2025: Proposed a by-law allowing automatic annual fee increases tied to inflation, citing financial strain. Members defeated it. Surplus that fiscal year: $7.5 million.
  • March 2026: Fifteen member proposals for governance reform disqualified for arriving outside the 60-day window.

EXAMINATION

Vital signs.

Pulse: Only a few hundred (at most) out of 35,000+ members attend AGMs.

Approval: 37% of Members feel CFPC plays important role.

Intake: Member proposals accepted on only 60 days of the year.

Mental status: Pleasant and well groomed. Defensive thought processes noted:

  • Minimization (“some physicians have felt disconnected”)
  • Rationalization (minutes withheld on legal advice)
  • Displacement (a 37% approval rating is a problem of “how we’re portraying that information”)
  • Reaction formation (“We really welcome divergent perspectives and voices”)
  • Compartmentalization (accreditor and vendor of CPD described as two different departments behind a “firewall”)
  • Cognitive distortions: Catastrophizing (a projected $5.4 million deficit, “not sustainable to continue long term”; the year closed with a $5.1 million surplus
  • All-or-nothing thinking (either full minutes with “sensitive material” or two-page summaries; redaction, which is how every other body that publishes minutes handles sensitive material, does not occur to the patient)
  • Labeling (a 95% member vote becomes “advisory”; an unseen by-law package becomes “corrective”)
  • Risk to self: low. Risk to members: ongoing.

INVESTIGATIONS

Bloodwork (audited statements, year ended February 28, 2026): Revenue $59.5 million; dues $30.0 million (compulsory for anyone keeping the CCFP); surplus $7.5 million, after $5.1 million the year before; reserve fund $40.0 million; cash $11.6 million, up from $4.2 million; the Office of the CEO’s budget line (shared only with non-FMF meetings) up 41%, from $2.8 million to $3.9 million. Sponsors named: none. Legal fees: no subtotal, not itemized, somewhere inside $7.0 million of “corporate services.”

Imaging (the College’s governing by-law, read in full): Section 5.2: The Board sets the list of nominees “in its sole discretion.” Section 5.3: The President “will be acclaimed.”

Records review: Board minutes not available to members. A 95% vote in 2023 asked for them; the Board declined in July 2024 and offers two-page summaries instead.

ASSESSMENT AND PLAN

Primary diagnosis: Oligarchy (a form of government in which all power is vested in a few persons or in a dominant class or clique; government by the few.). Robert Michel’s Iron Law of Oligarchy suggests that all complex organizations develop into oligarchies. Hence no cure for the illness itself. But symptomatic treatment is warranted.

Picture of German Born sociologist Robert Michels who moved to fascist Italy in the early 1900s and contributed to the elite theory of political dynamics
Sociologist Robert Michels, authour of the Iron Law of Oligarchy

Treatment Plan: Support of six motions at the AGM by members essential to treat the most significant symptoms of this patient.

Problem 1. Electile dysfunction. Treatment: Members elect the President and Board directly; any member may run; no committee screens the ballot.

Problem 2. Transparency deficiency disorder. Treatment: Board and committee minutes posted within 30 days.

Problem 3. Restrictive Voting Syndrome, aka Evening-meeting exclusion syndrome with proxy-dependent syndrome. Treatment: Electronic advance voting on member proposals, on the system the College already runs.

Problem 4. Seasonal access disorder (member proposals accepted only during a 60-day window, in summer) Treatment: Member proposals accepted year-round.

Problem 5. Mandate amnesia. Treatment: A formal Board response within 90 days to any proposal that passes: An implementation plan, or written reasons that members then vote on.

Problem 6. Financial reserve hypertrophy disorder. Treatment: Five figures published every year: Travel and hospitality; sponsors over $10,000, by name; spending on the College’s own CPD products; consultant fees; legal fees.

PROGNOSIS

Prognosis with treatment: Good. The patient is solvent, well resourced and, on the President’s own account, wants to reconnect. Without treatment: Highly probable progressive deterioration. Adherence to treatment suggestions have historically been poor. Two unambiguous member orders above 90% went unfilled. That is why each treatment is written as a by-law the Board cannot repeal on its own.

FOLLOW UP

October 28, 7 PM Eastern, Virtual. There will be a notice of meeting arriving by October 7 (check your email). Directions for voting on treatment protocol by proxy will be reviewed in a follow up blog shortly after notice of meeting.

CODE STATUS:

Full code. The members want this patient to live. We just want it healthier.

How to Make the CFPC More Accountable to Members

NB: My thanks to Dr. Greg Dubord and Dr. Paul Conte for co-authouring this blog.

Last June, Ontario physicians changed how the Ontario Medical Association (OMA) is governed. It wasn’t by writing angry letters. It was by registering for a virtual meeting, giving up some of their valuable time by showing up, and voting. The lesson was simple: members CAN change an organization that is supposed to advocate for and defend them, IF they are willing to get just a little bit involved.

The same opportunity is now in front of every practising member of the College of Family Physicians of Canada (CFPC), but the window is short.

WHAT’S ON THE BALLOT

In July, Dr. Greg Dubord, Dr. Paul Conte and I, each filed the same six proposals with the CFPC in accordance with the Canada Not-for-profit Corporations Act. On August 12 the College confirmed in writing that all six will go into the notice of meeting for the October 28 Annual Meeting of Members, exactly as we filed them.

Our motions are bylaw amendments, rather than ordinary resolutions. In 2023, members voted 95 per cent for access to Board minutes and 91 per cent for an independent review of the PGY3 process. Because they were not bylaw changes, the Board treated them as suggestions and declined to implement either. A by-law change means it is mandatory for the Board to follow it.

The full text of the motions (warning – there is a lot of legal jargon), can be found here. In plain English however, the six motions would:

1. Let members elect the President and the Board directly, with any member free to run and no committee screening the candidates.
2. Post Board and committee minutes to the member portal within 30 days.
3. Let members vote electronically in advance on member proposals, using the electronic voting system the College already runs.
4. Accept member proposals year-round instead of an easy-to-miss 60-day summer window.
5. Require the Board to respond formally, within 90 days, to any member proposal that passes: either an implementation plan or written reasons for declining, which members then vote on.
6. Publish five CFPC financial figures every year: travel and hospitality, sponsors over $10,000 by name, spending on the College’s own CPD products, consultant fees, and legal fees.

Number one is the big one. Right now the Board decides, in the by-law’s own words, “in its sole discretion,” who gets to be a candidate, and the President is acclaimed (i.e., installed without a vote) rather than elected. A small group choosing its own successors is the dictionary definition of an oligarchy. Motion 1 begins to democratize the CFPC.

WHAT ELSE IS COMING

The Board is bringing its own package of by-law amendments to the same meeting. At the September 9 member town hall (the recording is on YouTube) the President described it as corrective changes to bring the by-laws into line with federal law. She also said the Board will circulate its own commentary on our six motions alongside its package.

Fair enough. But not one clause of the Board’s package was shown at the town hall. Members will see the text for the first time when the notice of meeting arrives, which the College says will be by October 7. That leaves us just three weeks to read it before the vote.

We will be watching to see if the Board package touches the same sections our motions amend. We also want to see if the motion will be to approve the whole package in a single vote (i.e an omnibus vote) or each Board motion will require a separate vote. We prefer the latter.

One more thing to watch: the order of the votes. The Chair sets the agenda, and it would be natural for the Board’s package to come up before our motions. If their package rewrites the sections on elections, and then Motion 1 comes up, don’t be surprised to hear that the member motion “conflicts with the by-law as just amended.” It doesn’t. Our motions amend whatever by-law is in force at the moment they pass. But it’s the kind of thing that sounds convincing at 8:15 PM with a timer running, so it’s worth knowing before you log in.

HOW THE MEETING WORKS

The College has posted its meeting norms for October 28. If you read them you’ll see it allows only ninety seconds per speaker, with a visible timer. There’s no chat function, so you don’t have a clue what any of your colleagues are thinking. No amendments permitted from the floor.

In other words, nothing gets decided by debate on the night. Everything gets decided by who registers, and who shows up having already made up their mind. If physicians who simply favour the status quo, and the usual from the CFPC are the only ones that show up…….well…….

WHAT TO DO

The three of us recognize that family physicians are ridiculously busy. It has taken far too long for recognition of the unremitting nature of comprehensive family practice to be spoken about. Despite this, not nearly enough is being done to change things. This means that you all have precious little free time. However, the blunt reality is that we can’t change the CFPC for the better, unless members get involved.

We ask all CFPC members to do three things.

First, watch your inbox. The notice of meeting, with all six motions and the Board’s package, arrives by October 7. It will include registration and proxy instructions (yes, there does appear to be a proxy system for the CFPC, unlike for the OMA AGM).

Second, register the day it arrives. October 28, 7 PM Eastern, virtual. Put it in your calendar now.

Third, if you can’t attend, appoint a proxy. The notice will tell you how. A proxy vote counts exactly the same as one cast in the room.

And one question worth asking the College at amm@cfpc.ca: where on the agenda do the member motions sit, and will each be voted on separately? They’ve confirmed the motions are on the ballot. They haven’t said where, or how.

Regardless of what the leadership of member driven organizations may say, member engagement is always a good thing. The more members get involved and have their say, the stronger an organization will be. We encourage all family doctors to join us at the AGM.

We will post again with more information as the situation arises.

Innovation Winter

Recently, the Ontario Government announced plans for a province wide family practice record system. I was debating what to write about it when I came across this post from Dr. Shahin on LinkedIn. While I don’t agree with all of it, it’s an important point of view. He’s kindly agreed to allow me to post this as a guest blog, and I encourage you to give his LinkedIn page a read.

Dr. Ilan Shahin is a Family Medicine specialist who serves as the Primary Care Lead for Patient Attachment for the Central West Ontario Health Team (CW OHT). 

He’s also a Board Member and Secretary-Treasurer of the Ontario College of Family Physicians (OCFP), has an MD and Master of Business Administration (MBA) from McGill University and is a co-founder of ConsultLoop, a former e-referral platform.  Basically a whole lot smarter than I am.

Innovation Winter is a Canadian tradition of killing off product categories with the whisper of a large procurement.

Every so often in digital health, governments see small companies sprouting around a category, and decide to procure The Thing for the entire jurisdiction. This is ambitious, well-intended, and comes with its fair share of boosters. E-consults, e-referrals, and e-prescribing all had similar stories. However, these didn’t work out as intended.

E-consults remains a clunky product with uptake well below its potential, when once there was a physician-led startup that offered a nice mobile experience that was much easier to use and even log on to.

E-referrals is still maturing when it’s been 10 years since an original RFP was won via a single LHIN with the thought that it would be rolled out across the province. There too, there was a company (which I co-founded) that built the referral platform at less than 5% the cost of that initial RFP, produced unprecedented and yet unmatched wait time data, and had pilots shut down because of whispers that e-referrals would be deployed imminently across the province.

E-prescribing has the story of Infoway’s landmark project that was shut down after hundreds of millions in spending, with market penetration that was only a few percentage points of total prescriptions despite the virtualization pressure of a pandemic. Setting standards for companies serving the pharmacy market could have harnessed their competitive drives, rather than relying on one platform with its limited agility.

In each case, government comes with good intentions, and tries to build The Thing. In doing so, they create what is effectively a monopoly, which risks insulating the product from market forces that produce better value, and lower costs.

However we don’t need a large procurement to actually have happened, for the monopoly or oligopoly to be entrenched, in order to kill innovation. Just the mere whisper that something big is coming is enough to make rational actors across the system wait and see. This also includes small businesses, which is where the imperative to listen to customers, the urgency to improve, and the competition on price and quality actually lives. Ingenuity lives there too, in the companies facing short cash runways, the incumbent complex, and the need to prove themselves as trustworthy both clinically, operationally, and ethically.

Government has to be careful about what it does to the marketplace when it acts. Sometimes in raising its hand, it ushers in an innovation winter, which has the potential to block far more value in a robust, competitive market, than it uncovers in a RFP-led closed market approach.

Let government focus on building the strongest marketplace, driving to common standards to uplift the market’s value, while ensuring fair competition to harness the cost and quality pressures that come with it.

Market-making. That’s the game. Innovation winters are signs of failure.

FHO+: The Good, The Bad, and the Reality on the Ground

My thanks to Dr. Wael Guirguis, (pictured inset) who had a superb post on LinkedIN that he’s kindly allowed me to reproduce as a guest blog. Dr. Guirguis got his MD in Egypt in 2003 and has been practicing in Canada since 2011. He’s the lead physician for the Fairway FHO and provides comprehensive care for patients at the Danton Medical Centres. A thought provoking read which I hope you’ll enjoy.

Over the past couple of months, Family physicians across Ontario have started experiencing the reality of the new FHO+ model in day-to-day practice.The goals behind the reform are understandable.

Improve access. Support continuity of care. Encourage after-hours coverage. Create more accountability in primary care.

These are important goals, and family physicians should absolutely be part of improving the system. Some aspects of FHO+ deserve recognition. Organized after-hours coverage matters. Continuity of care matters. Accountability matters. But as implementation unfolds, many front-line physicians are beginning to identify operational consequences that may not have been fully appreciated during policy design.

The Efficiency Problem

One of the biggest concerns is the relationship between productivity and compensation efficiency. Under FHO+, physicians are now heavily constrained by hourly and monthly thresholds tied to direct patient care time. In practical terms, physicians can work harder, see more patients, and still experience a significant reduction in compensation efficiency. The unintended consequence is that the model may discourage efficiency during regular clinic hours.

A physician who develops efficient workflows, uses technology effectively, and safely improves patient throughput may actually feel penalized for doing so. That creates a concerning signal within primary care. Healthcare systems should reward:

  • safe patient access
  • continuity
  • quality
  • responsible innovation
  • sustainability
  • burnout prevention

Not unintentionally encourage physicians to slow down to remain within operational thresholds.

The Hidden Mental Burden

One of the least discussed consequences of FHO+ is the cognitive burden it creates for physicians throughout the day. Doctors are now not only thinking about patient care, they are also continuously tracking:

  • direct care hours
  • monthly hour accumulation
  • reimbursement thresholds
  • after-hours eligibility
  • continuity metrics
  • outside-use implications
  • whether additional work will still be compensated fairly

That constant background calculation creates mental fatigue. Family physicians already operate in an environment of nonstop decision-making: clinical care, inbox management, staffing issues, documentation, urgent requests, abnormal results, hospital follow-ups, and administrative work. Adding another layer of continuous operational tracking changes the psychology of practice itself. Instead of focusing entirely on patient care and clinic efficiency, physicians may begin constantly asking themselves:

“Am I crossing another threshold?” That is not a healthy foundation for sustainable primary care.

The Bigger Problem: Complexity Itself

This discussion is larger than FHO+ alone, It reflects a broader pattern in healthcare reform. With each reform cycle, the Schedule of Benefits seems to become increasingly complex rather than simpler.

New rules. New modifiers. New exceptions. New thresholds. New formulas. New tracking requirements. Yet very rarely do reforms focus on reducing front-line operational complexity for physicians. And complexity itself has consequences, It increases cognitive load, administrative dependency, billing anxiety, operational inefficiency, and eventually burnout. Complex healthcare systems may be unavoidable. But complex systems still require simple front-line workflows. That principle is often overlooked.

Continuity of Care Should Be Managed by the System, Not Punitive Billing Rules

Continuity of care matters. Family physicians understand that better continuity leads to better long-term outcomes, fewer fragmented records, reduced duplication, and safer patient care. But enforcing continuity through increasingly complicated physician payment penalties is not the right approach. A simpler and more effective solution already exists. If the Ministry of Health wants to strengthen continuity of care within capitation models, the responsibility should sit primarily with the system itself, not through constant billing complexity imposed on physicians.

For example: If a rostered patient repeatedly seeks care outside their enrolled medical home beyond a defined threshold, the Ministry could automatically review or remove the patient from the roster. The patient would be notified directly by the Ministry of Health not by the physician. This creates clear accountability while avoiding unnecessary tension between doctors and patients. Most importantly, it removes one of the major hidden burdens currently placed on family physicians: constantly monitoring continuity metrics, outside use calculations, and roster penalties while simultaneously trying to run busy clinics.

Continuity of care should be encouraged through smart system design and patient accountability  not by forcing physicians to navigate increasingly complicated billing formulas and penalties. Doctors should focus on delivering care. The healthcare system should focus on managing the system.

The Human Side Nobody Talks About

Most family physicians are not trying to maximize billing. They are trying to:

  • keep clinics financially sustainable
  • reduce patient wait times
  • manage inbox overload
  • supervise staff
  • complete documentation
  • respond to urgent patient needs
  • avoid burnout

When systems unintentionally penalize high-functioning clinics for being efficient, morale suffers quickly. And eventually, patients feel the impact.

A Better Path Forward

Primary care reform is necessary. But reforms work best when governments collaborate closely with front-line physicians who actually operate clinics every day. The goal should not simply be measuring physician hours. The goal should be:

  • maximizing safe patient access
  • improving continuity
  • reducing unnecessary administrative burden
  • supporting sustainable family medicine
  • encouraging innovation and operational efficiency
  • protecting physicians from burnout

Ontario has extraordinary family physicians who want the system to succeed. The question is whether the system is being designed in a way that allows them to succeed too.

The Shrinkflation of Family Medicine

Dr. Julie Wilson (pictured inset) had a superb post on LinkedIN that she has kindly allowed me to reproduce here as a guest blog. A much smarter person than I, she is a family doctor,has been named one of Canada’s 100 Most Powerful Women, Top 40 under 40, 3 x Business award winner and much much more. I encourage you to follow her for more of her excellent insights.

There is a word for when the packaging stays the same but there is less inside. In groceries, we call it shrinkflation. In family medicine, the same process has been underway for years and we still do not have a proper name for it. The phenomenon is real, the consequences are significant, and the cause is structural rather than professional.

It deserves to be examined plainly.

What Family Medicine Was Designed to Do

When I completed my family medicine residency, the expectations were unambiguous. A graduating family physician needed to be able to deliver their own patients’ babies, follow them in hospital, suture lacerations in the office, perform biopsies and joint injections, insert IUDs, provide prenatal care, administer pediatric vaccines, conduct children’s wellness visits, and manage mental health from assessment through to ongoing treatment. You were trained to treat and manage every condition as though there were no specialists present, because in Canada, there often are not.

This was not an aspirational standard. It was the functional design of the role. Family medicine in Canada was conceived as the foundation of a system in which primary care would carry the load that specialist infrastructure could not be expected to cover across a country of this geographic scale and population distribution. Broad scope was not a luxury. It was a requirement.

What Has Changed Since the Pandemic

The erosion of that scope has been incremental and largely unremarked upon in public discourse. Since the pandemic, a substantial number of family physicians, including those whose practice is confined entirely to clinic-based work, have stopped performing procedures and providing services that were previously considered core to the role. Biopsies, suturing, contraceptive management, prenatal care, pediatric immunisation, children’s wellness visits, mental health assessments, and ongoing counselling have migrated out of the family practice setting into referral queues, specialist offices, and in many cases, emergency departments.

It would be tempting to attribute this to shifting training norms or changing physician preferences, and those factors are not entirely irrelevant. But they are not the primary explanation. Family physicians did not collectively decide to de-skill because they lost interest in comprehensive practice. The more accurate explanation is that the financial and structural conditions required to sustain comprehensive practice have deteriorated to the point where, for many clinics, broad scope is no longer economically viable.

The Economics of Comprehensive Care

Comprehensive care costs more to deliver than narrow care. It requires longer appointment slots, better equipment, more qualified support staff, more expansive insurance coverage, and considerably more time spent on coordination and documentation that does not generate a separate billing code. These are real costs that the clinic model must absorb, and for a significant proportion of BC primary care clinics, the current overhead structure cannot absorb them.

The 2025 Financial Review of Primary Care Clinics in Vancouver, produced by the Vancouver Division of Family Practice, provides useful context. Average operating expenses per physician run approximately $110,000 per year. A clinic operating at 25% overhead on a physician billing $450,000 generates $112,500 in revenue, leaving almost nothing above the average expense threshold and no margin whatsoever for the additional infrastructure that comprehensive practice requires. At overhead rates of 20% or below, which are increasingly common in recruitment conversations driven by alternative-revenue clinic models, the arithmetic becomes impossible well before extended scope enters the picture.

The result is a rational economic response to an irrational structural situation. Clinics on constrained margins contract their service offering to the minimum sustainable model. Services that require additional time, equipment, or staff are referred out. The physician’s role narrows not because of a change in values or training, but because the financial model of the clinic cannot support anything broader.

The Systemic Consequences

The consequences of this contraction do not remain contained within the family practice setting. They redistribute across the health system in ways that are cumulative, expensive, and in many cases preventable.

Canada operates on the stated premise of a primary care-based health system. The logic of that model is that a robust and comprehensive primary care foundation reduces the demand on specialist services, emergency departments, and acute care capacity. When the foundation contracts, the load it was carrying does not disappear. It transfers.

Every laceration that is no longer sutured in a family physician’s office becomes an emergency department visit. Every mental health presentation that no longer has a landing place in primary care adds to the demand on crisis services and inpatient psychiatric capacity that is already stretched beyond its design parameters. Every biopsy that moves from a family physician’s office into a specialist referral queue adds weeks or months to the interval between a patient’s first concern and a clinical diagnosis. Every prenatal patient who cannot access continuity of care through their family physician adds complexity to obstetric and hospital-based maternity services.

Specialty wait times lengthen not only because of specialist supply constraints but because specialists are now managing presentations that a well-resourced primary care system would have handled earlier and closer to home. Emergency departments are not simply overwhelmed by volume. They are absorbing a category of care that primary care has progressively stopped providing, without any corresponding expansion of emergency capacity to meet that transferred demand.

The diagnostic lag that results from this redistribution carries its own clinical cost. The interval between a patient identifying a concern and receiving a diagnosis has extended from days to months for an increasing range of conditions. In oncology, in cardiology, in neurology, earlier diagnosis consistently correlates with better outcomes. The compression of primary care scope is not a neutral administrative adjustment. It has clinical consequences that are difficult to measure at the individual encounter level but become visible at the population level in outcomes data.

Patients who have only ever experienced the contracted version of family medicine do not recognise what is absent, because they have no baseline for comparison. They do not know that the referral they received could have been managed in the same appointment by a physician who is fully trained and willing to do the work. The shrinkflation is invisible to those who have never seen the full product.

The Path Back

Restoring comprehensive family medicine will not happen through exhortation. Physicians who have adapted their practice to the structural constraints of their clinic model will not re-expand their scope because the profession asks them to. The conditions that made contraction rational need to change before expansion becomes possible.

Several directions are worth pursuing seriously. Funding models need to reflect the genuine cost of delivering comprehensive primary care, including the additional infrastructure, time, and staff that broad scope requires. The LFP billing model in BC represents progress in recognising longitudinal value, but it does not yet fully account for the procedural and extended scope work that a comprehensive practice involves.

Training culture matters as well. If residents observe that the physicians they are learning from no longer perform the procedures they are being taught, the implicit message is that those skills are aspirational rather than practical. Preserving broad scope in residency training requires that the training environment model it, which requires that the clinics where training occurs are financially equipped to sustain it.

Record transfer and cross-clinic infrastructure also warrant attention. A physician who might otherwise take on complex procedural or prenatal care is significantly less likely to do so if the clinical history required to do it safely is inaccessible because of the fragmented and non-interoperable state of EMR systems across BC. The administrative friction of comprehensive practice needs to be reduced, not compounded.

Finally, the conversation about what is being lost needs to happen at a scale and with a directness that it has not yet achieved. Policymakers, health system planners, and the public are not well positioned to advocate for the restoration of something whose disappearance they have not been clearly shown. Making the shrinkflation visible, naming it, costing it, and tracing its consequences through the system is a necessary precondition for addressing it.

The physicians are still trained. The capability is present. What is required now is a serious, sustained effort to rebuild the structural conditions that make comprehensive family medicine not only possible, but financially sustainable for the clinics and physicians who want to practice it properly.

Dr. Julie Wilson, MD, CCFP, FCFP

Local Medical Schools Will Help Address Doctor Shortages

Old Country Doctors Note: I was a teacher with the Rural Ontario Medical Program for three decades. It was founded by Dr. Peter Wells, and based on the principle that putting trainee doctors in smaller communities will enhance the chance of them working there. It’s been wildly successful. On that same note, Dr. Butt feels that putting a Medical School in Barrie will help increase recruitment to smaller centres, and I think he’s right. His Letter to the Editor appeared in the local press, and he’s given me permission to reproduce as a guest blog here.

Dr. Atif Butt (pictured inset) guest blogs for me today. He’s one of these ultra smart characters who not only has and MBA (McMaster 2003) but also and MD (McMaster, 2011) and a CCFP (EM). He’s retired from the Military (Major) and works in ER in Alliston, and Urgent Care in Barrie and does sedations in an endoscopy clinic in Innisfil. Apparently he’s quite the dancer too.

Barrie has been home to my family and I since the fall of 2013. It is a wonderful area to raise a family and offers everything that a mid-size community requires but also the peace and quiet lacking in larger urban areas. It is also the gateway to cottage country.

I am surprised at how fast the city is expanding as demonstrated by the numerous condo buildings and townhouses being erected, especially on the Barrie/Innisfil border. A growing city will result in many consequences, some positive (e.g., more cultural diversity, more revenues for local businesses, etc.) but also some negatives (e.g., traffic headaches). It will also mean a growing population that will place greater demand on local health-care resources.

I have been practising medicine in several health-care organizations in the Barrie/Innisifil/Alliston area since 2013. I am impressed by how much demand is placed on local health-care organizations, yet they continue to persevere through. The success is fundamentally thanks to the heroic work of the health-care workers including physicians, nurses, and other allied health-care workers who band together to serve patients, often sacrificing their own nights and weekends. But we all have our limits and simply cannot do more.

Currently, almost six million Canadians (out of which over two million are in Ontario) do not have a family doctor. More specifically, it is estimated that over 55,000 people in the Simcoe County area do not have a family doctor. Almost every day, there are news reports of lengthy wait times in the ERs, which are frankly longer than plane flights from Canada to Pakistan. Attempts have been made to address such shortfalls by the use of nurse practitioners, physician assistants, and pharmacists and I am grateful for the work they provide. Nonetheless, physicians cannot simply be replaced by non-physicians and more are needed. That is why I am proposing that either a new medical school be created in the Barrie/Innisfil area or, preferably and more cost-effectively, seats from an existing Ontario medical school be expanded to our area.

I am encouraged to see that some efforts have already been made to expand medical school seats in Ontario. Examples include the 2025 opening of the Toronto Metropolitan University medical school and the upcoming opening of the York University medical school in 2028. I appreciate that such endeavours can be costly. For example, the federal government just announced almost $2 million to expand medical seats and services for the Northern Ontario School of Medicine. While this will greatly support the north, sadly, Barrie and the surrounding area seemed to be left out.

Despite investments in new medical schools, the demand far exceeds supply. For example, the newest medical school at TMU had 6,416 applications in 2025 but total projected class size in 2026 is 94. That means 1.5 per cent of applicants got accepted. Most medical schools in Ontario roughly seem to have on average about a three- to five-per-cent acceptance rate. While adding medical seats in Barrie/Innisfil maybe a drop in the bucket, it will hopefully lead to an ongoing pool of locally trained physicians that will want to practice in our area. Return of service contracts, where physicians have to practice locally for four to five years after training, can be a condition for acceptance into a medical school here.

Canada in general and Ontario in particular have a lot of talent, yet we are losing out. On a regular basis, I come across undergraduate students who have high GPAs/marks, extraordinary extra-curriculars and experiences, scored high on their MCATs, have applied multiple times to Canadian medical schools, yet are unable to even get an interview (let alone acceptance) into a Canadian medical school. Their families are often spending hundreds of thousands of dollars per year (in U.S. dollars) to send them abroad to the U.S./Caribbean/Europe so that they can pursue their dreams of becoming a physician. Even after they graduate from an international medical school, there is no guarantee that they will obtain a residency spot in Canada since preference is given to Canadian-trained grads. Hence, they may be forced to practise elsewhere like the U.S. Would it not be better if we could retain and train such talent who invested their tuition locally and then stayed to practise?

Intuitively, when medical trainees train in a particular geographical area, many will choose to stay and practise in that area. While in Barrie we have the Family Medicine Teaching Unit for training family medicine residents and the expansion of some ER residency spots at Royal Victoria Regional Health Centre, I believe that the next logical step is to have medical school seats in the Barrie/Innisifil area. This will allow us to recruit and retain future physicians in the local area.

I find that the simplest goals are often the most achievable and realistic. A brand-new expensive medical school with new infrastructure may be a costly pill for any government to swallow. Thus, simply expanding, say, a dozen seats, from an existing Ontario medical school to our area using existing hospitals or other health-care facilities may be much more palatable. Students will be able to virtually watch online any didactic lectures that are delivered at main campuses to obtain theoretical knowledge. Any practical knowledge and skills can be completed with assigned preceptors and through core rotations (e.g., ER, family medicine, obstetrics, general surgery) and elective (e.g., plastics, radiology, etc.) at several of the amazing and existing local hospitals and health-care facilities from Orillia to Barrie and Alliston to Newmarket. After doing three to four years of medical school and assuming they do a two-year family medicine residency in the Barrie/Innisfil area, I suspect many will choose to stay and practise in our wonderful area.

I have already reached out to several governing officials including the Office of the Premier of Ontario and the provincial minister of health to share my proposal. While their offices have provided some appreciative yet general responses of their broader investments, I truly believe that it is through greater and ongoing public support and engagement that expansion of a medical school in Barrie can be achieved. In other words, while I as a physician can write a prescription and explain the risks and benefits of the medicine, it is up to the patient to actually take the prescription. In this case, my prescription is the expansion of medical school seats to the Barrie/Innisfil area and I am asking you, the patient, to engage the government in filling this prescription.

About Dr. Elaine Ma: We’ve Been Here Before, and Didn’t Fix It…

My thanks to Dr. Mike Goodwin (pictured inset) for guest blogging for me today. Dr. Goodwin is a retired family physician who held numerous roles in medical politics including (but not limited to) being a member of the Coalition of Family Physicians, a member of the Section of General and Family Practice Executive and an OMA Board Director. He brings a historical perspective regarding medical audits to this blog, and I am grateful for his contribution.

I admire our courageous young colleague Dr. Elaine Ma, she of the seemingly never-ending OHIP billing/auditing dispute with a media savvy beyond her years. Dr. Ma’s impeccable sense of public health propriety during COVID has earned her a growing band of supporters. It has hopefully gained her financial support from both the Ontario Medical Association (OMA) and the Canadian Medical Protective Association.

But what Dr. Ma and younger colleagues may not appreciate is that OHIP’s abuse of doctors, utilizing its antiquated billing payment and auditing processes, has been ongoing for a long time. Between the years 2000 through 2005, a hundred odd doctors every year in Ontario were being subjected to the same sort of unfair retroactive audit, which Dr. Ma is currently experiencing.

Dr. Elaine Ma

Back then, just like now, we had a Schedule of Benefits (SOB) badly in need of an update, a pettifogging bureaucracy unwilling to interpret said schedule with any modicum of common sense… vague auditing rules which conferred the burden of proof upon the accused rather than the province, and the same one-sided authority to claw back payments or garnish future accounts receivable. OHIP even had computers back then, almost certainly the same ancient models they still use today (which they claim can’t possibly be configured to pay doctors in a timely manner after the award of binding arbitrated pay increases).

Administrative abuse of the profession in the very early aughts was rampant. OHIP had enlisted the help of the CPSO, because the College had administrative and regulatory authority, beyond criminal law, over all physicians pertaining to the practice of medicine. Actual auditing and enforcement of decisions was done by an entity of the College called the Medical Review Committee (MRC). It apparently escaped everyone’s notice at the time, and still today, that medical billing to OHIP was and is based upon definitions contained within an official MOH document called the OHIP SOB. The OHIP SOB is, at least in theory, derived from agreements negotiated between the province and the OMA, not the College! One might argue, logically, that any dispute concerning rules and definitions documented within the SOB should always be addressed in the first instance between the Ministry and the OMA.

At any rate, anger and despair over the medical billing and auditing system in that far away time came to a head when a gentle Welland paediatrician, Dr. Tony Hsu, committed suicide. I suspect that Tony felt he had lost face by going public with his own particular auditing horror story. The concept of “face” is important in the Chinese diaspora, and Tony, who worked a one in three (sometimes one in two) on call rota at the Welland County General Hospital (without any on-call stipends in those days), in addition to maintaining a community practice, was forced to repay $96,000. He had to take that out of his retirement savings.

Public and political outrage at Tony’s death, particularly in the Niagara region, was immediate and intense. Then Health Minister George Smitherman was pressed to call for a “public inquiry” into medical billing and auditing. By happy accident, retired Supreme Court Justice Peter Cory was available and appointed to the task. Those of us acquainted with Mr. Cory’s reputation silently cheered.

And when Cory’s very comprehensive report was published, nine months later in April 2005, the indecent OHIP billing auditing system finally came to an end.

Or so we thought!

In his report “Study, Conclusions, and Recommendations Into Medical Audit Practice in Ontario,” Mr. Cory did not mince words. “The medical audit system in Ontario has had a debilitating, and in some cases, devastating effect on physicians and their families,” he said. “It has had a negative effect on the delivery of services, and has undermined Ontario’s attractiveness as a place to practice.”

Also, and very pointedly, the honourable Cory recommended the appointment of a new independent audit board, while declining to take up an offer from the College to continue auditing medical billings as they had been doing prior to his inquiry. In all, Justice Cory made 118 separate recommendations, and I reproduce only the first four, below, since they were (possibly) the most important:

  1. Jurisdiction and structure: the responsibility for conducting the audits of physicians fee claims should be conferred on a new and independent board. See recommendations (1) to (4).
  2. Purpose of the audit process: The audit process must be employed only for the purpose of determining the appropriateness of physician fee claims. The audit system itself must be accountable. A biennial stakeholders forum should be established to receive reports on the operation of the new audit process and to receive and consider proposals for its improvement. See recommendations (5) to (7).
  3. A new emphasis on assisting physicians to comply with billing requirements: The primary goals of the new audit system should be (1) education to facilitate compliance with billing requirements, and (2) identification and elimination of false, fraudulent, and egregiously erroneous billing in a fair and effective manner. See recommendations (8) to (9).
  4. Schedule of benefits: The schedule of benefits must be revised and adapted. It must also be interpreted flexibly so that a physician is not deprived of payment for a service that is medically appropriate and that complies substantially with the requirements of the fee code. See recommendations (10) to (14).

(NB – as the report cannot be found online, Dr. Goodwin used his own personal copy of the report as a reference – Old Country Doctor)

In the wake of the Cory report, Minister Smitherman ceased audits immediately and promised changes. But no one at the MOH or College lost a job. And ministries or bureaucracies (like the CPSO) are resistant to any change from age-old ways of doing things. That’s particularly true when change might reduce influence, or even more important, authority and funding.

So when I joined the OMA board in 2005 as a newbie director, the ministry was already flooding the zone, as they did, with multiple new issues demanding our attention. Promises made didn’t materialize, and almost none of Mr. Cory’s recommendations, especially the most important, to “confer responsibility for conducting billing audits on a new and independent board,” were implemented. Months became years, and “the Cory report” gradually disappeared from sight, consigned to death by inattention. You can’t find it anywhere today, even with a Google search. Not even on the OMA website: for shame!

I’m convinced that if a significant part of Mr. Cory’s report had been adopted in 2005, much of the shoddy bureaucratic shenanigans from OHIP would have been fixed (including, maybe even their ancient computers). Dr. Elaine Ma would not be undergoing her current marathon persecution. Nor would we be seeing those cases where OHIP seems to let grifters get away with corrupt billing over multiple years before it (OHIP) picks up on the scam. How does that work, by the way?

It’s not every day you get support from a retired Supreme Court justice at your back… particularly such clear, sensible, workable recommendations from arguably the most influential liberal justice of the post-constitutional era in Canada. Peter Cory was famous for his kindness, and for his defence of human dignity at every opportunity…though he definitely had an iron fist in a velvet glove when the need arose. For anyone (like me) who ever had the good fortune to meet him, he was just an unforgettably decent man.

Memo to the OMA:

If you really want to fix this auditing problem, something which I and my colleagues failed to do, Peter Cory’s report from 2005 would still be a great place to start. Dr. Elaine Ma has provided you a good crisis: let’s not waste it.

The Appalling Treatment of Dr. Elaine Ma Is Hurting Health Care in Ontario

I’ve written about the horrific treatment that Dr. Elaine Ma has been subjected to by the bureaucrats at Ontario Health before. The situation is so ridiculous that it could be a story presented at the Theatre of the Absurd.

What happened?

Dr. Ma is a family physician from the Kingston area. During the Covid pandemic she realizes the need to immunize as many people as possible to protect the community. She organizes a number of outdoor mass vaccination clinics, which resulted in Kingston being one of the most heavily vaccinated areas of the province. For her efforts, she wins the very well deserved the praise of many, and an award from the Ontario College of Family Physicians.

There are two billing codes for providing Covid vaccinations. One for physicians who work in a vaccination clinic that someone else set up (e.g. public health). Another for those who set up the clinics themselves, and paid for staff/heating for outdoors/tents/internet etc. Since she paid for all of that, Dr. Ma bills the second code.

Dr. Elaine Ma

Fast forward a couple of years and the callous and unthinking bureaucrats at OHIP decide that she has billed the wrong code and demand she pay back $600,000. I won’t restate all the steps she went through to fight this. I will state that the reasons for them wanting the money paid back varied between the clinic being outdoors instead of indoors, medical students being involved and so on. But eventually the case winds up at Divisional Court.

On Dec 16, the court handed down a ruling supporting Dr. Ma. What I had failed to realize before is that the Ontario Health bureaucrats main argument appears to be that there were no extenuating circumstances during the time of the Vaccine Clinics that Dr. Ma set up. Yes, you read that correctly. The whole country was in the midst of a (hopefully) once in a lifetime pandemic. Canada was effectively shut down for business. People were not allowed to visit loved ones in hospital or nursing homes. Travel had ground to a halt. But, in the minds of the soulless and spiteful bureaucrats, none of this constituted “extenuating circumstances”.

Thankfully, Divisional Court Justices Matheson, Varpio and O’Brien were having none of this nonsense. They clearly stated the decision by bureaucrats that there were no extenuating circumstances was “unreasonable.” (I would have, and will, call that decision much worse things). The Justices pointed out the obvious. There was clearly a public health crisis at the time, and that many leaders, including politicians were calling on physicians to get the vaccinations done.

More importantly they stated something the OMA’s legal team really needs to take a deep dive into:

…”that the wording of section 17.5 does not limit relief to unpaid claims; it only requires the presence of extenuating circumstances. Since OHIP typically pays claims first and reviews them later, a restriction on unpaid claims would effectively nullify the provision. The court called this interpretation unreasonable.”

Currently OHIP pays physicians whenever they bill. Later, OHIP decides if it was reasonable or not, and if OHIP feels the situation is unreasonable, they demand the money back. The justices seem to be saying this process is not fair. Which has implications far beyond this one case. Obviously, this would not apply to clear cut cases of fraud. It is a much much needed kick to the slow, incompetent, and spiteful OHIP review process. I can’t possibly understand the potential future implications for this – but I suspect there will be many.

Finally, the justices let their displeasure be known by ordering OHIP to pay Dr. Ma $10,000 in court costs. This strongly suggests to me that they were peeved at the OHIP bureaucrats for taking it this far, and really didn’t think it should have gone there.

How is this hurting health care now?

Ontario is currently seeing an unprecedented surge in flu cases. Flu season has come early. The current variant appears to be extremely strong. It is circulating at “sky high” levels among young people. Three children (at least) have died. Hospitals have declared outbreaks and wards are closed. Visitation has stopped.

Sign on the door to the Medical Ward of my Hospital

You know what would really help? If only some people would come up with some innovative ways of getting their communities vaccinated against the flu. Yes this year’s flu shot is a bit of mismatch for the current strain, but it still provides some protection and keeps you from getting really ill.

Or how about an innovative idea for where to safely look after patients like was done during the Covid crisis. My friend Dr. Bryan Recoskie set up a unique 18 bed ward in our local Legion, to look after non-covid patients while the hospital wards were shut with covid positive patients.

Dr. Bryan Recoskie

And yet, I don’t see any of that happening right now. Don’t get me wrong, doctors continue to go to work. We continue to care for the sick and continue to comfort those in need. We continue to do our best in these trying circumstances.

But I can’t find any evidence (please correct me if I’m wrong) – of where people are doing unique out of the box things to try and mitigate the currently unfolding nightmare. Given the potential exists that IF you try something unique, you may wind up undergoing two years of pure hell by bitter, ruthless and depraved bureaucrats – can you blame people for not trying?

To quote a good friend of mine, “The damage has been done. Nobody is going to stick their necks out now.”

What should happen (but won’t):

First, under no circumstances should OHIP appeal the decision from Divisional Court. The mercilessly inhumane bureaucrats need back down. Second, Health Minister Sylvia Jones needs to do what she should have done a year ago – and direct the bureaucrats not to seek any recovery at all from Dr. Ma. It’s just the right and decent thing to do.

Finally, it would really help if Minister Jones issued a formal apology to Dr. Ma for how she has been treated by the bureaucrats. It’s not just the OHIP bureaucrats. Jones’ own communications director, Hannah Jensen claimed Dr. Ma had “pocketed the funds“, a statement that clearly suggested malfeasance.

Do that, and maybe, just maybe, physicians would once again feel comfortable coming up with out of the box solutions for crises that are occurring.

Maybe.