Dear OMA Board Member, About That Mandate for Negotiations

Dear OMA Board Member,

I read, with interest Ontario Medical Association (OMA) Board Chair Dr. Cathy Faulds update last Friday. There’s the usual information in there about the goings on at the OMA (which sadly not enough members pay attention to, though they should). Critically for most members however, was this comment by Dr. Faulds:

“The board will hold a special meeting at the end of September to finalize the negotiations mandate for use by the Negotiations Task Force (NTF)..”

This is a big step in the negotiations process and to truly understand that, members need to understand what a “mandate” is. Allow me to briefly expand on what Dr. Faulds wrote. The short version is that a mandate is the minimum offer the NTF can accept from the government. If the government offers an increase that is equal to or exceeds the mandate, then the NTF will automatically accept that offer on behalf of the Board.

The corollary to that, which some Board members did not understand when I was on the Board, is that if the mandate is met, and the NTF accepts – then it will automatically mean that you as a Board have to accept the offer as well. As per Board rules, you will then have to endorse the government offer to the membership. You can’t very well tell the NTF “you must achieve XYZ”, and if they do achieve XYZ, turn around and say it’s not enough.

Therefore, it is incumbent on you as a Board, to make sure the mandate is sufficient for the membership as a whole, given the times we live in, and the environment around us.

To that end, without spilling specific secrets, I will state that there was quite a lot of discussion about what an acceptable mandate was during my time on the Board. There were some Board Members who wanted to be “reasonable” and some who wanted to take a hard line and keep the mandate high.

I would, respectfully, point out that for the most part, mandates are never met. Usually the NTF comes back to the Board with “we tried – but this is the best we could get” and presents that to the Board. To be clear, I’m referring to all labour negotiations in general, not just physician ones. Negotiations Legal Counsel told us this last time, just ask them. Whatever you (or any Board) sets as the initial mandate, there is a strong chance the NTF will come back to you later and ask you to lower that mandate.

You will need to keep that in mind when setting your mandate.

To that end, I would encourage you to recognize that the time really has never been better to set the bar extremely high for the NTF mandate. It’s not just that physicians are considering leaving the profession. It’s not just that health care is collapsing all around us. It’s not just the ongoing problems with not just recruiting, but retaining physicians. You already know about all of those issues in excruciating detail.

No, the reality is that we now also have some significant competition for physicians within Canada from other provinces. And I mean strongly significant.

Not sure how many of you have seen this summary form the recently approved Physicians Services Agreement (PSA) in Nova Scotia. On the surface there would appear to be a fairly minimal 10% raise over four years. A deep dive however shows significant add ons like improved parental benefits, funding for overhead, funding to hire allied health care professionals, funding for admin work, enhanced FTE and income stabilization for specialists and so on. That plus a retirement fund!

Similarly, in Manitoba, their recent agreement was widely hailed as a landmark and a game changer. I spoke to a friend of mine from Manitoba who confirmed that it too contains things like a retention bonus ($21,000 and higher for those in rural communities), funding for admin time, funding for new models of care, additional funding for those patients who are older and an equity lens applied to fees. In short, the increase is widely viewed to be in the double digits percentage wise per year.

Look, I know the NTF knows all the stuff I’m pointing out (but others who read my open letter may not). I also would acknowledge that Dr. Mizdrak is a fine chair for the NTF and is (in a very good way and said with total admiration on my part) a real pitbull on behalf of the profession. I also have full confidence that the NTF did it’s due diligence in reviewing the many asks by the leaders of all the specialties.

But at the end of the day, it is up to you, dear Board Member to set the minimum acceptable deal (mandate) and it is up to you dear Board Member to ensure that Ontario remains a competitive place to attract physicians.

To that end, you must ensure that if there is a negotiated agreement, it must at least equal the increase in Manitoba or Nova Scotia (whichever is higher). Anything less would, quite frankly, be rightly viewed as the Board selling the profession out. (If we wind up going to arbitration, that’s a different story – but at least we will have gone there because the Board refused to take a sub optimal deal).

All of which is a long way of saying that since it is quite likely that an initial mandate may not be met, it is incumbent on the Board to set a mandate for the NTF that is HIGHER than what was achieved in Manitoba/Nova Scotia. This will allow for the usual process of the NTF having to come back and say what parts can be achieved and what can’t, and allow some wiggle room.

If you set the bar lower, well, frankly, I have to wonder how you can justify saying that you are advocating for the Doctors of Ontario.

Yours truly,

An Old Country Doctor.

Dear Premier Ford, You Know You’re a Conservative, Right?

Dear Premier Ford,

I’m not exactly your harshest critic. I actually support some (not all) of what what you’ve done in health care. Moving procedures from hospitals to outpatient clinics, building new hospitals, enhanced funding for paediatric mental health, are good steps. I hope there will be more commendable steps in the future.

Ontario Premier Doug Ford makes a health care spending announcement

However, I would be remiss if I didn’t point out that the health care system is going to be under a lot of fiscal pressure in the next couple of years. The remuneration that taxpayers pay for front line health care workers is about to increase drastically.

You will note, I hope, that I said “taxpayers” pay. I, like you in the past, try to avoid saying “government money”. The money to pay for health care and other services comes from the pockets of the little guy as a certain politician once put it. Calling it “government money” is just a way to deflect the public from the truth.

At any rate, you are no doubt aware that the nurses in Ontario got a well deserved 11 % arbitration award. You are probably aware that negotiations for a Physicians Services Agreement in Ontario are about to begin. Given that Manitoba just negotiated a record overall funding agreement with their doctors, and Nova Scotia doctors got a significant increase, you will not be able to hold the line against physicians getting an increase in Ontario.

Which of course means that many more health care workers will want an increase too. In short, there is going to be a lot of fiscal pressure on the taxpayer in the near future.

With that in mind, I will confess that my biggest disappointment in your management of health care is that I can’t honestly see that your government has reigned in the bureaucratic bloat that has so hampered the ability of front line physicians (and other health care workers) to look after patients properly.

Bureaucratic bloat is common in all government agencies. I greatly admire politicians who’ve made comments about needing to “end the gravy train” that provides jobs for bureaucrats and a myriad of consultants at the Provincial Government. Perhaps it’s because I live it daily, but no where does this gravy train seem to be so prevalent as health care.

Let’s look at digital health in Ontario for example. You have Ontario MD, which is an arms length agency that claims to be “the only truly provincial digital health network in Canada”, whatever that means. When I was on the OMA Board, OntarioMD was funded by taxpayers around $18 million a year.

But wait, you also have eHealth Ontario, that claims to be “creating a secure electronic health record information system so that all your medical information can be safely shared and accessed by your health care providers“. If I can decipher their audit statements correctly, they get a further $234 million dollars in revenue.

But that’s not all. The Ministry of Health has not one but TWO separate departments that appear to deal with health IT issues. Their organizational chart clearly shows a bureaucrat in charge of Health Services for an Information and IT cluster. She has her own team of well paid bureaucrats. Yet there is another bureaucrat in charge of Digital and Analytics strategy all with his own team of well paid bureaucrats. The Digital Health Branch of the Ministry of Health had a budget of almost $324 million in 2021/22.

And this is where the waste comes in. You have three agencies (one with two departments) to deal with one field, all reporting separately, none of whom necessarily agree with the other on what to do next. I saw this a lot at government when I was with the OMA. So progress was significantly impaired in digital health because not only was there not one vision amongst the agencies, but because every single issue went back and forth between the three agencies to try to get alignment (to cover the asses of the Sunshine List bureaucrats in case something went wrong). As a result, we are far behind every developed country (except the United States) when it comes to digital health.

I remember a politician who said:

“What drives me crazy is when you have a supervisor in government, and they report into 12 other supervisors. That’s unacceptable.“

That’s exactly what happens with the digital health care strategy in Ontario.

But moreover, the same thing happens in every single branch of the health care system. I mean seriously, if you already have a Clinical Care and Delivery Branch of the Ministry (see organizational chart) why do you need a separate arms length agency like Cancer Care Ontario? Or Ontario Drug Benefit? Or a myriad of others? They should be rolled up into the Ministry. There are many more examples but you get the point I hope.

If you were to simply stop funding OntarioMD (which in my opinion is no longer useful) and the scandal plagued, eHealth Ontario (which completely failed in its mission anyway), that would represent a savings of $250 million. At $100,000 each, that could pay for 2,500 front line nurses. Clearly nurses who provide front line care are more needed than bureaucrats who go around in circles.

The bureaucrats will no doubt fight you if you tried to do this. They will produce reams of power points and glossy manuals (all on the taxpayers dime of course) saying their work is important. But seriously, what would you expect from those who are accustomed to the gravy train?

Conservatives are supposed to be about reducing government waste, decreasing bureaucracy and efficient delivery of services. These are age old principles that, to be honest, I have yet to see from you as Premier.

If you don’t want to heed my advice, might I suggest that you instead take to heart the advice of the politician I mentioned above who wanted to end the gravy train and reduce the reporting to 12 other supervisors nonsense. That politician? A guy by the name of Doug Ford.

Respectfully submitted,

An Old Country Doctor.

The Admin Burden That’s Really Killing Family Practice

Recently, there’s been a lot of talk about the “administration burden” faced by family physicians. The Ontario College of Family Physicians estimates family doctors spend up to 19 hours a week on “paper work”. Given there are only so many hours in a week, the more hours spent doing paperwork, the less hours seeing patients.

It also contributes to situations where people just get too frustrated with family medicine, and quit. Twenty percent of Toronto family doctors are planning on leaving within five years. This bad karma is not lost on medical students, who, as I mentioned in a previous blog – are avoiding family practice like the plague, worsening a crisis that has been years in the making.

But what exactly is this “administration burden”? What’s the “paper work” that is driving us all to frustration? I would argue it’s not paper per se, it’s digital.

That’s not to say there isn’t paper. I frequently get asked for completely pointless sick notes from employers, impractical forms to return to work and seemingly useless – “we agreed your patient was permanently disabled, but we want a one year update to make sure your patient is still permanently disabled” forms from the pointy headed bureaucrats at insurance companies. But I’ve taken a somewhat mercenary approach to those forms in order to keep myself sane.

A sick note costs $20 and takes about a minute to write. A form the insurance company asks for usually takes a few minutes to fill out and I charge $40-$175 depending on the form. I reconcile the fact that these forms are a burden, with the fact that at least I make money out of them. While somewhat unscrupulous on my part, it keeps me from totally blowing my lid whenever I see one of these.

No the real admin burden comes from the completely absurd and unrelenting avalanche of reports/lab work/follow up notes – all of which present to me in a haphazard way, seemingly designed to drive me to psychiatric medications.

I took the Friday of Eid ul Fitr off to celebrate with my family. On Saturday, I logged into my Electronic Medical Record (EMR), correctly realizing that if I waited until Monday, the EMR inbox would crush my sorry soul.

Unsurprisingly, I had a total of 75 labs/reports/messages about patients to review. It wasn’t so much the number of items to take care of, (truly if they were straight forward it wouldn’t have been too bad). It was rather how badly and inefficiently the information came to me that sucked all of the happiness I had enjoyed on Eid from my spirit.

One method of getting information to me is via a system called Hospital Report Manager (HRM). I look at HRM in my EMR and see a report on a renal transplant patient from Sick Kids. But the note was “uncategorized” which meant that I had to go into the HRM software and enter the category “nephrologist” in the report. The VERY NEXT report in my HRM in box was……the exact same report on the exact same patient, but this time HRM had categorized the report as being from a cardiologist – so I had to go in, change the report once again to “nephrologist” and I now have two copies of the same report.

By the way – Sick Kid’s hospital provides exceptional medical and nursing care to my patients, but ever since they switched their hospital IT systems to a company called EPIC there has been no end of issues like this. The only thing that software is epic at is causing physician distress.

That’s not all. HRM has more goodies awaiting for me. There’s a report from my colleague Dr. Collings on his expert management of a wrist fracture on one of my patients. Thorough, comprehensive, and well done. Except HRM has auto-categorized him to be a gynaecologist So yes, I either have inaccurate information in my patients chart, or I go back and re-categorize the report to reflect that Dr. Collings is an orthopaedic surgeon.

Next up, HRM has a report from an Emergency Room physician about a patient who was seen and apparently had some abnormal bloodwork. Not life threatening, so asked to follow up with me. Only problem is the blood work from the hospital doesn’t come to me via HRM. Now I have to go to that patients chart, and access yet another system called OLIS, log into that and download the lab work from the hospital. But wait the note from the ER was unfortunately late getting to me (about 10 days out). OLIS is set up to auto download for the past seven days, unless I click more buttons, and back date – which I have to do.

Next up, a report from HRM that a patient of mine had a Covid swab done. But HRM won’t tell me if the swab was positive or negative. Just that it was done. Now I go back to that patient chart and access OLIS where the result is, adding yet more steps to my day.

Next come messages (yes, that’s on top of HRM and OLIS). I note a message from the local Shoppers Drug Mart asking for a renewal of blood pressure medications for a patient of mine. Only problem is that a brief look at the chart shows I sent a one year supply of that same medicine to the Shoppers three months ago, and they accepted this and downloaded it. I tell the pharmacy staff who tell me they “can’t find it” which leads to……well, let’s just say a deterioration in the conversation.

As an aside, while I’m not allowed to endorse any specific pharmacy, I will say I’ve generally found care to be much better when provided by smaller, independent pharmacists who build relationships with their patients, rather than big chains that just seem to fly in itinerant staff.

Anyway, you get the point. In total it took about 3 hours on Saturday to sort through this mess and it just doesn’t have to be this way. The reason I wrote a blog about Health IT in Turkiye was to show that other countries do a much better job of managing this burden. I’m sure there are other examples and we need to learn from them.

The vast majority of my family practice colleagues practice family medicine because they genuinely like their patients, like providing comprehensive care, value the relationships built over time and feel like they make a difference in peoples lives. But unless we do something about this administration burden, I fear more and more will leave the profession, because at some point, being human, they just won’t be able to take it any more.

What if We Didn’t Lose the Doctors We Trained?

Canada is in the midst of doctor shortage. In particular there are at least 6 million Canadians with out family doctor. The situation is worsening. The most recent Canadian Residency Match for medical students applying to specialties, showed that there were 268 empty spots for family medicine after the first round. This is the highest number of unmatched family medicine positions ever. Medical Students, being really smart people, are viewing family medicine as a dead end specialty and avoiding it like the plague.

If only the boorish loudmouth who predicted we were heading in this direction six years ago and been listened to…..

Governments at both federal and provincial levels are taking steps to try to address this. In British Columbia, they have introduced a capitation based payment model for family physicians (think of it as salary + performance bonuses). Ontario has a model like this that had great success in the early 2000’s. The federal government pledged more spending on health care in the future. Ontario plans the “largest expansion of medical school education in ten years.” And so on.

But what would have things been like if successive governments didn’t drive doctors away from Canada in the first place?

Going back as far as the 1990s, inept governments have, over the years, done their best to make physicians feel unwelcome. The Bob (“I am super elite“) Rae NDP government of 1990-1995 in Ontario implemented the Barer-Stoddart report. This report decided “there were too many doctors” (I kid you not) and cut medical school enrolment by 10%. Three decades later we are still feeling the adverse ramifications created by that move.

Similarly, the disreputable Kathleen Wynne Ontario Liberal government went to war with physicians in the mid 2010s, led by her woefully incompetent Health Minister Eric Hoskins, and his inept sidekick, Deputy Minister Bob Bell. Those geniuses thought it was a good idea to CUT 50 residency positions (training for doctors) and only saw the light during a deathbed confession just in time for the 2018 election. In particular, Hoskins and Bell’s blatant disregard and borderline contempt for family physicians resulted in, as OMA Vice-Chair Audrey Karlinsky put it, 6 years of family medicine graduates not choosing comprehensive family medicine.

Do you think supporting hundreds of those young potential family docs then would have made a difference now when 2.2 Million Ontario residents are without a family doctor?

To prove that idiocy in health care management can occur with parties of all political stripes, the former Alberta Conservative Health Minister, the combustible Tyler Shandro, actually verbally attacked a physician at his home in Alberta, along with, you guessed it, going to war with physicians in his own province. Really helps to retain physicians, no?

In my first ever blog for the Huffington Post (seven years ago!), I pointed out to then Health Minister Eric Hoskins that 30% of my graduating class no longer worked in Ontario due to Bob Rae’s intransigence. I urged Hoskins to change his behaviour or that by the time of the next election, health care would be in a worse crisis and hinted his government would pay the price in the 2018 election. (I wonder if Kathleen Wynne regrets sticking with him as health minister for so long, despite the fact he was obviously not up to the task).

Admittedly, that’s one person’s recollection. Are there any statistics out there that show just how many Canadian trained doctors have left Canada? There are, although they are really hard to come by, and not as up to date as I’d like. Huge shout out to Dr. Mary Fernando for digging these up for me.

In 2000, the OECD published a report on the mobility of health care professionals. On page 50, it indicated that 19% of doctors born in Canada were working in other countries. Given the crisis we see in health care around us right now, do you think it would help if we could have retained those doctors in Canada?

But wait, aren’t we trying get international medical graduates (IMGs) to come to Canada? Ontario health minister Sylvia Jones did direct colleges to come up with a way to speed up the ability to get foreign doctors licensed. But it turns out we have trouble keeping them as well. A study on retention patterns of IMGs in Canada showed that 12% of IMGs were approved to practice in Canada between 2005 and 2011 LEFT Canada by 2015. While IMGs apply, we have trouble retaining them too.

Clearly, governments need to focus on retention of physicians just as much (if not more so) than recruiting new physicians. What can they do?

The federal government can do a couple of things to help. First it can heed the results of a poll taken by the Medical Post magazine (I voted just before closing and these were the results):

Doctors don’t have pensions and benefits mostly due to some weird federal tax laws. Changing these should be easy and offering pensions and benefits would be a strong way to retain physicians. Similarly, reversing the 2017 tax changes that completely threw retirement planning out the window for doctors would be a big help.

Provincial governments should of course, take note of the fact that going to war with doctors always leads to a deterioration in health care for the residents of their province. But since most politicians are incapable of thinking about anything but their own self interest, let me point out three facts.

In 1995, after going to war with doctors, the Bob Rae NDP government was turfed from power in Ontario and the NDP has yet to form a provincial government since. In 2018, after going to war with doctors, the Kathleen Wynne Liberal government was decimated in the Ontario election, even losing official party status, which they have yet to regain. In 2022 after going to war with doctors, Alberta Premier Jason Kenny had to resign as premier because his own party saw the writing on the wall.

The message is clear. Going to war with doctors is bad for health care and bad for political careers. It’s time politicians realized that, and came up with meaningful solutions like pensions to retain the ones we train.

Canada’s Health Care Landscape has Changed Since the Canada Health Act

I’m honoured to have Dr. Silvy Mathew guest blog for me today. She’s a former member of the OMA Board, former member of the Physicians Services Committee, has a Master’s in Health Policy and Economics, a Certificate in Global Health and is hands down one of the smartest people I know.

Health care in Canada is governed by the Canada Health Act, a federal act that essentially states that medically necessary care provided by physicians and hospitals, will be covered by public insurance and administered by each province. 

The Act was passed in 1984, and is reflective of the type of acute medical care practiced at the time. However, in 2023 (and for at least a decade prior), medical care, through technology, medical advancements and aging, has changed drastically. Publicly covered care now, however well intentioned, is sorely lacking. Ironically, because of that, it is also very expensive.

For exampe, we lack public pharmacare  for adults despite being promised this by 2006 by then Prime Minister Paul Martin. (There is some pharmacare for seniors and children).

We lack dental care. We lack appropriate home care in an aging population that is getting weaker and frailer. We lack coverage on physiotherapy. In an era of increasing mental health burdens we lack psychotherapy.

The list goes on and on, notwithstanding the severe social issues that contribute to many of these issues (healthy food, exercise, housing and all the other social determinants of health).

Because we have not invested upfront, we pay significant costs in expensive procedures, prolonged hospital stays, and medications much of which could be minimized or avoided.

Why does it matter?

McKinsey Global Institute published a prospective analysis of 200 countries, looking forward on the impact of 52 diseases over the next two decades to quantify the social and economic gains if health is made a priority by government and private sector.  They quantified the value of health to the economy and showed that if using the existing interventions we have today, we can reduce disease burden by 40% in the next 20 years and extend “active middle age by 10 years”. This translates to an economic return of $2-$4 for each $1 invested. That’s remarkable. 

What’s the hold up? The lack of foresight, upfront cost and political inertia is costing us.

We have a shortage of healthcare professionals, and we use the ones we have, in extremely inefficient ways. For example, the lack of a proper digital health infrastructure in Ontario (like they have in Turkiye!) results in duplication of services, poor coordination, and inconsistent delivery of health care. Even the electronic services we DO have don’t capitalize on Artificial Intelligence (AI).

Technology advancement is a double edged sword. There are benefits to patients in terms of ongoing updated guidelines for care. But health care workers are having to do more, monitor more and change practice styles more, all leading to more individual HCW time.

Each test, often results in further testing or reassessment down the line, which compounds the problem. It’s rare that physicians just close the door on one issue a day.

Again, at the time of the Canada Health Act, we were practicing acute, limited health care. Today’s world is focused on prevention and chronic illness with monitoring. That shift has placed a huge burden on physicians time to review, inform/educate, coordinate new referrals and remind individuals to do monitoring.  Much of the time, it seems like we still don’t know how much benefit we will get from this. Hopefully the data will show we were correct to do this.

To collect and review the data though, we would need better digital systems to capture the information, which we don’t have.

Some people imply this will be managed with more “healthcare team members”. I think a huge solution for this particular issue is investing in technology and AI solutions.

Right now, we are trying and failing at holding back an avalanche.  We have technological advancements, but limited access to those. We have lack of integration of our digital infrastructure. An ageing population is leading to increased needs. But an aging health care work force is seeing retirements and illness leading to less access. New providers are available but their impact is less clear due to lesser training and duplication of services leading to increased costs. Delayed diagnoses are leading to worsened health outcomes and more expensive care. There is less preventative care due to a shortage of family physicians which leads to delayed diagnoses, worsened health outcomes and more expensive care. Lack of care giver support and home care support means that people are leaving the workforce to care for ill relatives which leads to hospital dumping. Burnout is endemic in health care, due to a feeling of disrespect and an inability to practice best patient care.

And so, physicians are in all areas of the country are giving up and closing their practices.

In the meantime, while we wait for our wishes to come true, there is opportunity to push the envelope and to drive change. People are desperate and they want options.

When access to health care is inadequate, people will choose out of jurisdiction options for delayed procedures and even screening tests. There is a moral hazard involved. People are taking risks by going elsewhere under the assumption that they will be taken care of properly.

However, with any challenges, there are opportunities. Some “non-medically necessary” medical tests (eg. screening for vitamin D) are not covered by medicare. However, it’s increasingly viewed as an early intervention. We will only see technology increase these options as better screening methods become available, and governments delay paying for them. Perhaps instead of waiting for open heart surgery or stenting, there may come a day where preventative procedures can be used to dissolve plaque in the heart arteries.

Health care faces inescapable and exponential change. However, it is unlikely, at least in the near future, that Canada (or any country’s) public health system will be able to keep up with technology and demand.

Oh for some strong, principled leadership that can see these challenges and address them head on, without resorting to political sound bites.

•

RePost: Ontario’s Heading For Another Family Doctor Shortage

This is the follow up blog to my last one, originally published in the Huffington Post on June 13, 2017. Reprinted here so that I can keep track of my old blogs, and also to once again point out how warnings of a crisis in Family Medicine were ignored for years.

The Barer-Stoddart report. Ask any physician of a certain age and the immediate reaction is likely to be disparaging. Written in 1991, it purported to help chart the course of the physician workforce into the 21st century. 

While it’s true that much of the report was ignored by the Ontario government of Bob “Super Elite” Rae, it’s still widely remembered for suggesting that the number of physicians in Ontario needed to be cut by 10 per cent. To accomplish this, medical school enrollment was slashed in the early 1990s.

Given that the population of Ontario continued to grow and age, the result was completely predictable. A massive doctor shortage (particularly in family medicine) hit the province at the end of the decade. It has taken the last 15 years to come close to correcting that. We’re not there yet (we still have fewer doctors per capita than Mongolia), but we were improving.

Alas, Ontario Health Minister “Unilateral Eric” Hoskins and Deputy Health Minister Bob Bellwere unable to remember the old saying, “Those who cannot remember the past are condemned to repeat it.”

Former Health Minister Dr. Eric Hoskins

Last week I blogged about how Hoskins and Bell need to support family medicine. Because they are not doing so, many physicians who graduate from family medicine residencies are not starting comprehensive family practices. Instead, they are doing things like hospitalist work, sports medicine and even medical marijuana clinics.

However, the situation is even worse than I thought. It was pointed out to me after my blog was published that the number of medical students applying to family medicine programs has dropped considerably this year. In Canada, to become a practicing physician, you first have to graduate from medical school, then do a residency (essentially a training program) in the specialty of your choice. To choose a residency, you apply to CARMs — which is a Canada-wide program that matches medical school graduates to the residency of their choice.

This year’s CARMs match shows some alarming results for family medicine in Ontario. Ideally, we should have 45 to 50 per cent of all graduates from medical school apply to family medicine for a sustainable workforce. However, only the Northern Ontario School of Medicine achieved that goal. While it’s a great school, it’s still the smallest of Ontario’s six medical schools.

By comparison, only 24 per cent of graduates of University of Toronto applied to family medicine, 27 per cent of Queen’s graduates, 32 per cent of Ottawa’s graduates, etc. Multiple studies show that comprehensive family medicine is responsible for decreased health-care costs, more efficient utilization of the health system, better patient outcomesand decreased hospitalizations. It is essential for a sustainable health-care system to have a strong family medicine component. The fact that so few medical school graduates chose family medicine, on top of the fact that recent graduates are not opening practices, should be setting off alarm bells.

So, why is this happening? First and foremost, it’s because Hoskins and Bell have refused to support family medicine. They have talked loudly about how they want to cut payments to higher paying specialties so that they could fund family medicine. Hoskins even went to the trouble of doctoring (pun intended) a chart to accuse specialists of overbilling. 

(Seriously, see the picture in this article. Notice how he made the pie chart on the right larger — the whole circle, not just the wedge showing percentage of billings. Makes the red area look LARGER than it really is, and makes the specialists look they are billing disproportionately more than they are.)

Unfortunately, while Hoskins and Bell were saying this in public, what they were actually doing is cutting family physicians. They unilaterally cut the number of physicians who could apply to the capitation (salary plus performance bonus) models of funding that I mentioned last week. This is the preferred method for paying physicians for newer graduates, and also for health care bureaucrats who like a predictable budget. Additionally, they cut a number of the performance bonuses family physicians got for looking after complex patients.

Medical students are not dumb. They saw all of this going on, and realized that family practice was no longer preferred by Hoskins and Bell. So they made career choices accordingly.

Currently, the Hoskins/Bell legacy is not a pretty one. It’s one of internecine disputes with doctors, laid-off nurses, hospital deficits, patients in stretchers for days and egregious wait times. At least with family medicine, they have an opportunity to begin to correct this mess by once again allowing new physicians to enter the capitation model, and restoring the various performance bonuses.

Failure to do so will mean that many years from now, as patients struggle to find a family physician, Hoskins and Bell will be remembered with the same disparaging legacy as Barer-Stoddart.

RePost – Hoskins and Bell Need to Support Family Medicine

The following is a reprint of an article that I wrote for the Huffington Post on June 5, 2017. Re-posting here so that we can see how the seeds of declining family physicians was planted by Drs. Eric Hoskins and Bob Bell, and also so that I can refer to it in the future if needed.

For the past 23 years, it’s been my pleasure to be a preceptor with the Rural Ontario Medical Program based out of Collingwood. As a preceptor, I have had the honour of supervising a wide variety of Medical Trainees, from first year Medical Students, all the way up to those in their last year of Residency. 

I often find I learn as much from them as they learn from me (it’s good to be questioned by students about why you do things the way you do). I clearly have some experience on my side, and they have more recent book knowledge. It’s a great combination for patient care.

Unfortunately, I can see that we are once again heading for the same situation as the late 1990s/early 2000s, when many medical trainees stopped going into comprehensive family medicine. The reasons then were due to increased workload, better opportunities in other specialties and an extremely poor relationship with the government of the day. 

At one point, only about 25% of graduates from medical school applied to Family Medicine Residencies. To suggest that there was a crisis in family medicine would be dramatically understating the issue.

However, the Conservative government of Mike Harris finally realized you need to co-operate with doctors if you want to improve patient care. In 2000, Health Minister Elizabeth Witmer rolled out something called Primary Care Reform (PCR) in co-operation with the Ontario Medical Association (OMA). This, over the next few years, led to a revitalization of Family Medicine, and now, close to 40% of medical school graduates are once again choosing Family Medicine as their specialty. 

While not the sole part of the PCR, a major component was a new model of paying physicians known as capitation. Capitation is essentially salary plus performance bonuses. Family Physicians would be paid a certain monthly rate to look after their patients, regardless of how often they saw them. They get bonuses based on how many complex (eg. Diabetic) medical cases they take on. This was in stark contrast to the old system known as Fee For Service (FFS) where physicians were essentially paid piecemeal (only got paid when they saw a patient).

The capitation based models were extremely popular with both Family Physicians and government. For Family Physicians, it allowed them to spend the time needed with patients during just one visit, instead of requiring multiple visits. For the government, it provided a predictable funding envelope. I appreciate this will come as a surprise to a couple of the frequent critics of my articles (in the comments), who have long implied that I was critical of Health Minister “Unilateral Eric” Hoskins because I was allegedly supporting the FFS model, but I actually have been in a capitated model since 2004.

Drs. Bob Bell (left) and Eric Hoskins

Did PCR work? In 2001, the population of Ontario was 11.4 million, and almost 3 million people didn’t have a family doctor. In 2016, the population of Ontario was 13.9 million, and only 800,000 did not have a family doctor. So over 4.5 MILLION people got a family doctor.

Then along came the hapless “Unilateral Eric”, and his widely disliked sidekick, Deputy Minister Bob Bell. “Unilateral Eric” likes to claim that he himself is family doctor. The reality is that he has NEVER provided the cradle to grave care that comprehensive family doctors in Ontario do on an ongoing basis. He does work a day a month at a walk in clinic, and I understand he donates that income to charity – which is good of him, but it’s hardly the same as what comprehensive family doctors do. 

Bob Bell for his part, likes to boast about how he used to be a family doctor back in the 1970s, but he seems to be unable to grasp that family medicine might have evolved since then.

Acting with the same level of competence as Tweedle Dee and Tweedle Dum, the infelicitous duo of Hoskins and Bell unilaterally cut the number of family physicians who could apply to capitated funding models. Again, this is likely a surprise to a couple of the critics of my columns, who have long been demanding that physicians go on salary. Surprise, it was Hoskins and Bell who unilaterally stopped the salary style models, not the OMA. They also unilaterally cut some of the performance bonuses (for things like diabetic care, medical education and so on).

The result was clearly predictable to anyone who understands Family Medicine in the 2010s. Over the past three years newer graduates from Family Medicine programs are avoiding comprehensive care. Many of my trainees are choosing to work solely in areas like emergency, anaesthesia, sports medicine or others. And while there is a need for doctors in all fields, the reality is that it’s comprehensive Family Medicine that leads to health system stability. 

It’s comprehensive Family Medicine that reduces hospitalizations. It’s comprehensive Family Medicine that when supported properly, reduces costs of health care.

In response to this, the dolorous duo of Hoskins and Bell unleashed something called the New Graduate Entry Program (NGEP) to provide new family medicine graduates with what they claimed was a capitated funding model. Alas they attached so many conditions including a morass of bureaucratic oversight that I understand only two new graduates have taken them up on this offer.

Hoskins and Bell have left a legacy of a crumbling health care system with their arroganceand unilateral cuts. 

However, they still have the ability, and opportunity to begin to correct one of their most egregious mistakes. A new crop of Family Medicine Residents will graduate on July 1. Hoskins and Bell can unilaterally reverse the cuts to the capitated models and performance bonuses. No one from the OMA will complain.

It’s time for them to recognize the important role of comprehensive Family Physicians, and support that with actions, not just words.

Will Pharmacy Prescribing Improve Health Care?

Pharmacists do a great job as part of a health care team. In hospital and nursing homes, I get expert guidance on dosages of potentially dangerous medications. I am also fortunate to have community pharmacists on a secure electronic messaging platform to discuss issues around medication complications/interactions/dosages and so on for my patients.

But, will it improve health care to let them treat minor conditions?

I expressed my displeasure on Twitter about the recent move to allow pharmacists to treat certain minor ailments:

A few pharmacists were not amused. It was pointed out to me that Ontario is one of the last provinces to allow this, and that it has “worked well” in other provinces.

But what exactly is the definition of “working well”? Politicians love it, mostly because it allows them to say “see we are taking steps to make your life easier.” Patients love it because they can say, “Jee, I think I have a bladder infection, now I can just get the antibiotic when I want.” Of course patient satisfaction will be high.

Unfortunately, as I wrote about a few years ago in the Huffington Post, patient satisfaction does NOT correlate with good health care or outcomes. As counter intuitive as it may seem, higher patient satisfaction scores correlate with a 9% higher cost per patient AND a 12 percent higher hospital re admission rate. Patient satisfaction should not be used as a metric to determine any health care policy.

On Twitter, Nathan McCormick suggested that pharmacists have a lot to offer and linked to an article from New Brunswick on how it’s worked well there. Unfortunately (and I stand to be corrected) the article suggests the diagnosis of urinary tract infections was made without a urine culture, or even a urine dipstick test (which is less accurate but still something). So there’s no way to sort out how many people had a true bladder infection, or simply “felt” like they did, which happens. The article also puts a strong focus on patient satisfaction and convenience, which as mentioned above, is not the same as good health care.

Nardine Nakhla asked me to familiarize myself with an article she wrote about how Ontario developed the process. There’s a lot to like in what’s written there:

  • A recognition of overprescription of antibiotics as a world wide problem
  • a focus on ethical standards based behaviour by pharmacists
  • A minimum amount of training for pharmacists before treatment minor ailments
  • The requirement for pharmacists to contact the family doctor or nurse practitioner when treating a minor ailment

Once again this doesn’t really reflect true health care outcomes. It also references the aforementioned New Brunswick article and specifically stated there was high patient satisfaction there.

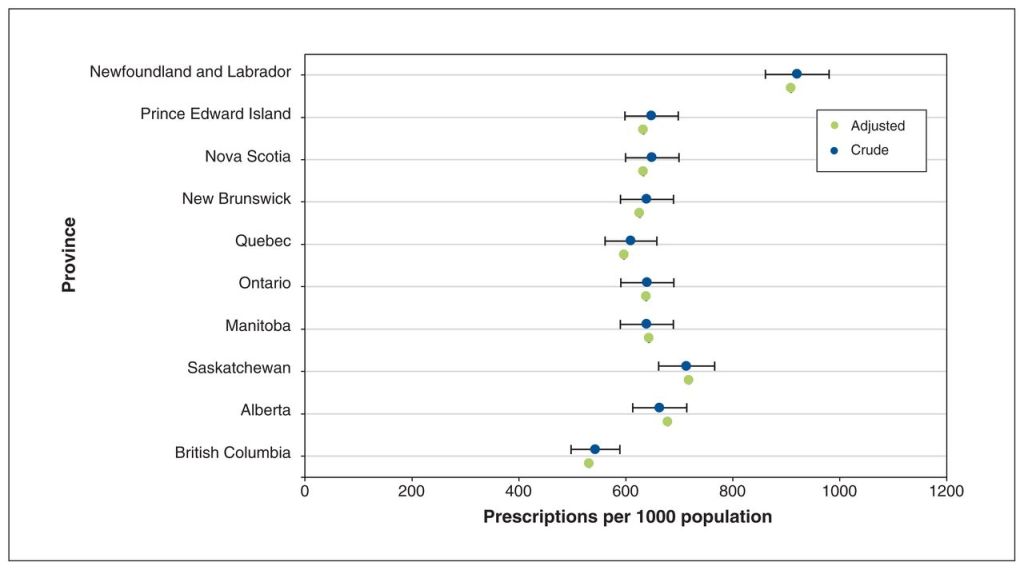
Let’s look at just one area of concern, antibiotic usage.  Global overprescription of antibiotics is a world wide concern.  It leads to increasing antibiotic resistance and the formation of new, drug resistant bacteria.  A look at Canadian data shows that there is intra provincial variation in the number of antibiotic prescriptions.  Newfoundland, where pharmacists have been treating minor ailments for years, has the highest rate of antibiotic prescriptions. British Columbia, where pharmacists are expecting an expansion of their scope this spring, had the lowest.  

From CMAJOpen: Interprovincial variation in antibiotic use in Canada, 2019: a retrospective cross-sectional study

World wide , of the ten countries with the most antibiotic use, Cyprus, Romania, and Greece allow them to be purchased directly from pharmacies. (I stuck to EU countries with more modern health systems for examples).

Kristen Watt wrote a piece in the medical post criticizing physicians for complaining about these new powers and asked me on Twitter to provide evidence from other locations.  She stated that Ontario was “15 years behind the trailblazing Alberta”. And yet the data in the CMAJ article above shows that Alberta has a higher rate of antibiotic prescriptions per capita.

One area I do agree with her is when she wrote:

“the government roll-out video, shot in a noticeable big box pharmacy, didn’t help us”

That big box is Shoppers Drug Mart, and their CEO Jeff Leger is seen promoting this change on the video.   Shoppers Drug Mart recently invested $75 million in Maple, a virtual care company.  Maple’s home page still shows the following:

Screenshot from Maple as of Jan 12, 2023

Gee, if you think you have a sore throat, you can just call a company (that Shoppers invested in), and get an antibiotic without a throat swab (who cares if it’s really strep) and lo and behold, there just happens to be Shoppers nearby that will deliver it to you. Yes, I know patients can request the pharmacy of their choice, but….

Look – there are other aspects of this process that need review.  Accurate diagnosis of a rash for example (several of the new pharmacist powers are for skin ailments). Or communication with the patients family physician about the treatments given.  Probably more.

I WANT pharmacists to help.  I really truly am grateful that so many are willing to step up in a time where our health care system is collapsing faster every day. But I want pharmacists to help in ways that support good health care outcomes.

 Might I offer three suggestions for how pharmacists can do that:

  1. As a group, they can petition Shoppers Drug Mart to put pressure on Maple to change the example on their website.  It’s great marketing (focusing on convenience) but terrible health care.
  2. Get involved with Choosing Wisely, Canada’s leading group looking at all ways to pick the right health care treatments.  There doesn’t appear to be a pharmacist in looking at their leaders.  I think pharmacists could provide extremely valuable information on not just anti-biotic stewardship, but also overall medication management (eg. reducing pill burden in the elderly)
  3. Strongly lobby the government for a unified integrated electronic health system that will allow them secure communication with physicians and access to limited health care data (eg creatinine clearance).  We’ve got this in my neck of the woods, and it’s a huge benefit to physicians, pharmacists and most importantly patients.

In order to save what’s left of our health care system (if that’s even possible now) we need to focus on health care outcomes, and ensuring proper an appropriate care. Doing the three things I listed above would be a big help in that direction.

What Backlogged Health Care Looks Like and How to Fix It.

Dr. Silvy Mathew guest blogs for me today. She is hands down one of the smartest people I know. She writes about her experience in visiting the ER to help a family member. Dr. Mathew has been a strong advocate for health system reform and it is a loss for all Ontario residents that her warnings about the impending crisis in health care were not heeded by Health Ministers dating back to Eric Hoskins.

A few days ago I was in the Emergency Room (ER) with a family member. The ER was slammed. The paramedics were lovely and about four teams that I could see were stuck in waiting room, waiting for their patients to be triaged. We were on a stretcher by the front sliding doors. Almost outside.

We were there for urgent imaging, and possibly consultation. We tried to do this in the outpatient setting, but lack of access to both urgent images and consults for urgent care makes that impossible. So we go off to ER by EMS (needed for transport).

I’m fortunate. I am able to fill in gaps. I can advise triage what issue is, as they can’t do physical exam in the waiting room in front of what seems like hundreds of people. I can provide medical information on relevant questions. I can monitor the patient status for changes.

I did remind staff after several hours to check blood sugar as my relative is an insulin dependent diabetic, now off food/fluids. I did remind about necessary medications to be given. Of course, if I wasn’t there, they may have reviewed the chart closer but they were clearly slammed and trying to manage.

And we weren’t in distress. My family member was unable to advocate for themselves. We got imaging about six hours in, and I watched the imaging staff, working with 50% less nursing staff, literally just running in and out moving people. Doing their best.

We had excellent care from people busting their butts. But so many potential falls through the cracks and errors. Twelve hours later, we got home, luckily without any new issues from ER. And we had a plan. And we had a specialist who called first thing in the a.m. to ensure we have close follow-up.

The system in Ontario has relied for decades on individuals and work-arounds making things work (like above) when the system design is archaic. Successive Ontario governments have refused to participate in strategic multi-pronged co-design, instead of piecemeal band-aids.

I have worked for 15 yrs in Ontario health care. I’ve witnessed how far things have fallen and how none of our work arounds previously used are available now after the Covid 19 pandemic, for multiple reasons. I’ve participated with the Ontario Medical Association and sat on bilateral committees with the government to try to advocate for system change.

I’ve witnessed how siloed and unaware most people outside of primary care are. Family Medicine is the canary NOT the Emergency Department. The issues that have caused this system collapse have been occurring since 2012. Many of us, especially Dr. Nadia Alam, tried to be loud and warn.

Last year, in 2021, we gave up. It was obvious to us it was too late. We heard for years from our mid-career colleagues about how they couldn’t do this anymore. How they wouldn’t work in a system that didn’t allow them ANY joy or success while taking more and more from them personally.

Covid-19 just pushed the dial a bit faster. The family doctors who were hanging on from retiring have chosen to live now (not leave, but LIVE). The mid-career family docs are struggling as mentioned above and also choosing to leave family medicine if possible, because nothing is working in it. Obviously, new graduates are terrified.

And so here we are, and the CCFP answer to this is to ADD a third year to residency. Because somehow they think adding more school, asking people to take on more debt, delay starting their lives longer, while having less non-academic preceptor support will somehow help?

What it will do is: add even more fuel to the family medicine crisis and shortage. It’s not gonna teach you how to run a business (last I checked real life experience mattered more). It’s not going to teach how to manage complexity in real life. It WILL drive more people out of family medicine residency.

What we REALLY need is a re design of the health system. You want people to do this job? LET them. You want family doctors to work at the top of their scope? ENABLE them. Support access to resources OUTSIDE of hospital and provide help to coordinate.

Stop advocating for more debt and school CCFP, and advocate for real life mentorship, group practices and shared care. You want Emergency Rooms to not house people? Fund home care and long term care. Fund resource teams to support those in seniors neighborhoods already. Use a community approach.

While we are at it, stop spending all the money on pharmacology. Fund allied health, encourage exercise programs and healthy meals because that’s WAY more useful than the hundreds of thousands of dollars of Botox we spend on contractures AFTER they occur. Keeping people mobile keeps them out of hospital and long term care.

The Canadian media can stop asking if health care has collapsed, anyone working in it knows it has. It will show in a year or two, when the numbers of late-diagnosed cancers, life expectancy and other markers of care get affected. But in real-time we are seeing it now.

If we don’t have some real leadership here and some true innovation, we are in for some truly sad times in the next decade. End.

Does Ontario’s Digital Health Strategy Meet Our Needs?

That the health care system is currently in a state of crisis is no secret. That we need to look at bold, radical transformation of the health care system is no secret. That fixing health care means fixing family medicine first is well known. But in order to do all of this, we must finally fix the mess that is digital health infrastructure in Ontario (indeed, all of Canada).

If you speak to any health care worker about Digital Health/Electronic Medical Records(EMR)/Health Information Systems(HIS) you are most likely to elicit a loud, pain filled groan. EMRs have long been cited as a leading cause for physician burnout. Incredibly, 7 out of 10 physicians (!!) have some form of EMR induced stress.

Even the Surgeon General of the U.S. stated that EMRs needed to be fixed (Dr. Glaumcoflecken’s “there are so many clicks” is the exact response you’d get from me):

The reality however, is that there is a bad way of implementing a digital health infrastructure and a good way.

A bad way would be what the four hospitals in my neck of the woods did last year. Implement Meditech Expanse with it’s cumbersome modules, painful clicks, restrictive algorithms and emesis inducing user interface. Better yet, force doctors to learn this odiously inhumane system in the middle of a pandemic when they were already burnt out. The obvious result? At Collingwood Hospital (where I still have privileges but may not after this blog), many family doctors are leaving citing this as a main cause. (Piss off people who are already burnt out, and they leave, who knew?)

A better way of doing things would be to set things up the way my colleague Dr. James Lane did in (ironically enough) the Georgian Triangle region of which Collingwood is a large part. Set up a system where the whole community is on one EMR. Then allow limited information sharing with allied health care providers. Start with pharmacists, then add in home care providers. As a result, there is secure information sharing between health care providers allowing the optimization of patient care.

Some recent examples from my practice:

  1. I renew a prescription for amiodarone. The pharmacists messages me back on the patient’s chart (no faxing, no finding the chart etc) letting me know that the cardiologist had actually reduced the dose of the amiodarone, and I immediately correct the prescription.
  2. The wife of a patient with dementia is concerned her husband is deteriorating. I send a message via my EMR to the Home Care case manager assigned to my practice. I get a response by end of day saying she’s contacted the wife and will arrange for an in home assessment. (This doesn’t solve the problem of actually finding staff to do the work of course, but at least I know that the referral hasn’t been lost).
  3. I send a CT requisition to radiology for staging of a newly diagnosed cancer patient. The local radiologist has questions so he accesses the chart to look at some of the pathology reports to inform his report of the CT.

There’s many more examples but you get the point. These kind of things can not only enhance patient care, but reduce the admin burden of co-ordinating between different agencies. (I cringe when my friends in other centres talk about how hard it is to get home care to acknowledge that they received a referral much less to do something about it).

But this can only happen if the Digital Health team at the Ministry of Health has the vision, the boldness and the fortitude to force these changes and frankly, I’m not sure they do. I had meetings with some of the Digital Health team when I was OMA President. They are well meaning people who want to improve things. But the strategy they are choosing is doomed to failure.

I probably shouldn’t mention this as it was a closed meeting, but I don’t care any more, and besides, what can they do to me? Stop me from running for OMA President again? One of the senior members of the Ministry’s team explained their strategy to me like this:

“If I want to buy a pair of shoes, I have three apps on my phone that allows me to compare different prices from different vendors, and then I choose the best price. Patients should do that when they access health care.”

Now this fellow was in his 40s, and a university graduate. Clearly he can access multiple apps. Good for him.

But the highest users of any health care system are the seniors and the reality is that they are not as technologically able as our friendly government bureaucrat. Do we really expect an 80 year old with multiple medical problems to flip through three apps if they need health care? What if the apps only access part of the system? You’d need one app to access their family doctor, another to access the hospital and a third to access home care. Would anyone want to do this?

All this will do is increase the plethora of software out there, cause more confusion and a deteriorate the communications between health care providers and add to the work load of physicians (because, you know, we are not already doing enough clerical work).

What about OntarioMD? Aren’t they supposed to advocate for change that will help physicians? I had issues with OntarioMD when I was on the OMA Board. (Long story for another day).

But I do note with interest that OMA Board Chair Dr. Cathy Faulds announced in her Board Report that there is a new mandate for OntarioMD that includes end to end proof of concepts on policy. I personally won’t hold my breath (one bitten, twice shy) but I do acknowledge it’s a step in the right direction. Maybe they can finally get on with some of the work that I advocated for during my term and relieve some of the burden that physicians deal with.

It’s the 21st Century. We still can’t fix the health system without fixing family medicine. But we can’t fix family medicine without fixing digital health. Here’s hoping the powers that be finally realize that.