

Are You Accepting New Patients?

Dr. Madura Sundareswaran guest blogs for me today. She’s a community family physician who’s resume is too long to print here. She helped found the Peterborough Newcomer Health Clinic and is a recipient of the CPSO Board Award which recognizes outstanding Ontario Physicians. This article originally appeared on her LinkedIn page.

The day people stop asking this question is the day we have fixed the primary care crisis.

I’m a family physician doing community-based comprehensive family practice in Peterborough, Ontario. I currently work in three different primary care models in our community – fee-for-service, a team-based family health organization, and nurse-practitioner led clinics. All of my colleagues work very hard providing excellent care to their patients.

Despite this, the latest figures suggest that 32,000 people living in the Peterborough region do not have a family doctor.

What does that look like?

A woman in Peterborough notices a breast lump today and is very worried about it. She frantically searches google and reddit to learn that there are no walk-in clinics here. She calls a number late in the afternoon for a local clinic for unattached patients, but all the spots are full for the day. Her options are a virtual doctor who will never conduct a physical exam – but she thinks an exam is important – how will they ever know what this lump feels like virtually? She wants someone’s expertise, she wants reassurance. She decides to go to the emergency department for this problem…but leaves after waiting for 9 hours. She is guilt-ridden as she waits there – she is not as sick as the others in the waiting room. No physician or nurse practitioner will have enough of a relationship with this woman to know that she recently lost her best friend to breast cancer and the impact this has on her illness experience. She is freaking out about this lump…alone.

Or…

A 68 year old male has seen a few pharmacists and virtual family doctor for his hemorrhoids over the last year. He decides that he just has to live with hemorrhoids. A google search says his symptoms are classic for the problem; he’s reassured. As a doctor, I know that this gentleman needs a physical exam but this man cannot find someone to do it. After a few months he winds up in the emergency department with terrible pain – a physical exam very obviously demonstrates rectal cancer. It’s had a year to grow.

Or…

George is a 58 year old man who has never had a family doctor. He has been on Health Care Connect for four years but no one has ever called him to say they have found him a family doctor or nurse practitioner. He is in “perfect health” so he does not need a doctor. He has never had his blood pressure checked, never been counselled on smoking cessation, and has never had bloodwork done. What he doesn’t know is that his Hemoglobin A1c is 7.4 (he has Type II diabetes but too early for symptoms), he has hypertension (high blood pressure – which in its most common form has no symptoms or signs), and his cholesterol is really high. George will probably have a heart attack in the next 10 years. The potential consequences of a heart attack are death. This was entirely preventable.

What we know: attachment to a regular primary care provider (family physician or nurse practitioner) leads to more preventative care, better chronic disease management, and lower rates of hospital admission (ref)

We need a solution ASAP

I eagerly watched as Ontario announced $110 million that will “connect up to 328,000 people across Ontario to primary care teams.” For my community this also translated to a promise for a community health centre (CHC) to connect 11,375 people to primary care. This is much needed but not enough.

Ontario Health Minister Sylvia Jones announcing expansion of primary health care teams

In order to develop a community health centre – a building must be built or set up, policies will need to be implemented, and several primary care providers including physicians, nurse practitioners, social workers, pharmacists, dieticians, etc. will need to be hired. Even if this could be set up within 12 months, where does that leave the other 20,625 in the region without a family doctor? I’ll tell you – scrambling door to door and still knocking asking if anyone is accepting new patients.

But wait! There are other options. A single full-time family physician working in one of Peterborough’s existing family health organizations can roster approximately 1300 patients and join an existing team-based model. We currently have job openings in every one of our five existing multi-disciplinary teams for family physicians. A clinic could be up and running in a matter of weeks. There are family doctors in this community who are very eligible to take on this job – and would likely consider it if they were fairly and adequately compensated.

Learning from British Columbia

I am a firm believer in learning what works and never reinventing the wheel.

In 2023, British Columbia completely revamped its pay structure for family doctors. They paid their doctors better and restructured compensation models – and apparently within a year they got 700 more doing comprehensive, community-based family medicine.

Dr. Ramneek Dosanjh, Past President of Doctors of BC, who called the new funding formula for family physicians in BC a “seismic shift”

I am going to make a few assumptions but I want to illustrate and oversimplify something here.

  • In the new BC payment model, the pay per full time doctor increased by $135,000/year (assume per full time equivalent). It wasn’t just a pay raise – it involved a few critical changes regarding what doctors could bill for and some restructuring. But the end result was a pay raise.
  • This resulted in an increase of 700 family physicians (assume full time equivalent) practicing comprehensive family medicine over one year.
  • Let’s say 1 full time doctor rosters 1300 patients.
  • If Ontario could get 700 new full-time family doctors to provide comprehensive, community-based family medicine, 910,000 people could now have a family doctor.
  • The entire rollout for the BC program is budgeted at $708 million over three years but this would include complete restructuring from fee for service care. Ontario already invests over $1 billion annually in interdisciplinary primary care teams and we have a significant head start compared to BC a year ago.
  • In contrast, Ontario plans to spend an additional $110 million to connect up to 328,000 people across Ontario to primary care teams.

Providing family doctors with the financial support and resources to set up their own practices is the best bang-for-your-buck approach if the goal is patient attachment to a primary care provider.

We need an all hands on deck approach. Support community health centres, nurse practitioner led clinics, but please also support family physician’s practicing family medicine. That is the only way you will achieve attachment for all Ontarians.

Your most obvious solution is pay family physicians better today – so they will hold off retiring for a couple more years and may actually sign on to take a practice.

British Columbia just proved that fair and competitive compensation for family physicians may result in more of them doing it.

Why do I care?

I have been in family practice for five years. I have a roster of patients who have access to a whole range of team-based primary care services – a pharmacist, a social worker, a nurse practitioner, an RPN and multiple other service through our family health team. Every day I get asked if I can take on a friend or family member as they do not have or just lost their family doctor. This simple ask creates a great deal of stress and guilt for me. I know what happens when someone does not have a family doctor or nurse practitioner. They will be sicker, they may die sooner, they will be alone trying to “doctor” themselves.

The moral distress of being made to feel like I am determining people’s fate – giving some people a high standard of care while others are left to fend for themselves will be what ultimately leads to my exit from this profession in this province. Why do I get to give a small handful of people comprehensive team-based care, while the rest (often marginalized, more vulnerable patients) get nothing? It is not fair.

What next?

We are all eagerly awaiting the next negotiation between the Ontario Medical Association and the Ministry of Health.

If we do not see a pay raise for physicians, or worse, we pay them less – everyone in Ontario can accept the reality that they may have a lovely multidisciplinary medical home with a diverse range of primary care providers – but a family doctor probably will unlikely be part of it.

The next time a leader or politician is raving about their new model for care – or pitch a strategy that does not include a family doctor I urge every tax payer and journalist to ask them:

1.     Do you have a publicly funded family doctor? (Do you truly understand what it means not to have one? Have you ever had to endure the struggle?)

2.     If you are so confident in your plan, would you be willing to give up your family doctor to one of the 2.3 million people in Ontario without one?

3.     Why is fair and competitive financial compensation of family physicians not part of your multi-pronged approach?

We are listening to politicians and leaders sell us on an idea of a fully-funded, glorious renovation. Meanwhile the house is on fire. Your family doctors are a dwindling number of people who cannot contain the flames. What are they worth?

About Asking for Reduced Admin Burden From the MOH….

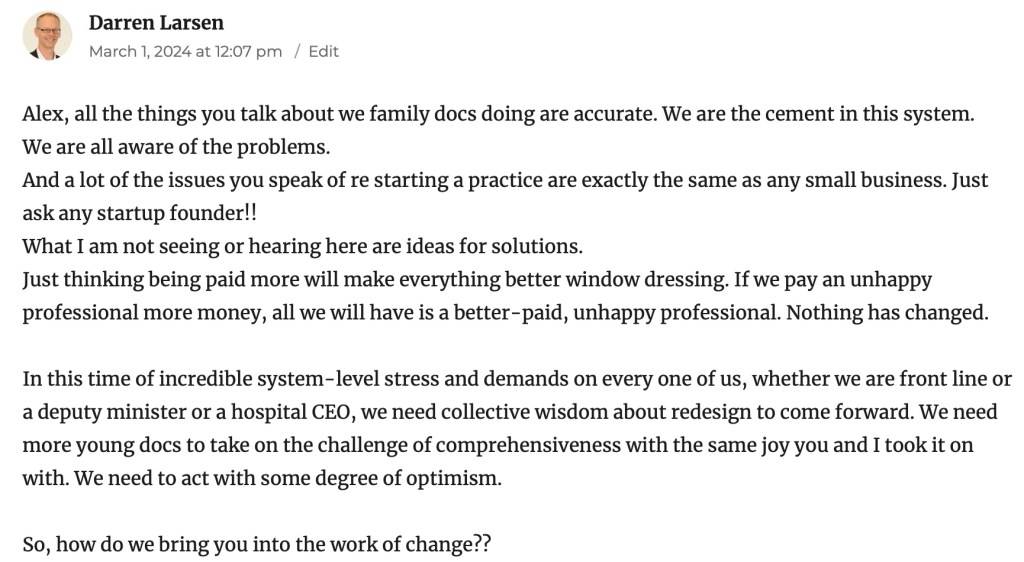
Lots of talk on the net about how the economic model for family physicians no longer works in 2024. My own blog site has had guest posts dedicated to this issue. There has been some criticism of this position. Dr. Darren Larsen in a reply to the post linked above suggests he is “not seeing or hearing…ideas for solutions“. He further states that all paying doctors more will do is create a “better-paid, unhappy professional. Nothing has changed.”

Others have made the similar comments. There is nothing philosophically wrong with the argument to reduce workload instead of raising pay. Practically speaking however, history has repeatedly taught us that the Ministry of Health (MOH) bureaucracy is incapable of delivering on that promise.

Some personal stories:

In the mid 2010s I was a Peer Lead for OntarioMD (no really!). I was frustrated by the Ontario Lab Information System (OLIS) because I had to manually retrieve all the lab work for a patient individually in their chart. Hospital Report Manager (HRM) by comparison, sends reports on all my patients directly to one inbox. (why we need two systems – and now more, is another story). The then VP of OntarioMD informed me they were working on “Practitioner Query” – which would allow me to get all my lab work from OLIS in one inbox. This was supposed to be ready in six months. That was over a decade ago.

From 2014-2018, thanks to the vision of my colleague Dr. James Lane, we developed an integrated health portal as part of our Health Links project for South Georgian Bay. For $35K a year, we were able to ensure that nursing homes could message physicians on their EMR. We dramatically reduced paperwork for physicians from nursing homes, improved health care outcomes, and reduced hospitalizations thus saving the entire health system money.

The MOH bureaucracy couldn’t wrap its head around this and wouldn’t allow it to continue.

For those of you who think I should have told people about this project, I wrote an article in the Toronto Sun about it. Afterwards, I got invited to do a presentation on this with the then CEO of eHealth Ontario and her senior team. Heck, when I was a keynote speaker at OntarioMDs Every Step conference in 2019 (no really!) I presented this project. The then head of the MOH Digital Health Team was there and heard it. Still, the bureaucracy couldn’t see their way towards allowing a project that saved physician time (and improved health care outcomes) could continue.

Ok, ok, so this blog is just for me to complain about not being listened to right? Well no, there are multiple other examples.

One workload issue for family physicians is keeping track of which of our patients get immunized for which vaccines. If only there was a central tracking system that sent the information to us directly. Wait, there is! The Covax system for tracking Covid vaccinations. Obviously the easiest and most sensible thing to do is expand the already existing system to add all the other vaccines so we get notified (eg when public health gives Gardasil). Yet 3 years after Covax, the MOH can’t even make this simple common sense change.

More? When I was on the SGFP Executive, one of our senior physicians told us the story of how he was on a working group to make the schedule of benefits (the fee schedule for Ontarios doctors) easier. After six months of meetings, they made a decision to add a comma to the descriptive sentence of one code. One comma in an 800 page schedule.

I could go on but you get the point. It’s fine for the MOH to say that that they promise to reduce the Admin burden for family docs. But frankly to these aged and cynical ears, it just sounds like them saying “This time we really mean it, honest!” – kinda like when Lucy promised to hold the football down for Charlie Brown for real this time, with predictable results.

Look, we have a five alarm crisis in family medicine in Ontario. Just about every week brings a story of another physician who is struggling with the economics of running a practice, and is considering quitting.

As with all emergencies, we need to have an effective triage system in place. Deal with the most urgent thing first, then go on to other things. We clearly can’t wait until 2034 for the MOH to implement some of the workload reducing schemes they might have (and no matter how much they promise they really mean it – it will take that long). So the first thing that needs to be done is bring financial stability to family practices so that they can continue to function while we sort out everything else.

Now, given Ontario physicians are in the midst of negotiating a new contract with the Ontario government, I expect the MOH team to say to our own negotiations team something like – “I know you guys want X% increase, but we can only give you 1/2 of that, but we promise to reduce your admin burden so you are working less hard”. I would do the same if I was them.

But, my expectation, and the expectation I think of the majority of doctors in Ontario, would be that the OMA negotiations team looks at the MOH team, and quotes the best engineer in the history of Starfleet to them.

With apologies to Geordi Laforge, B’elana Torres, Trip Tucker, Jett Reno, Andy Billups, and Hemmer – but Scotty was the BEST ENGINEER in the history of Star Trek!

The first step towards fixing the crisis in family medicine is a new physicians service agreement that stabilizes family practices. Once that’s done, work can begin anew on health systems transformation/workload reduction and so on. To try to do it the other way round, or even hand in hand, is a recipe for further collapse of the health care system.

Dr. Alex Duong: The Challenges Facing an Early-Mid Career Family Physician

Dr. Alex Duong, a family physician from the Vanier district of Ottawa (which amazingly enough is one of the more underserviced areas of Ontario).

Recently, Maria DiDanieli, the clinical lead for system navigation at the Burlington Family Health Team, published an opinion piece in Healthy Debate that was critical of the decision of Drs. Alam/Mathew and yours truly to recommend that family practice residents bide their time instead of starting up a comprehensive care practice in Ontario. Dr. Duong replies and has kindly allowed me to reproduce his reply here.

I am a full-time community family physician, and I read this article with great disappointment.


I am at the face of our health care system. When patients cannot get a timely breast biopsy or a knee replacement, they come to ask me. I address their frustrations, alleviate their pain, and manage expectations.


I am the backstop when issues are missed during transitions in care and issues that require follow up.


I am the navigator that helps patients, and their families orient themselves to housing resources, mental health and financial resources.


I am the advocate for my patient’s health when they deal with their employer or insurance companies.


I do all these things and more, alongside everything from newborn care to palliative medicine.


I, like the great majority of family physicians, take pride in our work, and in what we contribute to our patients and the community at large. But Banks do not grant loans for a new clinic based on my contributions to Ontario’s healthcare system. My rent payments do not decrease because of the positive impact I make on my patients’ lives. The salaries of our exceptional staff are not funded by the sound of clanging pots and pans.


Today, to outfit a new clinic with the minimum number of physicians for a FHO requires high 6 figures to 1 million dollars, loaned at 6.95% interest. We guarantee our own lease – we are on the hook for ensuring it gets paid for the entire term. We are responsible for hiring and ensuring our staff are paid a living wage. We invest our own time in making sure the clinic runs. For many community family physicians like me, there is no assistance for any of this from any level of government. No money for staff, no incentives for starting up, no support for logistics. We are in a precarious, failing business model with ever growing administrative burdens patching the system equal to a part-time job. We have been trying to expound on this, and frankly have been completely unsuccessful in this.


You realize that “… there does not seem to be much political will to improve this situation at this time.” Yet, you ask family physicians to work harder expecting a different result from the government.


You state that “With these current barriers and shifts, any new practice can feel fragile or vulnerable to imminent obsolescence.” Yet, you expect new graduates to take on a massive financial risk: long term lease, EMR contracts, and double their already tremendous debt in start-up costs.


You lament that “Instead of acting as beacons of wisdom, encouragement and level-headed advice, we see a growing shift toward inciting everyone to walk out!”. Do you apply this standard to the teachers in Quebec who recently concluded a strike? Are they less dedicated to their students? Do you apply this standard to all groups who organize to make their voices heard?


The authors, Drs. Alam, Gandhi and Mathew made it clear that there are many options available to new family doctors. They warn of the current state of specifically locking into comprehensive family medicine, to ensure that new grads do not put themselves in a position where they will be burnt out early in their career. To me, leadership requires honest conversations, not empty promises, or exploiting the ideals of new family doctors. I find it unethical to sell a romantic vision of what it is like to start and maintain a Family Medicine practice in the current environment. It is a recipe for moral injury when those ideals run flat into the economic realities, as I have experienced.

And frankly, to say to those of us, like myself, still practicing longitudinal family medicine we should be working harder, or we are just doing family practice wrong is demoralizing. It is grossly offensive to my early-mid career family medicine colleagues who have burnt out through great moral struggle and guilt. Disillusioned family physicians who leave longitudinal family practice will not return. The greater harm to the public and to patients is not the Star article that speaks truth to the issue, but the issue itself: that family physicians, whose concerns are being gaslit, continue to leave longitudinal practices.

Another Open Letter to the OMA Board: Re-visit the Negotiations Mandate

Dear OMA Board Member,

Just me again. The grumpy, aged quack with a history of being a bit of a thistle in your obliques. Well intentioned I assure you (although I’m told some may not see it that way).

Negotiations with the provincial government on a Physicians Services Agreement (PSA) continue and mediation began on February 20th. That’s all great and part of the process. However, things HAVE CHANGED a lot since the last time I wrote to you and urged you to set a strong mandate.

I am asking you to revisit the negotiations mandate at this time, in light of three new key pieces of information that are very relevant to Ontario doctors.

To recap – the negotiations mandate is the bare minimum ask that the Negotiations Task Force (NTF) can accept on behalf of the Board. If the government makes an offer that meets or exceeds that – well, then they accept it on behalf of the Board and the Board is compelled to endorse it. The mandate is, quite correctly, confidential (you can’t let the other side know your bare minimum ask any more than they would let you know their mandate). But it’s up to the Board to determine if the mandate is enough (not the NTF).

Now to be clear, I’m not saying you should revise it, just revisit it. Perhaps the mandate is already sufficiently strong. That would be great. But things are different now.

The first reason to revisit the mandate:

Other provinces have surpassed Ontario physicians in terms of income. BC and Saskatchewan have significant deals to stabilize the physician work force. Manitoba’s deal with physicians appears to be the best of the bunch. Manitoba has not only a well deserved increase for all physicians, but significant steps towards gender pay equity.

As an aside, while I applaud the fact that DoctorsManitoba made steps towards gender pay equity, I’m forced to wonder what happened to Ontario? When I was on the OMA Board we were proud of the fact that although it was too late, we were the first PTMA to report on the issues around gender pay equity. We proved that the pay gap was not because “women work less hard”. What happened ?

Also, to be clear I want to acknowledge that the negotiations counsel (Messrs Goldblatt and Barrett) are very well aware of any topic that could affect negotiations. I remember Darren Cargill, who at the time was on our NTF, told me “they read everything.”

Therefore, I know they read the Manitoba Schedule of Benefits which is available online and reported back to you. I’m sure you are fully aware of the retention bonuses in that deal. I’m sure you know about the significant changes that decrease the gender pay gap. I’m sure you know about the fact that Manitoba pays physicians for Admin time. And that their capitation model has no negation (although a lower base rate). And that they have an age premium. A pelvic exam premium (gender equity again). And that they allow extra payments for dealing with more than one problem at a visit. I have absolutely no doubt that our negotiations counsel has fully and thoroughly advised you of this, along with the benefits of the deals in BC and Saskatchewan.

The second reason to revisit the mandate:

The crisis in family medicine is spiralling out of control, faster than I thought possible. Not only is it badly affecting patient care, but the health, well being and morale of physicians is sinking like a stone. Last September, I never dreamed that I, along with Drs. Alam and Mathew, would write a letter to Family Practice residents telling them to stay away from comprehensive family medicine in Ontario. I never dreamed that there would be story after story after story of individual family physicians openly talking about how they were burning out. This situation has gone form bad to desperate frighteningly quickly.

The third reason to revisit the mandate:

Bill 124, the piece of legislation that limited increases to the public sector, was used to promote a low ball PSA to us the last time. You even, admittedly and embarrassingly, convinced a guy who should have known better. It’s ruled unconstitutional and the government will not appeal this. In fact they will repeal the Bill entirely. In light of that, many other public sector workers will be asking for catch up pay.

So it really is time for you to re-visit the negotiations mandate. Just double check to make sure it’s as strong as it should be given the above factors. Make sure it takes into account that the the BC deal has attracted over 700 physicians to comprehensive family practice. Make sure it recognizes that Manitoba will likely be showing a net growth in physicians shortly, and can reasonably attract physicians from out of their province. If you have to revise the mandate upwards after looking at it, then do so.

NB – IF the NTF were to push back if you do revise the mandate upwards, then make sure you hold your ground. Remember, YOU are the Board and YOU give direction to ALL committees and task forces, including the NTF. I’ll be careful how I say this so as not to divulge Board confidentiality, but the NTF in my day did have a proposal on one particular issue (not the whole PSA) that they told us to approve and our Board pushed back and said no. We had to listen to some (quite eloquent) speeches about how hard they worked and this undermined their work and so on and so forth – but after that they went back and kept negotiating as directed. Don’t do any less this time.

These negotiations are likely to make or break the profession for decades to come. They are that important. You owe it to your members to take another look at the mandate.

Yours truly,

An Old Country Doctor.


