

The FHO+ Model Alone Won’t Save Family Medicine in Ontario

Disclaimer: I’ve looked through the OMA page on the FHO+ model and interpreted the data as best I can, BUT, this information should NOT be used by others for their own financial planning – they should review the data for themselves. Additionally, because this is a complex model – if the OMA’s Negotiations Task Force feels there are mistakes – I would be happy to correct those.

Last week, the OMA announced that they and the Ontario government had developed an enhanced model for paying family physicians. In Ontario, the most popular model for paying family physicians is something called the Family Health Organization (FHO). More physicians would choose it, but in typical unthinking and regressive fashion, the bureaucrats at the MOH convinced the government to limit entry into that model in the 2010s – because you know, why would you want people going into family medicine to have their preferred payment model? What were they going to do? Stop working as family doctors? Sigh…..

The OMA website states the new FHO+ is the “Future of Family Medicine” and talks glowingly about how this will “bring back the joy of family medicine, and build a foundation to support recruitment and retention”.

It’s always tough to break things down with a new model, and there are a lot of variables and enhancements to review. I encourage all family physicians to watch my friend Dr. Adam Stewart’s set of truly excellent videos on this new model.

For my part, I consider myself to have a medium sized practice. I therefore looked at Dr. “B” on the OMA’s web page to come up with my thoughts. (Note to OMA – come up with some better names for the doctors!)

  1. How much of an increase in income am I going to get?

According to the OMA site, I should expect an increase of 13% of my gross income. But it’s not clarified what the baseline for that increase is? Is it this year’s income? Last year’s? So I emailed the OMA and was given this answer:

“The base rate the parties agreed to use in our costing was FY2023/24, keeping in mind the last permanent increases were on April 1, 2023, the recent years 2.8%, 9.95% and the monthly relativity for FY2024/25 are all temporary and will end on April 1, 2026.”

Alright, some more math (my apologies). Let’s use fiscal year 22/23 to start. Let’s assume I grossed $X in that year. For FY 23/24 – that was the last year of the previous PSA and we got a 2.8% increase in fees. So I grossed $1.028X that year. FY24/25 was year I of the current PSA and we were awarded 9.95% by the Arbitrator (compounded to the 2.8%). Because there was no agreement on how to divide it up, it was distributed equally among all docs. So I grossed $1.13X.

Still with me? This year, FY 25/26, by mutual agreement, there was a relativity based increase from the original FY 22/23. FHO docs like me got 11.7% so this year, for now, I will be grossing $1.117X. This is down from last year but may change based on whatever happens in Arbitration.

Based on the OMAs reply, if FY 23/24 is the base year they used in their calculations (when I made $1.028X) then and increase of 13% on that will translate to $1.161X. In essence, if FHO+ goes through, it will mean a 4.4% increase for me next year, compared to this year (1.161-1.117) and a mere 3% more than last fiscal year. Better than nothing? Sure. Is it the major dollar influx needed to save family medicine? I think you know the answer to that.
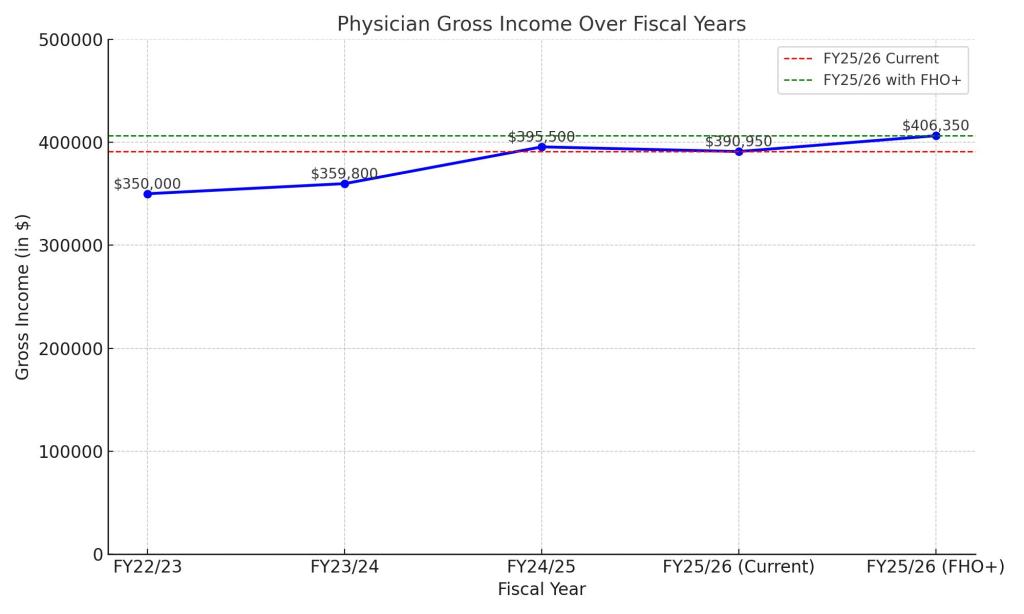
Graph showing a hypothetical growth in gross income for a category “B” family physician who billed $350,000 in FY 22/23

2. How will rural medicine fare?

One of the things that strikes me about this model is that effectively, rural medicine will not do as well. Now, in fairness, there are attachment bonuses for taking on new patients, and those bonuses are higher in rural areas. So there is that. But my understanding is that rural doctors are working overtime anyway and not really able to take more patients right now.

But what should be noted is that in the OMA calculations, the assumption has been made that doctors are getting at least some access bonus currently. So let’s look at Dr. Rustic and Dr. Metro, a rural and urban doc.
Let’s assume they also fall into category “B” as per the OMAs example. It is well known that urban doctors, despite how hard they work, have challenges getting the access bonus. Dr. Metro currently gets an access bonus of $0 because there are five walk in clinics with 15 minutes of her office. This is despite her group working after hours care. Dr. Rustic on the other hand, gets $25K in access bonus, mostly because his group is the only game in town.

With FHO+ the access bonus gone and repurposed to pay for other items (and that is a very good thing as my friend Dr. Mark Linder pointed out) in effect, Dr. Metro’s raise will be $25k MORE than Dr. Rustic’s. I don’t begrudge Dr. Metro the income, she deserves it. But in order to recruit in rural areas, we’re going to have to find a way to bump Dr. Rustic’s income more.

3. What exactly will the Accountability Metric be?

This is of course, the great unknown. These metrics are often presented as “reasonable” and then governments always find a way to make them unreasonable. We won’t know the answer to that until after Arbitration.

Final Thoughts

At the end of the day, I think family doctors as a whole need to realize that FFS family medicine has gone the way of the Dodo bird (I know this will upset some FFS purists). The government also seems to recognize this and as part of the agreement is increasing the number of FHO+ positions.

Dr. FFS, Family Physician

Despite some of the concerns above, I do think that FHOs should migrate to the new model. It is slightly more money, and I do wonder if by tweaking your practice more – the amount can go up. For example, I have about 200 patients whom I have not rostered because of outside use issues – I would now roster them – and this would increase my income even more. So I suspect there is potential to make more than a 4.4% increase if you manage your roster well. Looking at increased shadow billing rates also offers some potential for more growth.

However, saving family medicine requires a multi-pronged approach that requires a single, unified health information system, family practice teams with physicians clearly placed as the leaders of the teams (with funding for leadership roles) and much more than a 4.4% increase in income. So take the money for now, but don’t in anyway shape or form believe that this in and of itself will fix family medicine.


Unrelenting Bureaucracy is Killing Health Care (and Canada)

Canadians are currently dealing with the dizzying spectacle of Donald Trump’s tariffs against our country. On again? Off again? Delayed? Doubling? I’ve personally gotten seasick trying to keep up with whatever tangerine Palpatine is thinking.

U.S. President Donald Trump – aka the Tangerine Palpatine

However Canada’s response to this (and the nonsense about us becoming the 51st state) has frankly been quite lacking. Yes, it’s great to see Canadians being able to fly the flag with pride, especially after the miserable co-opting of the Canadian flag by the freedom convoy types, who likely themselves were Donald Trump supporters. (How’s that working out for you guys now?) Yes #elbowsupCanada is a wonderful approach to take and a great mantra going forward, particularly with how intertwined hockey is with our nation. (Quick reminder: Not only do we win Olympics, we win Four Nations Cups as well).

BUT, for all the outcropping of (absolutely warranted) national pride – our governments – outside of launching retaliatory tariffs, haven’t done anything to fix the systemic problems in our economy. For example, getting rid of domestic trade barriers and having free trade between provinces would provide a boost of up to $200 billion dollars to our economy, but seemingly no action on this yet.

Even more importantly and what’s long overdue, is an absolutely necessary look at the bureaucracy and impediments that many businesses face in trying to contribute to our economy. Let me talk about a personal experience (and no disrespect intended to the good people on staff in my township).

About 10 years ago, our community had clearly outgrown the medical centre. Some poor sap was put in charge of expanding it. (Guess who.) I had to deal a myriad of problems of putting an addition on our medical centre. Here’s a couple of examples of what I dealt with.

As per policy, the township requested that we provide an engineered site plan. The reason for this was to assess water drainage requirements. While on the surface this makes sense, all the engineered site plan was going to tell us what size of culvert to put on our property for water drainage. The estimate for the site plan was about $15,000.

A sad, lonely culvert, passing its life away draining water…

However, it turns out there were only two sizes of commercial culverts for our project. A big one and a small one. The big one cost $500 more than the small one. Being well-versed in the obstinacy of Ontario Health’s bureaucrats, but somewhat naive in the inflexibility of municipal bureaucrats, I offered to simply put in the bigger culvert right from the start in exchange for waving the engineered site plan.

Those discussions went as well as my less naive readers will expect. The site plan wound up costing $17,000, and it told us that we had to put in the big culvert.

Want more? The township requested a $250,000 letter of credit or certified cheque prior to approving the expansion of the building. My initial reaction was somewhat negative to this request, but upon reflecting, I did realize that it made sense. The request was put in place in case a builder started a project, ran out of money before they finished the project, and left a hole in the ground. The money would then be used to pay to clean up the mess they made.

I still grumbled about the fact that the township was making long term doctors who were clearly invested in the community do this, but I have to concede that it was fair.

The bank informed me there’s some complex fee formula for a letter of credit – and it would have cost $5,000. I asked them for a certified cheque, and it turns out banks don’t do that anymore. However, they were willing to issue a bank draft and the fee for that was $50. Obviously, I got the bank draft instead.

When I went to the planning office however, I was told this was unsuitable. The contract we signed specifically asked for a Letter of Credit or Certified Cheque and I had presented neither. Therefore we had not met the terms of our contract and the project would come to a halt. The staff person did offer to take this to the planning committee, and six weeks later they decided this was ok.

Is this me just griping? Nope – in fact his is happening all through health care and businesses in Canada. I recently spoke to the owner of a Nursing Home. His home had been approved on a “fast track” for a new build based on the dire shortage of nursing home beds in Ontario. I asked when the facility would be built and he just laughed. Apparently “fast track” means that there will “only” be 30 months of paper work (!) before the shovels go in the ground and he hopes it will be completed in 5-6 years!! I’m guessing this “fast track” must be on Toronto’s Eglinton LRT line….

A sad, lonely train on Toronto’s much, much, much delayed Eglinton LRT line

Want more? Just look at the saga of my local hospital, the Collingwood General and Marine. We’ve known for almost two decades that it’s far too small for the community. Heck the community has been asking for a new hospital since the early 2010s and finally got approval on phase 1 (of 5) in 2016. And 9 years later (!) we are at phase 3. The “hope” is that the new building will open its doors in 2032 – 16 YEARS after it was absolutely clear a new hospital was needed immediately.

This problem is not restricted to the health care sector of course. The Financial Post had a piece in 2019 (!) about how these rules are affecting multiple industries. Not only are we not building critical infrastructure in a timely manner because of an inability to cut the bureaucratic bloat, but it’s stifling private businesses as well. The Canadian Chamber of Commerce pointed out that the “ease” of doing business has gone from fourth in the world in 2006 to 53rd now, and this impedes economic growth and investment.

New Prime Minister Mark Carney is off to Europe this week to build trade and strengthen relations. Nothing wrong with that, we need reliable trade partners in the future. BUT, we face an unhinged, hyper volatile situation with our neighbours to the south RIGHT NOW. It seems to me there is no better time than now to drop intra Provincial trade Barriers and right size the bureaucracy allowing for businesses to grow and thrive more easily in Canada. As for health care, the right time was 10 years ago.

Prime Minister Mark Carney

Health Care in the Ontario Election: Lots of Sound Bites, No Strong Policy

Last week, I had the opportunity to talk to Greg Brady, on his 640 am radio show, Toronto Today. The episode is on Spotify and, if you are in need of a great cure for insomnia, you can catch me starting from about the 19:30 mark:

Six and half minutes is not enough time to discuss health care in Ontario. Neither is a 1,000 word blog, but that won’t stop me from trying to expand on some of my thoughts.

The first and most prevalent thought I have is disappointment in ALL of the political parties for how they have addressed health care so far. Everyone on the front lines of health care has known for a least a decade that we need bold transformative changes in how health care is run and delivered in Ontario. Probably all of Canada.

And yet, the four would be Premiers all fail to outline a plan for such transformation. Instead, they have all resorted to that age old political vote grabbing stunt of saying “Let’s just throw more money at the problem” without actually reminding you that the money is going to come from YOUR pockets and is going to be, frankly, poorly spent.

The Conservatives hired Dr. Jane Philpott to oversee a spend of $1.8 billion in a plan to connect everyone with a “primary care provider” in the next few years. As I’ve written before, that plan, through no fault of Dr. Philpott, who I have a great deal of respect for, is doomed to failure.

The Conservatives did not start the downfall of family practice in Ontario (that was the miserable Eric Hoskins/Bob Bell duo during the wretched Kathleen Wynne years). But they sure haven’t done enough to fix the mess they inherited. Economist Boris Kralj, PhD, recently showed in the Medical Post that Ontario lost 238 family physicians in 2022/23 – the biggest loss of any province.

The Liberals for their part want to spend 3.1 Billion dollars. At least they promise everyone a family doctor and not a “provider” (and yes, there IS a difference, a BIG one between the two). However, their plan amounts to spending $1.3 billion more than the Conservatives. Spending more without changing things seems naive at best.

The NDP promise to recruit 3,500 more doctors, promise family doctors for everyone, cut red tape, establish a “Northern Command Centre” for health care (that’s actually a good idea) – all for the low low price of only $4.1 Billion dollars, a billion more than the Liberals.

The Green Party promises are actually the most detailed I could see, including lots of goodies, like recruiting more doctors, building more nursing homes, increasing nursing student spots, hiring 6,800 personal support workers and more. There is only one thing missing from the proposal (at least on their website). How much this will all cost YOU, the taxpayer.

Ontario spends $81 billion in taxpayers dollars on health care. Rather than look to see if that money is being spent wisely, and looking to transform health care, all the political parties are simply giving us sound bites. They promise to spend $83-$85 billion on the same failing system, without looking at changing things. Because spending more inefficiently will surely fix things.

OK Smart Guy – What do YOU Think Should Be Done?

Glad you asked dear reader, glad you asked. At an absolute minimum I’m looking for a party that has the political courage and wisdom to do the following three things.

First, A complete hiring freeze on all bureaucrats in health care, including not replacing those who retire, or leave for other reasons.

Currently Ontario has 10 times as many health care bureaucrats per capita as Germany. That’s too many. This means that any meaningful suggestions for change have to go through so many bureaucrats that the whole system is plagued with paralysis by analysis. Time to trim the fat.

Second, ensuring one, and only one, patient app that every resident of Ontario has, which will have access to all their health care data, and allow them to share this with the health care specialist or facility of their choice

Ontario is a digital health nightmare. Your health information often times can’t be shared if you go from one hospital to another, or one doctor to another. There are multiple inefficiencies and unnecessary repeat tests because of this mess and it should never have been allowed to occur.

It would be too expensive and too time consuming to force every health care facility to use the same electronic medical records system. What can be done however, is to force all the systems to integrate with ONE patient app. This will ensure a common standard, and moreover will allow a hospital you happen to be in, to access your out patient information (with your permission) which just doesn’t happen now.

Third, ensuring strong family physician representation at the board level of the Ontario Health Teams.

There is a lot of talk about the benefits of team based care. As someone who views one of his proudest achievements to be the founding Chair of the Georgian Bay Family Health Team, I would agree with this. The current plan for Ontario Health Teams does have merit. BUT, in order for these teams to succeed, they need strong family physician leadership at the GOVERNANCE level. That’s right, you need to put doctors (and more than just a token one) on the Boards of these teams and ensure the teams are led by them – for best clinical outcomes. I don’t see that in the plans.

Final Thoughts

My usual followers will know that I generally vote on the conservative side of the political spectrum (de gustibus non est disputandum). However, I’ve been frankly disappointed that the current Conservative government has been anything but conservative. Sadly, the other parties are really not offering the kind of transformative solutions we need in health care either. I firmly believe that we should all vote in elections, and I certainly will, but for now, call me an undecided old country doctor.

OMA Board Betrays Members By Latest Action and This Changes My Vote

OMA Elections period has opened. A chance for members to have a say in how the organization is run and what strategic direction it should take .

After my last couple of missives on OMA Elections, I was going to leave this alone and see what transpired. However, when I went to vote, I noticed a curious thing. None of the non-physician Board candidates were up for re-election. This sent up a red flag. There are three non-physician Board Directors – and every year, as members we have to vote for either one or two of them (the terms are staggered).

If one looks at the OMA website, this little nugget is hidden away in the depths of the Elections FAQ page, a page that I suspect extremely few members would access, much less be aware of:

“…In the case where the director holds a non-physician position and is interested in serving an additional term, the director would be presented to the membership as a re-appointed director…”

There are some conditions the sitting non-Physician Board Directors have to meet, but the blunt reality is that the OMA has taken away the right and ability of Members to vote for these 3 positions if those Directors want another term. This represents 27% of the Board (11 positions total) – which is frankly a large block of votes and can sway a close vote at the Board.

Worse is the vagueness of what is written for IF there was a vacancy. There are a number of requirements for running for the Board for these candidates – all of which are appropriate – however the very last sentence simply states:

“Shortlisted candidates will go through detailed vetting by Promeus Inc., including reference checks, police record checks and social media checks.”

Nowhere does it clearly state that in the event of a vacancy – there would be an election for the non-physician Board Directors. Perhaps this is still the case – however not mentioning it definitively in writing suggests the possibility that this may change.

I was on the OMA board when the governance changes took effect. I supported the overall thrust of them (still do). One of the issues when discussing non-Physician Board Directors was a concern expressed that the type of candidates that might help the OMA out would not want to run in an election. Apparently, these candidates would be “used” to being recruited and simply expected to be given a job.


I personally thought that was silly. If you’re a strong person, have a sense of self-worth, and are confident in yourself, you should be willing to run in an election. You might lose but that’s life (I’ve lost elections). But the personal integrity to run is essential. If the OMA is to represent members, then the members must have the right to vote for all Board Directors. Up until now, that’s what was happening.

Perhaps some non-Physician Directors are thinking “if I was on another board, they’d simply appoint me, and I wouldn’t have to take a chance on losing and ruining my precious resume.” But those are NOT Boards of representative organizations like the OMA

As far as I’m concerned, worrying about offending the egos of some candidates is not enough reason to take away the rights of members to choose ALL of their Board Directors. How much longer will it be before these 3 non-Physician Board candidates will simply be chosen by a process set up by the OMA without any input from the part of members? In case you think it unlikely, that is actually what was initially proposed by the governance consultants in 2019, until we shot it down.

Worse this change was made without an open discussion with the membership. The OMA should have presented arguments for this change to the members in an open, transparent manner. By hiding it in a FAQ without informing members is a betrayal of the principles of giving members power over the OMA. That was the main thrust of the governance changes in the first place.

What can members do? I mentioned in my previous blog that I personally won’t vote for incumbents. It seems that there’s only one incumbent up for re-election, current Board Chair Dr. Cathy Faulds. I have a lot of respect for Dr. Faulds (really). She’s accomplished much in her career (her resume is incredible) with work in health systems transformation/patient care advocacy and bilateral work with governments.

I was considering voting for her based on the fact that a good Board does need to hear all view points (even those that differ from mine) but I so fundamentally disagree with this move, and the current culture the Board has overseen that I personally can’t vote for her now. Whether other members see it that way is up to them.

A glance at the other candidates for Board show that there are 11 candidates who couldn’t be bothered to do a video statement to advertise themselves. Sorry – but as much as I disagree with the current elections process – if you are going to run for the top position at the OMA, and you can’t even find the time to put a video together to advertise yourself – well that is concerning.

My few loyal readers will know that I strongly supported Dr. Ramsey Hijazi last year – and continue to do so this year. He has consistently stood up for members – most recently by setting up a petition demanding that the government stop tormenting Dr. Elaine Ma for running a Covid Vaccination clinic. He’s also been strong in the press. He will get my first vote (which in the weird way the OMA weighs votes is the most important).

After that, there are a number of candidates that caught my eye – in alphabetical order – Dr. Khaled Azzam, Dr. Douglas Belton, Dr. Joy Hately, Dr. Pamela Liao, Dr. Afsheen Mazhar, Dr. Shawn Mondoux, Dr. Sameena Uddin, Dr. Darija Vusovejic. To be clear, members should review all the candidates themselves and vote, but I am going to vote for them after Dr. Hijazi.

As a family doctor, I also have a vote for my SGFP representative. Lots of great candidates running there. It will again, not surprise any of my followers that I will strongly endorse Dr. Nadia Alam for SGFP Vice-Chair. She’s an excellent leader and a dear friend. She took a well deserved break from medical politics for a bit. But it’s good to see her getting involved again and our profession will better for it. I leave the rest of the voting to your good judgement.

Disclaimer: NONE of the candidates listed asked me to endorse them.








