Dear Minister Jones – Fire Your Negotiations Team.

Dear Minister Jones,

Just me again, a certain crotchety and increasingly cantankerous geezer offering you advice in an open letter that you are not likely to take. But you would be better off if you did. More importantly, so would the people of Ontario.

Ontario Health Minister Sylvia Jones

First, I would once again suggest that you have done some good work in the health ministry. Moving surgical procedures to outpatient clinics, increasing the number of diagnostic testing facilities, starting a new medical school focused on training family doctors and more are all good moves. While the effects of some of those decisions will not be felt for many years – the reality is that somebody had to do this to help health care down the road and you’ve done that.

Unfortunately however, the past couple of weeks have been catastrophic for your Ministry’s relationship with Ontario’s doctors. It’s funny how one dumb decision or comment can completely wreck a relationship, but that’s exactly what happened when your Negotiations Team stated that there was “no concern” about a diminished supply of doctors. Therefore, they refused to negotiate money for retention of physicians or admin work, like other provinces have (cough BC, cough Manitoba, cough EVEN Alberta!)

In essence, your Negotiations Team has been a disaster, first by militantly dragging out negotiations into a very adversarial arbitration process (when all the other provinces above figured out a way to, you know, respectfully negotiate with doctors) – and then by making a statement about the supply of doctors that is so comically stupid and out of touch that Ontario has become a laughing stock.

Three members of the Ministry’s Negotiations Team pictured above.

This will not bode well for health care in this province.

Look, I know there may be a temptation to say “Ok this was a mistake” and to try and walk back the comments.. While it’s abundantly true that the people of Ontario are a good and kind people who will forgive politicians if they own up to their mistakes (cough greenbelt, cough enhanced police powers and closing playgrounds during covid) – one thing that politicians can’t survive, is being made a laughing stock. Except Donald Trump of course. I still haven’t figured that one out and I don’t think I ever will. (N.B. Donald Trump is not someone you should try to emulate).

Anyway, the reality is that at this point you really only have one path left to turn this thing around. You have to fire your negotiations team. All of them. I’m not just talking about the seven who were appointed to lead that team, I’m talking about the multiple bureaucrats who give them supporting data and have influenced their position.

The only rational explanation I can think of for those bureaucrats promoting a position of “no concern” about physician supply, and saying doctors are not working hard enough, is that they hate doctors. Many of them were likely hired at a time when it was fashionable to bash doctors for billing “too much”. (BTW how did that attitude work out for the people of Ontario?) They’ve clearly carried on with that belief in the arbitration proposals.

I get that in arbitration, there will be some posturing. If your Negotiations Team had said “we’ll pay you $50 a month as a retention bonus” or “admin work doesn’t involve seeing patients, so we’ll pay you $20 an hour” – I honestly would have shrugged my shoulders, recognized it was part of the arbitration “game” and said nothing.

But to say retention and recruitment of physicians is not a major concern, when people line up for hours on end just for the faint chance of getting a family doctor?? That thought process can only be due to a pathologic hatred of physicians, or a delusional mindset totally divorced from reality. Either is a cause for termination. Can the whole team now.

A long line forms outside CDK Family Medicine and Walk-In Clinic in Kingston, Ont.. It was the first day of ‘rostering’ at the clinic, where four doctors will take as many as 4,000 new patients. (Jamie Corbett) – from CBC News

But what of negotiations with the OMA you may ask?

Actually, that’s not hard either. Your ministry has an appointee to the Arbitration Board, just like the OMA does. I believe your appointee is one Kevin Smith. The job of the appointee is to tell you and your team what the lead arbitrator, William Kaplan is thinking and how he is leaning. How they do that is beyond me. When I met Kaplan it was like talking to a Vulcan. There was absolutely no emotion or hint of what he was thinking – but apparently Kevin Smith is better than I am at figuring this out.


One of the above is William Kaplan, Arbitrator, and even after meeting him I’m not sure which is which.

What your appointee will tell you, and what the OMA appointee to the Board will tell the OMA is – Kaplan is wondering “this” or thinking “that” or leaning towards “X percent”. Find out what that X per cent is, offer it to the Doctors for the first year of the new Physicians Services Agreement (PSA). That solves things for one year, which gives you time to pick a brand new negotiations team for year 2-4 for the PSA.

Note to my three loyal readers, yes, this arbitration is ONLY for the percentage increase of the first year of the four year agreement. Worse, while the OMA and Ministry have generally agreed to a 70/30 split of whatever the amount is with 70% allotted to raises, and 30% to be given to targeted programs, they haven’t been able to agree on how the 30% is to be targeted. This means…..more arbitration for that piece. Then, it begins again next year for years 2-4 of the PSA. In essence, we appear to be locked in a perpetual, never ending antagonistic arbitration process (which is still better than unilateral government actions but really frustrating nonetheless).

As I told Premier Ford recently- if health care doesn’t get fixed – I don’t care what the polls say now, or how many by-elections you seem to have won, this is going to be a real problem in 2026. With health care in the crisis it is in now, you need all hands working together and co-operatively. Locking Ontario’s doctors into two more years of extremely adversarial arbitration shows that we are not co-operating and not working together. This is why graduates are leaving the province. And we can’t afford that.

It’s time for you to do the right thing for Ontario, and cut bait with your current negotiations team.

Yours sincerely,

An Old Country Doctor.

Dr. Soni Writes to her MP About the Recent Tax Law Changes

My thanks to guest blogger Dr. Deepa Soni, an Emergency Room Physician at Credit Valley Hospital. She has written a much more eloquent letter to her MP about the recent tax changes introduced by the federal government, and allowed me to reproduce here as an open letter.

The Honourable Anita Anand,

MP, Oakville,

301 Robinson Street

Oakville, ON

L6J 1G7

 
April 20, 2024

Dear Minister Anand,

I’m writing to you as a constituent of your riding in Oakville regarding your government’s capital gains taxation measures introduced in this week’s budget.

As an emergency physician for the last 25 years, I and thousands of my colleagues in Ontario, were saving in our medical corporation to be able to fund benefits that many Canadians have available through their jobs: maternity leave, disability, and medical/dental benefits. In addition, and most importantly, incorporation allows us to save for our retirement as we do not have pensions (again, a benefit many Canadians, including government employees and civil servants have as part of their employment). Incorporation was a negotiated benefit that was given by the provincial government in lieu of increasing our fees, with the understanding that the structure would allow us to mitigate some of these factors about our career.

When planning for retirement under one set of assumptions, and then finding out that the federal government has moved the goal posts to extract revenue for its budget shortfall, you can understand why so many physicians are bewildered and disappointed by the Liberal government. This would be the equivalent of someone changing the terms of your pension or taking large chunks of it away. For many doctors, this will have profound impacts on their ability to retire when they thought they would.

 
In addition, as a daughter of first-generation immigrant parents, both of whom were physicians, I am certain you had a front row seat watching your parents work hard to obtain their medical degree, residency, and then establishing a practice. This is not to say that other Canadians don’t work hard: the one thing that makes doctors unique is that our fees are set by provincial governments and our fees have not risen to keep up with inflation. Unlike other incorporated professionals such as accountants, dentists, and skilled trades, physicians cannot increase their fees to make up for rising costs. We are locked into the fee schedule determined by provincial governments (who are always employing cost containing measures to balance budgets). The federal government is turning a blind eye to this important point as it does not fall under federal jurisdiction. Nevertheless, the impact cannot be ignored.

 
As a corporate lawyer prior to being elected an MP, I’m sure you would not have wanted your hard work and education to be characterized with the words ‘tax cheat‘ if you had been using a legal way to save for retirement. This is the narrative being circulated in the media and it is deeply disappointing. It is noteworthy that MPs receive an annual pay raise (this year ranging $8000-11900), along with pension and benefits. This makes an MP salary one of the highest earners in Canada, with guaranteed income through retirement.

Yet, it is doctors who are singled out as being in the wealthiest 1% and rhetoric implying that we are not doing our part for less fortunate Canadians. We pay into personal taxes and contribute to the economy like everyone else. As small businesses, doctors support the economy through employing staff (nurses, allied health, receptionists etc.), paying rent, and financially supporting many Canadian companies providing support services to our practices (electronic medical records, medical office supplies etc.).

We are also entrusted with caring for the population of Canada in the most sacred way. This taxation measure comes at a time when the medical profession in Canada is suffering unprecedented levels of burnout. Millions of Canadians cannot access a family doctor because they have closed their practises and left (in large part, due to rising costs and fixed fee schedules). Why in an era when attracting medical graduates to do family medicine is a priority, would your government eliminate one of the few advantages that help new grads set up comprehensive practices so they can care for Canadians from cradle to grave? Does your government understand the downstream effect this capital gains taxation will have on patients for decades to come? 

From watching media interviews recently, it appears that the federal government’s solution to this is “we will just allow in more foreign doctors“. This is deeply hurtful on many levels: it devalues currently practising physicians who have put in their life’s work to bring excellent care to this country’s patients. In addition, it takes many years for a doctor to acclimatize to the healthcare system in Canada. What happens to patients in the meantime? The solution is not to “throw the baby out with the bathwater”. The solution is to step back and really take in the impact of these actions and the message that has been conveyed to the physicians of this country. I hope your government will rethink this and choose to act fairly regarding incorporation for medical professionals. 

Sincerely

Deepa Soni MD CCFP(EM)

About Asking for Reduced Admin Burden From the MOH….

Lots of talk on the net about how the economic model for family physicians no longer works in 2024. My own blog site has had guest posts dedicated to this issue. There has been some criticism of this position. Dr. Darren Larsen in a reply to the post linked above suggests he is “not seeing or hearing…ideas for solutions“. He further states that all paying doctors more will do is create a “better-paid, unhappy professional. Nothing has changed.”

Others have made the similar comments. There is nothing philosophically wrong with the argument to reduce workload instead of raising pay. Practically speaking however, history has repeatedly taught us that the Ministry of Health (MOH) bureaucracy is incapable of delivering on that promise.

Some personal stories:

In the mid 2010s I was a Peer Lead for OntarioMD (no really!). I was frustrated by the Ontario Lab Information System (OLIS) because I had to manually retrieve all the lab work for a patient individually in their chart. Hospital Report Manager (HRM) by comparison, sends reports on all my patients directly to one inbox. (why we need two systems – and now more, is another story). The then VP of OntarioMD informed me they were working on “Practitioner Query” – which would allow me to get all my lab work from OLIS in one inbox. This was supposed to be ready in six months. That was over a decade ago.

From 2014-2018, thanks to the vision of my colleague Dr. James Lane, we developed an integrated health portal as part of our Health Links project for South Georgian Bay. For $35K a year, we were able to ensure that nursing homes could message physicians on their EMR. We dramatically reduced paperwork for physicians from nursing homes, improved health care outcomes, and reduced hospitalizations thus saving the entire health system money.

The MOH bureaucracy couldn’t wrap its head around this and wouldn’t allow it to continue.

For those of you who think I should have told people about this project, I wrote an article in the Toronto Sun about it. Afterwards, I got invited to do a presentation on this with the then CEO of eHealth Ontario and her senior team. Heck, when I was a keynote speaker at OntarioMDs Every Step conference in 2019 (no really!) I presented this project. The then head of the MOH Digital Health Team was there and heard it. Still, the bureaucracy couldn’t see their way towards allowing a project that saved physician time (and improved health care outcomes) could continue.

Ok, ok, so this blog is just for me to complain about not being listened to right? Well no, there are multiple other examples.

One workload issue for family physicians is keeping track of which of our patients get immunized for which vaccines. If only there was a central tracking system that sent the information to us directly. Wait, there is! The Covax system for tracking Covid vaccinations. Obviously the easiest and most sensible thing to do is expand the already existing system to add all the other vaccines so we get notified (eg when public health gives Gardasil). Yet 3 years after Covax, the MOH can’t even make this simple common sense change.

More? When I was on the SGFP Executive, one of our senior physicians told us the story of how he was on a working group to make the schedule of benefits (the fee schedule for Ontarios doctors) easier. After six months of meetings, they made a decision to add a comma to the descriptive sentence of one code. One comma in an 800 page schedule.

I could go on but you get the point. It’s fine for the MOH to say that that they promise to reduce the Admin burden for family docs. But frankly to these aged and cynical ears, it just sounds like them saying “This time we really mean it, honest!” – kinda like when Lucy promised to hold the football down for Charlie Brown for real this time, with predictable results.

Look, we have a five alarm crisis in family medicine in Ontario. Just about every week brings a story of another physician who is struggling with the economics of running a practice, and is considering quitting.

As with all emergencies, we need to have an effective triage system in place. Deal with the most urgent thing first, then go on to other things. We clearly can’t wait until 2034 for the MOH to implement some of the workload reducing schemes they might have (and no matter how much they promise they really mean it – it will take that long). So the first thing that needs to be done is bring financial stability to family practices so that they can continue to function while we sort out everything else.

Now, given Ontario physicians are in the midst of negotiating a new contract with the Ontario government, I expect the MOH team to say to our own negotiations team something like – “I know you guys want X% increase, but we can only give you 1/2 of that, but we promise to reduce your admin burden so you are working less hard”. I would do the same if I was them.

But, my expectation, and the expectation I think of the majority of doctors in Ontario, would be that the OMA negotiations team looks at the MOH team, and quotes the best engineer in the history of Starfleet to them.

With apologies to Geordi Laforge, B’elana Torres, Trip Tucker, Jett Reno, Andy Billups, and Hemmer – but Scotty was the BEST ENGINEER in the history of Star Trek!

The first step towards fixing the crisis in family medicine is a new physicians service agreement that stabilizes family practices. Once that’s done, work can begin anew on health systems transformation/workload reduction and so on. To try to do it the other way round, or even hand in hand, is a recipe for further collapse of the health care system.

Dr. Alex Duong: The Challenges Facing an Early-Mid Career Family Physician

Dr. Alex Duong, a family physician from the Vanier district of Ottawa (which amazingly enough is one of the more underserviced areas of Ontario).

Recently, Maria DiDanieli, the clinical lead for system navigation at the Burlington Family Health Team, published an opinion piece in Healthy Debate that was critical of the decision of Drs. Alam/Mathew and yours truly to recommend that family practice residents bide their time instead of starting up a comprehensive care practice in Ontario. Dr. Duong replies and has kindly allowed me to reproduce his reply here.

I am a full-time community family physician, and I read this article with great disappointment.


I am at the face of our health care system. When patients cannot get a timely breast biopsy or a knee replacement, they come to ask me. I address their frustrations, alleviate their pain, and manage expectations.


I am the backstop when issues are missed during transitions in care and issues that require follow up.


I am the navigator that helps patients, and their families orient themselves to housing resources, mental health and financial resources.


I am the advocate for my patient’s health when they deal with their employer or insurance companies.


I do all these things and more, alongside everything from newborn care to palliative medicine.


I, like the great majority of family physicians, take pride in our work, and in what we contribute to our patients and the community at large. But Banks do not grant loans for a new clinic based on my contributions to Ontario’s healthcare system. My rent payments do not decrease because of the positive impact I make on my patients’ lives. The salaries of our exceptional staff are not funded by the sound of clanging pots and pans.


Today, to outfit a new clinic with the minimum number of physicians for a FHO requires high 6 figures to 1 million dollars, loaned at 6.95% interest. We guarantee our own lease – we are on the hook for ensuring it gets paid for the entire term. We are responsible for hiring and ensuring our staff are paid a living wage. We invest our own time in making sure the clinic runs. For many community family physicians like me, there is no assistance for any of this from any level of government. No money for staff, no incentives for starting up, no support for logistics. We are in a precarious, failing business model with ever growing administrative burdens patching the system equal to a part-time job. We have been trying to expound on this, and frankly have been completely unsuccessful in this.


You realize that “… there does not seem to be much political will to improve this situation at this time.” Yet, you ask family physicians to work harder expecting a different result from the government.


You state that “With these current barriers and shifts, any new practice can feel fragile or vulnerable to imminent obsolescence.” Yet, you expect new graduates to take on a massive financial risk: long term lease, EMR contracts, and double their already tremendous debt in start-up costs.


You lament that “Instead of acting as beacons of wisdom, encouragement and level-headed advice, we see a growing shift toward inciting everyone to walk out!”. Do you apply this standard to the teachers in Quebec who recently concluded a strike? Are they less dedicated to their students? Do you apply this standard to all groups who organize to make their voices heard?


The authors, Drs. Alam, Gandhi and Mathew made it clear that there are many options available to new family doctors. They warn of the current state of specifically locking into comprehensive family medicine, to ensure that new grads do not put themselves in a position where they will be burnt out early in their career. To me, leadership requires honest conversations, not empty promises, or exploiting the ideals of new family doctors. I find it unethical to sell a romantic vision of what it is like to start and maintain a Family Medicine practice in the current environment. It is a recipe for moral injury when those ideals run flat into the economic realities, as I have experienced.

And frankly, to say to those of us, like myself, still practicing longitudinal family medicine we should be working harder, or we are just doing family practice wrong is demoralizing. It is grossly offensive to my early-mid career family medicine colleagues who have burnt out through great moral struggle and guilt. Disillusioned family physicians who leave longitudinal family practice will not return. The greater harm to the public and to patients is not the Star article that speaks truth to the issue, but the issue itself: that family physicians, whose concerns are being gaslit, continue to leave longitudinal practices.

Another Open Letter to the OMA Board: Re-visit the Negotiations Mandate

Dear OMA Board Member,

Just me again. The grumpy, aged quack with a history of being a bit of a thistle in your obliques. Well intentioned I assure you (although I’m told some may not see it that way).

Negotiations with the provincial government on a Physicians Services Agreement (PSA) continue and mediation began on February 20th. That’s all great and part of the process. However, things HAVE CHANGED a lot since the last time I wrote to you and urged you to set a strong mandate.

I am asking you to revisit the negotiations mandate at this time, in light of three new key pieces of information that are very relevant to Ontario doctors.

To recap – the negotiations mandate is the bare minimum ask that the Negotiations Task Force (NTF) can accept on behalf of the Board. If the government makes an offer that meets or exceeds that – well, then they accept it on behalf of the Board and the Board is compelled to endorse it. The mandate is, quite correctly, confidential (you can’t let the other side know your bare minimum ask any more than they would let you know their mandate). But it’s up to the Board to determine if the mandate is enough (not the NTF).

Now to be clear, I’m not saying you should revise it, just revisit it. Perhaps the mandate is already sufficiently strong. That would be great. But things are different now.

The first reason to revisit the mandate:

Other provinces have surpassed Ontario physicians in terms of income. BC and Saskatchewan have significant deals to stabilize the physician work force. Manitoba’s deal with physicians appears to be the best of the bunch. Manitoba has not only a well deserved increase for all physicians, but significant steps towards gender pay equity.

As an aside, while I applaud the fact that DoctorsManitoba made steps towards gender pay equity, I’m forced to wonder what happened to Ontario? When I was on the OMA Board we were proud of the fact that although it was too late, we were the first PTMA to report on the issues around gender pay equity. We proved that the pay gap was not because “women work less hard”. What happened ?

Also, to be clear I want to acknowledge that the negotiations counsel (Messrs Goldblatt and Barrett) are very well aware of any topic that could affect negotiations. I remember Darren Cargill, who at the time was on our NTF, told me “they read everything.”

Therefore, I know they read the Manitoba Schedule of Benefits which is available online and reported back to you. I’m sure you are fully aware of the retention bonuses in that deal. I’m sure you know about the significant changes that decrease the gender pay gap. I’m sure you know about the fact that Manitoba pays physicians for Admin time. And that their capitation model has no negation (although a lower base rate). And that they have an age premium. A pelvic exam premium (gender equity again). And that they allow extra payments for dealing with more than one problem at a visit. I have absolutely no doubt that our negotiations counsel has fully and thoroughly advised you of this, along with the benefits of the deals in BC and Saskatchewan.

The second reason to revisit the mandate:

The crisis in family medicine is spiralling out of control, faster than I thought possible. Not only is it badly affecting patient care, but the health, well being and morale of physicians is sinking like a stone. Last September, I never dreamed that I, along with Drs. Alam and Mathew, would write a letter to Family Practice residents telling them to stay away from comprehensive family medicine in Ontario. I never dreamed that there would be story after story after story of individual family physicians openly talking about how they were burning out. This situation has gone form bad to desperate frighteningly quickly.

The third reason to revisit the mandate:

Bill 124, the piece of legislation that limited increases to the public sector, was used to promote a low ball PSA to us the last time. You even, admittedly and embarrassingly, convinced a guy who should have known better. It’s ruled unconstitutional and the government will not appeal this. In fact they will repeal the Bill entirely. In light of that, many other public sector workers will be asking for catch up pay.

So it really is time for you to re-visit the negotiations mandate. Just double check to make sure it’s as strong as it should be given the above factors. Make sure it takes into account that the the BC deal has attracted over 700 physicians to comprehensive family practice. Make sure it recognizes that Manitoba will likely be showing a net growth in physicians shortly, and can reasonably attract physicians from out of their province. If you have to revise the mandate upwards after looking at it, then do so.

NB – IF the NTF were to push back if you do revise the mandate upwards, then make sure you hold your ground. Remember, YOU are the Board and YOU give direction to ALL committees and task forces, including the NTF. I’ll be careful how I say this so as not to divulge Board confidentiality, but the NTF in my day did have a proposal on one particular issue (not the whole PSA) that they told us to approve and our Board pushed back and said no. We had to listen to some (quite eloquent) speeches about how hard they worked and this undermined their work and so on and so forth – but after that they went back and kept negotiating as directed. Don’t do any less this time.

These negotiations are likely to make or break the profession for decades to come. They are that important. You owe it to your members to take another look at the mandate.

Yours truly,

An Old Country Doctor.

Open Letter to All Family Practice Residents

The following letter was jointly written by the three of us and published in the Toronto Star on February 20, 2024. It is being reproduced below so that we can share the letter on Facebook as we believe it will be of interest to physicians across Canada.

To All Family Medicine Residents, 

We are writing to say congratulations! You are nearly at the end of a decade of hard work, perseverance and sacrifice; ready to start your career and “real life”. You have joined a beautiful and unique specialty. You will be the key to the healthcare system. You will find answers when patients arrive with ambiguous symptoms. Others will tag in and out of a patient’s health journey. You will stay and be an essential part of the beginning, middle and end of every patient’s story. You will save lives. 

Your skill and knowledge are unparalleled, and there is no substitute for your expertise. 

Which is why with heavy hearts, we, the undersigned, recommend that you do not start your own family medicine practice in Ontario. Not right now.  

Family medicine is in crisis. Family doctors in Ontario are unable to provide the care they could and should. We face unprecedented levels of administrative burden, unsustainable business expenses, lack of healthcare resources, lack of social and cultural support for our patients and ourselves and finally, a lack of respect. This has led to widespread burnout and exhaustion.

In short, it is becoming frankly unsafe to run a family practice in Ontario, especially for those just starting.

We are family doctors with decades of experience. We are also physician leaders, past-presidents and board directors of the Ontario Medical Association (OMA), academic faculty, and health policy experts. We understand the situation well. 

Do not sign that contract. Do not sign a lease, hire staff, buy equipment, contract with an EMR or any of the million things that must be done so that you can start a comprehensive care family practice. 

Starting a practice at this time will require you to continue to sacrifice everything else in your life. If you have debt, you may not be able to pay it down, let alone start living the life you and many others have postponed for so long. You will struggle to spend time with your family, buy a home, care for vulnerable loved ones and more. You will continue to work at a non-stop pace, this time with no end in sight.

You will burn out and like many others, leave family medicine for good. This is why millions of Ontarians no longer have a family doctor.

The Ontario Ministry of Health can solve this crisis. 

Governments in Manitoba, Saskatchewan and British Columbia have done so. This past year, they made family medicine a priority – and backed their words with targeted funding toward key programs to support both new and established doctors. It comes as no surprise that they have welcomed hundreds of new family doctors into their communities.

If they can do it, so can Ontario.

What can you do in the meantime? Work in hospitals, hospices, operating rooms and long-term care. Work in obstetrics, anesthesia, as a hospitalist, in emergency or palliative care, oncology, sports medicine etc. Be a locum. Bide your time. 

You are skilled, smart, and adaptable. Your knowledge is extensive, demonstrating an unmatched depth and breadth of training. Use it.

When people leave comprehensive care family medicine, they almost never come back. 

We don’t want that to happen to you. When the government of Ontario recognizes family doctors as the foundation of medical care, negotiates a fair contract and improves health policies to reflect patient needs in 2024… well, when that happens, we will write a different letter and welcome you to the world you were meant to be in.

 We hope by then it is not too late.

Sincerely,

Dr. Nadia Alam, comprehensive care family physician and anesthetist, past-president of the OMA 

Dr. Sohail Gandhi, comprehensive care family physician and hospitalist, past-president of the OMA

Dr. Silvy Mathew, comprehensive care family physician and long-term care, past-board director of the OMA

Dr. Soni Reflects on the Delays in Emergency Rooms

Dr. Deepa Soni, and Emergency Room physician for over twenty years, reflects on the case of a young woman with appendicitis, and the delays in getting her care.

NB: Recently, Julia Malott spoke out on X (formerly known as Twitter) about how terrified she was about Canada’s health care crisis. She wrote how her daughter had not eaten in 18 hours as she continued to wait for surgery for appendicitis. She expressed concern about the lack of the beds and wondered if her daughter would get surgery before the appendix ruptured.

My friend Dr. Soni, who has worked in an Emergency Department for over 20 years, had, as usual, a very thoughtful and well spoken X thread of her own. (Dr. Soni was NOT involved in the care of this young woman). I thank her for allowing me to reproduce her thoughts here.

The only way these stories (about long delays in Emergency rooms) will stop being the norm, is when patients start sharing their experience like this mother did. Only voters can make federal and provincial governments change because votes are the only currency that matter. Doctors and nurses have been raising alarm bells for years without success.

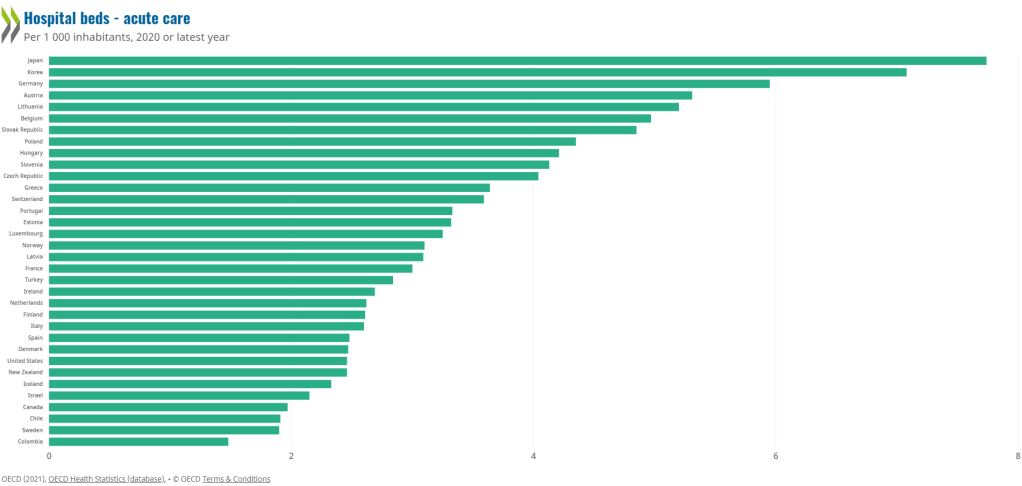
Canada has one of the lowest number of hospital beds of all the OECD countries, around 2.3/1000 people. In comparison countries like Japan, Korea and Germany are around 13/1000.

Graph showing how Canada fourth from the bottom (!) in hospital beds per capita.

Why does this matter? Having low hospital bed numbers means that words like “flu surge“, and “winter surge” — which have been used for decades to explain away long wait times and hallway medicine, are actually not “surges.” Rather, they are the expected backlog in a system that lacks adequate beds and resources.

The population of Canada is increasing and aging. We are about to enter a silver tsunami where a large cohort of our population will be over the age of 65 and many over the age of 85. This will place unprecedented pressures on our health care system.

What happens when the hospital bed capacity is outstripped by the numbers of patients needing care? It means that the elderly patient who needs admission to a hospital bed to recover from a heart attack has no bed to go to and spends days “admitted” in the emergency department. Bureaucrats call these “unconventional spaces.” What they really are, are stretchers.

When the vast majority of the emergency department beds are being used to take care of hospital patients, that means that patients that are waiting in the emergency department waiting room, will wait for hours for care, much like this story is describing.

Media needs to scratch beyond the surface and hold government to account. Real solutions are going to require thinking beyond the four-year election cycle. What will our system look like in 20 years? How do you plan for that?

It’s going to require recognizing the backbone of our healthcare system is primary care. Family doctors are overwhelmed by administrative burden, trying to run their offices and taking care of large practises in the community without adequate resources.


Build community infrastructure with resources like palliative care so that people can remain in their homes comfortably in their last days; and sufficient homecare services so that patients can receive antibiotics and other intravenous treatments at home to ease the pressure on hospitals. These services are vastly underfunded and do not have enough staff to properly provide care for everyone that needs it in the community.

It’s going to require building more nursing homes, retirement homes, seniors services and dementia care programs, as our elderly population will be the largest it’s ever been in this country.


Incentivize and properly pay hospital nurses so that we can recruit and retain them to be able to run departments and programs properly. Currently, agency nurses make at least two times as much as a hospital nurse, and this has created instability in the workforce. Governments need to show that they value nurses and the important work that they do.

Creative solutions like interprovincial licensing of doctors and nurses and a National Pharmacare program will help. While the idea of recruiting from other countries sounds like an easy quick fix, it will not solve anything if those newly obtained doctors and nurses find themselves overworked and burning out soon after arriving to Canada. The system problems are going to impact them just as they have impacted those who are already working in the system. This type of strain is what contributes to moral distress and burn out.

The backlog in the emergency department is a reflection of multiple failing areas that create an overall system that is strained beyond capacity. With each passing year, Canada’s healthcare system has become more and more stretched, trying to provide more care to more people, with fewer resources. Throwing Band-Aids at it is like trying to mop up the floor under an overflowing sink instead of trying to figure out how to turn off the tap.

Stories like this one are happening every day in Ontario and all of Canada. Most patients and families are too busy dealing with the acute health problem to take the time to write to their MP/MPP or to go to the media. But when people take the time to bring these stories to light, a critical tipping point will eventually occur where they can no longer be ignored by government. Because votes matter.

No one who went into healthcare wants to work in a system that makes patients feel like this story illuminated. But we need more voices bringing their stories out in the open. It will improve the system for the people working in it, and for the people receiving care within it. And that is better for everyone.

Dear OMA Board Member, About That Mandate for Negotiations

Dear OMA Board Member,

I read, with interest Ontario Medical Association (OMA) Board Chair Dr. Cathy Faulds update last Friday. There’s the usual information in there about the goings on at the OMA (which sadly not enough members pay attention to, though they should). Critically for most members however, was this comment by Dr. Faulds:

“The board will hold a special meeting at the end of September to finalize the negotiations mandate for use by the Negotiations Task Force (NTF)..”

This is a big step in the negotiations process and to truly understand that, members need to understand what a “mandate” is. Allow me to briefly expand on what Dr. Faulds wrote. The short version is that a mandate is the minimum offer the NTF can accept from the government. If the government offers an increase that is equal to or exceeds the mandate, then the NTF will automatically accept that offer on behalf of the Board.

The corollary to that, which some Board members did not understand when I was on the Board, is that if the mandate is met, and the NTF accepts – then it will automatically mean that you as a Board have to accept the offer as well. As per Board rules, you will then have to endorse the government offer to the membership. You can’t very well tell the NTF “you must achieve XYZ”, and if they do achieve XYZ, turn around and say it’s not enough.

Therefore, it is incumbent on you as a Board, to make sure the mandate is sufficient for the membership as a whole, given the times we live in, and the environment around us.

To that end, without spilling specific secrets, I will state that there was quite a lot of discussion about what an acceptable mandate was during my time on the Board. There were some Board Members who wanted to be “reasonable” and some who wanted to take a hard line and keep the mandate high.

I would, respectfully, point out that for the most part, mandates are never met. Usually the NTF comes back to the Board with “we tried – but this is the best we could get” and presents that to the Board. To be clear, I’m referring to all labour negotiations in general, not just physician ones. Negotiations Legal Counsel told us this last time, just ask them. Whatever you (or any Board) sets as the initial mandate, there is a strong chance the NTF will come back to you later and ask you to lower that mandate.

You will need to keep that in mind when setting your mandate.

To that end, I would encourage you to recognize that the time really has never been better to set the bar extremely high for the NTF mandate. It’s not just that physicians are considering leaving the profession. It’s not just that health care is collapsing all around us. It’s not just the ongoing problems with not just recruiting, but retaining physicians. You already know about all of those issues in excruciating detail.

No, the reality is that we now also have some significant competition for physicians within Canada from other provinces. And I mean strongly significant.

Not sure how many of you have seen this summary form the recently approved Physicians Services Agreement (PSA) in Nova Scotia. On the surface there would appear to be a fairly minimal 10% raise over four years. A deep dive however shows significant add ons like improved parental benefits, funding for overhead, funding to hire allied health care professionals, funding for admin work, enhanced FTE and income stabilization for specialists and so on. That plus a retirement fund!

Similarly, in Manitoba, their recent agreement was widely hailed as a landmark and a game changer. I spoke to a friend of mine from Manitoba who confirmed that it too contains things like a retention bonus ($21,000 and higher for those in rural communities), funding for admin time, funding for new models of care, additional funding for those patients who are older and an equity lens applied to fees. In short, the increase is widely viewed to be in the double digits percentage wise per year.

Look, I know the NTF knows all the stuff I’m pointing out (but others who read my open letter may not). I also would acknowledge that Dr. Mizdrak is a fine chair for the NTF and is (in a very good way and said with total admiration on my part) a real pitbull on behalf of the profession. I also have full confidence that the NTF did it’s due diligence in reviewing the many asks by the leaders of all the specialties.

But at the end of the day, it is up to you, dear Board Member to set the minimum acceptable deal (mandate) and it is up to you dear Board Member to ensure that Ontario remains a competitive place to attract physicians.

To that end, you must ensure that if there is a negotiated agreement, it must at least equal the increase in Manitoba or Nova Scotia (whichever is higher). Anything less would, quite frankly, be rightly viewed as the Board selling the profession out. (If we wind up going to arbitration, that’s a different story – but at least we will have gone there because the Board refused to take a sub optimal deal).

All of which is a long way of saying that since it is quite likely that an initial mandate may not be met, it is incumbent on the Board to set a mandate for the NTF that is HIGHER than what was achieved in Manitoba/Nova Scotia. This will allow for the usual process of the NTF having to come back and say what parts can be achieved and what can’t, and allow some wiggle room.

If you set the bar lower, well, frankly, I have to wonder how you can justify saying that you are advocating for the Doctors of Ontario.

Yours truly,

An Old Country Doctor.

RePost: Inside Ontario’s Bloated Health Care Bureaucracy

NB: This is a copy of a column I originally wrote for Postmedia in October of 2015. It’s copied here so that I can access it easily in the future. And a sad reminder that as of 2023, things haven’t changed for the better. If anything, they are worse.

Ontario’s health-care bureaucracy has exploded over the past 12 years, mostly because the government has set up a series of arm’s-length agencies it can scapegoat.

I’ve experienced this bureaucratic mess first-hand.

From 2013 to early 2015, I was the lead physician for the South Georgian Bay Health Links. I took the position because I was told the goal was to co-ordinate care between various health-care agencies to better help patients with the most complex illnesses.

Then-health minister Deb Matthews said there were too many “silos” in the health-care system and anointed her then-associate deputy minister the “silo-buster.” The ADM told us to develop a local solution — because each area is different — and focus on our strengths to help these patients.

Our area is very fortunate to have an advanced IT infrastructure. Virtually all 60,000 residents have an electronic medical record (EMR) in a joint database. We are also one of only two regions in Ontario with electronic prescriptions. This process requires the pharmacy to have a portal that allows it to communicate securely, in real time, with the physician to discuss issues of clinical importance.

My patients have benefitted significantly from this technology, so our thought was to set it up with other allied health-care providers (home-care nurses, retirement and nursing homes, community support workers, etc).

The Ministry of Health funded Health Links through the Local Health Integration Network (LHIN). So we put a proposal together and took it to the LHIN. The LHIN’s IT department liked the idea, but wanted to get input from the ministry. The ministry liked the idea, but wanted us to get the input of eHealth Ontario, the independent agency trying to create electronic health records. eHealth told us to come to a “regional network meeting.”

At the meeting, they thought the idea was good, but asked for the ministry’s eHealth liaison to comment. The liaison referred it to the ministry’s IT group (yes, the ministry has both an eHealth liaison group and an IT group) who wanted to ensure compatibility with a “provincial solution” — even though we were told to develop a local one — and suggested we review with the LHIN IT department.

After a year of “circling back” (a phrase I learned from these guys that I came to detest) we finally gave up, funded the project ourselves for $70,000 — less than a salary on the province’s Sunshine List — and my complex patients are now starting to see the benefits.

As I have come to appreciate, the government set up these various arm’s-length agencies, such as the LHINs, eHealth, Health Quality Ontario, Community Care Access Centres and so on, rather than simply have the ministry accept responsibility for these tasks. From a politician’s point of view, this gives them the ability to deflect criticism by saying such and such agency is “independent.” For the most part, this has worked for the Liberals. They’ve won four elections in a row. But it certainly hasn’t helped the patients any.

My colleague, Dr. Shawn Whatley, posted a superb blog piece that looks at how many bureaucrats work in Canada’s health-care system. It shows Canada has three times as many bureaucrats as other countries with advanced universal-care systems. Even worse, Ontario has only 1.7 acute-care hospital beds per 1,000 people, which is about HALF the average for other OECD countries. Ontario got to this number by closing 17,000 acute-care beds — and laying off the nurses needed to staff them — between 1990 and 2013.

But at least the bureaucrats are producing meaningful reports and are happy to be helping with moving health system transformation forward, right? Not so, according to a recent survey of health leaders conducted by Quantum Transformation Technologies. Most respondents said they aren’t happy with Hoskins or the LHINs.

It’s dramatic just how badly health leaders feel the system is working. The comments at the bottom of the survey are equally telling. There are repeated calls to cut the number of LHINs and reduce the size of the bureaucracy.

So in summary, Ontario is burdened with a bloated, ineffective, and demoralized health-care bureaucracy.

Wynne and Hoskins’ solution to this? Lay off nurses and start a fight with doctors over their fees.

Franz Kafka couldn’t have come up with something this convoluted.

— Mohammad Gandhi, MD, CCFP, FCFP, is an assistant clinical professor at McMaster and Queens universities. 

* More than 1,000 doctors recently joined a Facebook group to complain about how the Ontario Medical Association, which represents them, isn’t sticking up for them in their fee fight with the province.

Earlier this month, the province cut funding for doctor services by $235 million, chopping doctor fees by 1.3%.

******************************

GROWING HEALTH-CARE BUREAUCRACY

* There are 0.9 health-care bureaucrats per 1,000 people in Canada, compared to 0.4 per 1,000 in Sweden; 0.255 in Australia and 0.23 in Japan. Germany has 0.06 bureaucrats per 1,000 people.

* Ontario has only 1.7 acute-care hospital beds per 1,000 people, which is about half the average for other OECD countries. 

*****************************

A recent Canadian Institute for Health Information (CIHI) report — the one Premier Kathleen Wynne and Health Minister Eric Hoskins say shows “Ontario has the best paid doctors in the country” — also says 12,000 Ontario nurses left the profession this past year.

* It also shows Ontario has only 176 physicians per 100,000 people (ranking 7th in Canada).

* Ontario has the fewest family doctors per 100,000 people out of all the provinces. Only 10% of family doctors in the province are accepting new patients.

* A recent Quantum Transformation Technologies survey of Ontario health leaders found 55% think Hoskins is doing a poor to fair job, 62% think the LHINs are doing a poor to fair job, and 50% feel the government has a poor track record of helping those with mental health issues.

#Docxit on the Rise, Means More Trouble for Our Health System

Acknowledgement: I want to thank my friend Dr. Graham Slaughter for coming up with the term “Docxit”. Graham is not only a brilliant internist, but is incredibly talented at wordplay and music. Plus, he has really thick, lustrous wavy hair!

A bunch of stuff has come to my attention recently in my social life and on my social media feeds. I’m saddened by all of these and even more saddened by what this means for the residents of Canada.

Item 1: a friend of mine in her early 40s confided she is going to give up her family practice. She loves her patients, but the admin burden and the poor remuneration make it no longer feasible to do this work.

Item 2: two more friends of mine, also in their 40s, are actively making plans to leave medicine altogether. One of them told me she knew four family physicians (all in their 40s) who left this year alone, and two others in their 30s who have moved out of country.

Item 3: I came across a social media post from a friend of mine from my days in OMA leadership announcing he was now a real estate agent. Amongst the people congratulating him on passing his real estate exams were other physicians also saying they were look at ways of getting out of medicine.

Item 4: The family health organization I’m part of in the Collingwood area has gone from 52 family physicians to 47 as some have retired without finding a replacement, despite trying.

Provincially of course, there are many more such stories. Three family doctors in the Ottawa area left their practices earlier this year. Twenty per cent of family doctors in Toronto are planning on closing their practices in the next five years. The list goes on.

It’s not just Ontario. British Columbia is facing a “dire picture” when it comes to family physicians. Doctors Manitoba, through their excellent (now past) president Dr. Candace Bradshaw, pointed out the need for more doctors on more than one occasion. I could probably find articles from every province highlighting issues with recruiting and retaining physicians, but you get the point.

Doctors, it seems, are looking at leaving the profession (for either retirement or other jobs) in alarmingly high numbers. This phenomenon, dubbed Docxit by Dr. Slaughter, is happening at a time when our health system can arguably least afford it (if it ever really could).

This is particularly a concern as our younger physicians seem to be more likely to quit. A report by Statistics Canada suggested that up to 47% of physicians with less that 5 years experience are intending to leave or change jobs in the next three years. To be clear, they are not intending to retire, just do something other than what they’ve trained for.

From Statistics Canada

This phenomenon is not just present in Canada. The American Medical Association is concerned about “Medicine’s great resignation” as 1 in 5 physicians in the U.S. are also planning an exit in the next two years.

The situation in Europe would appear to be even more dire. The Politico article I linked to states that seven million people in France do not have a family doctor, with more family doctors retiring than setting up a practice. There is a shortage of two million health care workers in Europe. Brexit has badly worsened the shortage of doctors in the United Kingdom. Spain is running out of doctors. And so on.

Once again, those leaving appear to be over represented by younger physicians. It’s so bad that European Junior Doctors (an association of younger doctors in continental Europe) issued a press release warning the health care system there was going to collapse.

What’s going on then? Why are so many doctors leaving? I mean, despite the few (but loud) vociferous miscreants on social media, being a physician is still the most respected profession in the world (at 83% we’re tied with farmers and scientists). Studies show that Canadians trust their doctors to make the right choice for them and are afforded a measure of leeway that politicians and bureaucrats must surely be envious of. And you know that stereotype about first generation South Asian immigrants always wanting their kids to grow up to be doctors because of their status in society – it’s true (trust me, I and many of my friends lived it).

But the reality is that over the past ten years, practicing medicine has devolved to where it is no longer about caring for patients (which is what all good doctors want to do). In Canada, it’s been about fighting bureaucracy. With doctors now spending up to 19 hours a week doing paperwork (that’s a half a work week for most people) or fighting nameless, pointy headed, basement cellar cubicle dwelling bureaucrats to get them to actually pay for surgery that a patient needs, medicine is now more about who can do paperwork better than who can promote health care better.

In the United States, the rise of corporate entities eating up private medical practices has fuelled an explosion of a different kind of paper work, all with its own stresses. One study suggested that each physician spends almost $83,000 U.S. a year interacting with insurance companies.

Add to that the ludicrous number of options and waivers and liabilities and I sometimes think it’s easier to understand Einstein’s Theory of Relativity than it would be to understand U. S. Health Care. Dr. Glaucomflecken does an excellent job of explaining the frustration here:

I don’t know what the reasons for #Docxit are in Europe, but I imagine they are similar. The over bureaucratization of medicine is taking its toll everywhere. As was stated in the Politico article:

“At its core, it’s really that there is the perception that potentially medicine is no longer an attractive career choice, a choice for people to stay in for a whole career. And this will really endanger the sustainability of health care systems in future,” – Sarada Das, secretary-general for the Standing Committee of European Doctors (CPME)

There are so many crises in our health care system right now, it’s honestly hard to keep track. But two things are for certain. First, we won’t be able to fix health care without retaining doctors. Second, as more doctors opt for Docxit, we would appear to be doing a lousy job at retention.